Born Different, but Not Knowing Why

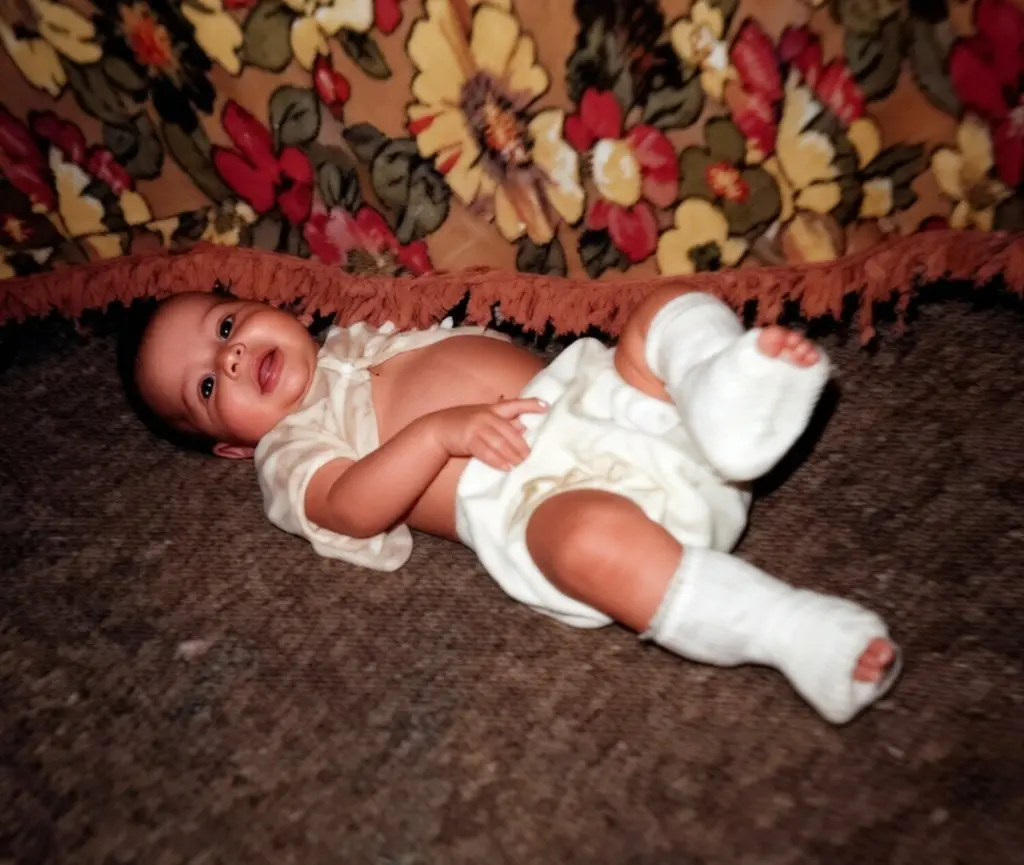
I was born into a body that was different from the beginning.

  • Clubfoot.
  • Left hip dysplasia.
  • Leg casts as an infant.

As an adolescent, I experienced severe growing pains, never realizing they might be connected to conditions that would take years to identify. Years passed. I lived life pain-free. 

By 2006, I was in the best shape of my life after losing 100 pounds through exercise and a low-carb diet. On May 9, 2006, I donated a kidney to my husband, Martin, an act of love I will never regret. We just celebrated our 20-year kidney transplant anniversary this year. 

At that time, I had not yet developed the debilitating symptoms of Chiari Malformation or Tethered Cord Syndrome (TCS). Then, in my 30s, everything changed.

2008: When the Symptoms Began

After riding a roller coaster in 2008, I immediately began experiencing symptoms that would eventually be associated with Chiari Malformation and TCS.

Brain imaging showed evidence of Chiari, but doctors didn’t interpret the findings in a way that led to answers. Because my cerebellar tonsillar herniation measured “only” 5 millimeters, doctors dismissed my symptoms as insignificant.

I knew something was wrong, but I struggled to get neurologists and neurosurgeons to take me seriously. Exhausted and frightened, I researched and advocated for myself until I finally found a specialist who understood.

Finding My Hero: Dr. John Oro

At 39, I found Dr. John Oro at the Colorado Chiari Institute. He diagnosed me with Chiari Malformation and Tethered Cord Syndrome.

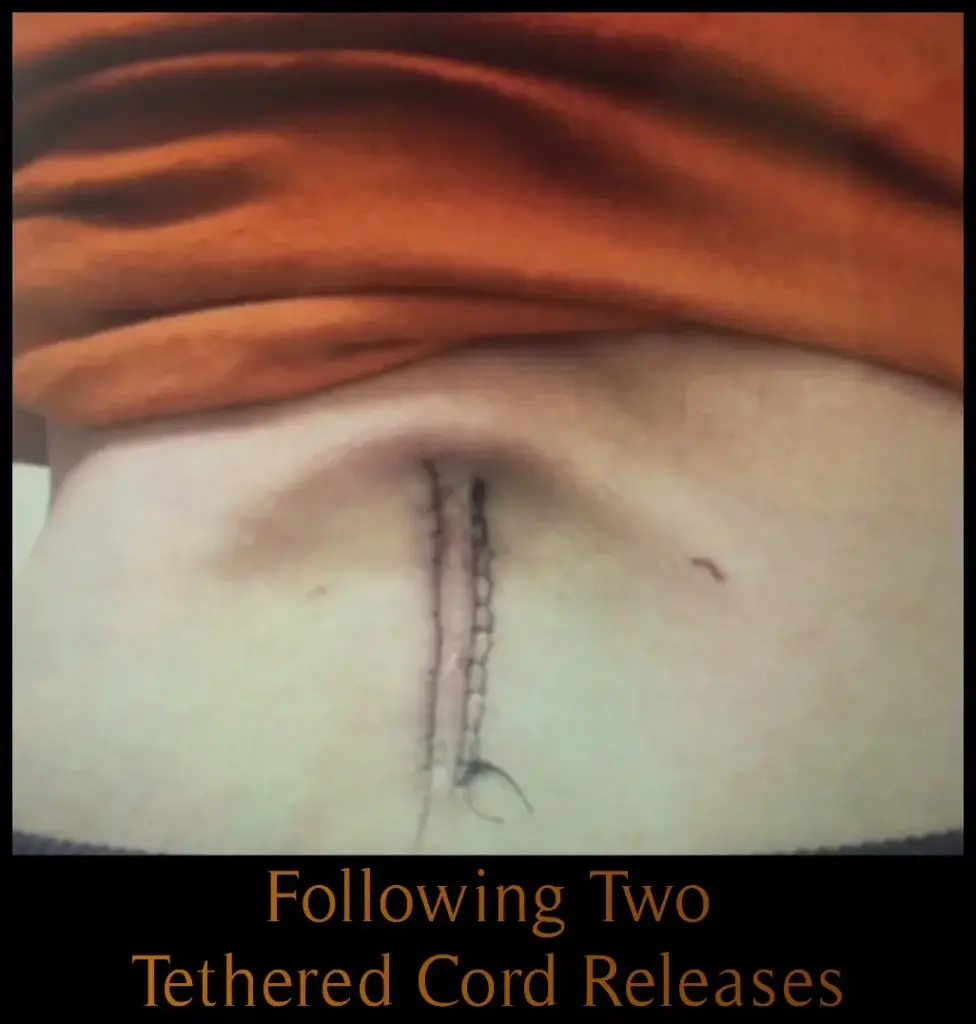
My TCS symptoms were more severe than my Chiari symptoms at the time, so in 2009, Dr. Oro performed my first spinal cord detethering surgery. For the first time, I felt understood.

Five Years Later: The Tethered Cord Returned

Approximately five years later, my spinal cord retethered, and my symptoms returned worse than before.

I traveled back to Colorado, where Dr. Oro performed another detethering surgery that lasted about four and a half hours. Afterward, I was able to “manage” my Chiari and TCS symptoms for a year.  

I hoped I could finally move forward, but my medical journey was far from over.
2016: The Crack in My Neck

In 2016, I heard and felt a crack in my neck. From that day forward, my Chiari symptoms became severe, and I began desperately seeking decompression surgery.

Dr. Oro had retired, so I had to find another specialist. Eventually, a UCLA neurosurgeon agreed to perform the procedure.

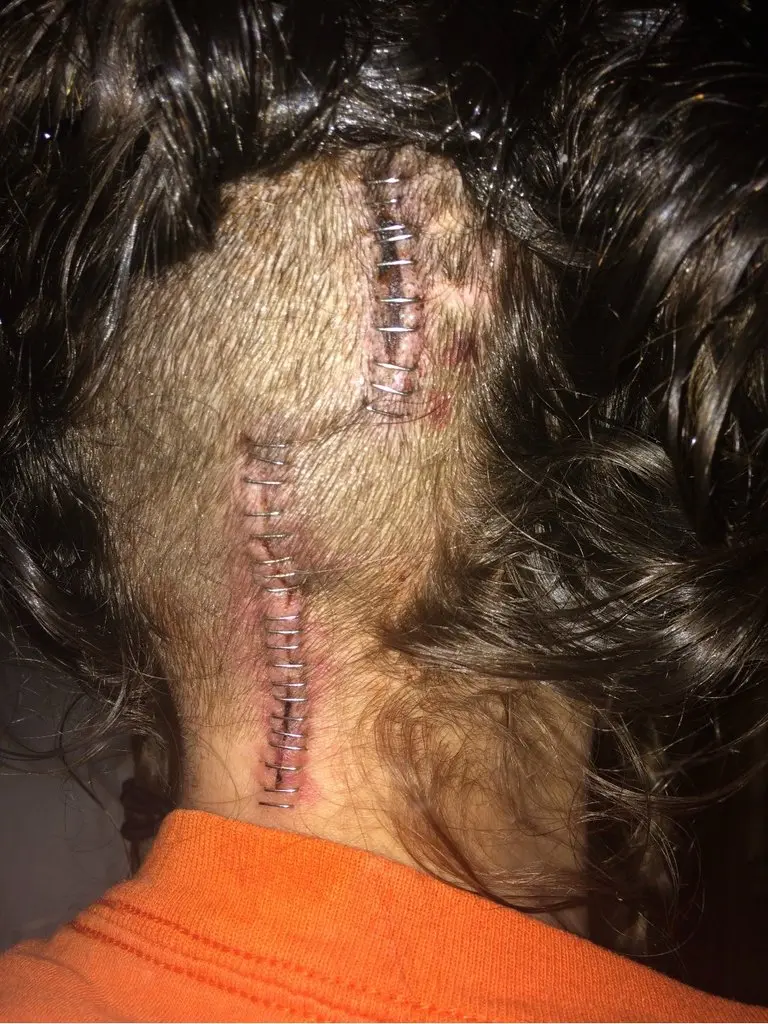
The six-hour surgery included cauterizing my cerebellar tonsils. Waking up was the most painful experience I had ever endured. I begged the medical staff to knock me out because the pain control was not working.

I eventually recovered, carrying the memory of that experience and 30 staples in my head. For approximately eight months, I felt some relief.

Then my symptoms returned.
The Clear Fluid: Discovering My Cranial CSF Leak

After those eight months, clear fluid began dripping from my nose, followed by horrific head pain. Local testing for a cranial cerebrospinal fluid (CSF) leak was negative.

Through my own research, I found Dr. Edward Hepworth in Colorado, a cranial ENT specialist who treats difficult-to-diagnose CSF leaks. After waiting eight months for an appointment, I traveled to Colorado and underwent a 48-hour hospital admission for a pledget study.

The leak was finally found.

In 2019, Dr. Hepworth repaired my cranial leak. During that same trip, I also had a hole in my heart closed.  

Hypermobile Ehlers-Danlos Syndrome: Connecting My Issues

In 2021, I was finally diagnosed with Hypermobile Ehlers-Danlos Syndrome (hEDS), a connective tissue disorder affecting joints, ligaments, and other tissues.

I had suspected hEDS for years, but obtaining a diagnosis was extremely difficult. The diagnosis helped connect some of the many conditions I had experienced, including clubfoot, hip dysplasia, Chiari symptoms, TCS, and my cranial CSF leak.

Each diagnosis added clarity, but none erased the pain or the years I had spent fighting to be heard.

Eighteen Surgeries: Learning the Language of Hospitals

Over the years, I have undergone 18 surgeries.

I learned the smell of hospitals, the sound of monitors, the fear before anesthesia, and the vulnerability of waking up unsure what pain would come next. I also learned how to navigate medical care and advocate for myself.

For years, I thought brain surgery was the worst pain I would ever experience.

I was wrong.

2020: The Day I Was Floxed

In 2020, I was hospitalized for an infected cyst below my parotid gland. I received Ciprofloxacin followed by intravenous Levaquin (levofloxacin), both fluoroquinolone antibiotics, over two days.

The day I was discharged, my life changed.

Severe, systemic pain began almost immediately. It spread throughout my body, making every movement difficult. I could barely walk, couldn’t tolerate anyone touching my feet, and couldn’t wear shoes.

I had survived brain surgery and spinal cord surgeries, so I knew what pain and recovery felt like. This was different. Surgery has an ending, an incision that heals, and the hope of recovery. Being floxed became something I had to live inside.

I felt like a walking corpse. At times, the suffering was so overwhelming that I wanted to die.

A Year of Medical Trauma and Gaslighting

For the next year, I lived in severe pain without answers. Doctors referred me to behavioral health because they could not explain my physical symptoms.

Being unable to walk normally, tolerate touch, or wear shoes while feeling disbelieved caused profound emotional harm. The experience became medical PTSD.

Then I learned about Fluoroquinolone Associated Disability, commonly known as FQAD. For the first time, I found information that connected my symptoms to the antibiotics I had received.

I finally had a name for what I believed had happened to me.

Spending Our Savings to Find Relief

My husband and I spent $23,000 of our savings on a five-day IV treatment followed by stem cell therapy. We made that decision because I was suffering so severely and needed a chance at a better quality of life.

I believe those treatments helped keep me from ending up in a wheelchair, but they did not restore my former life.

I am disabled now and live with severe pain every day. The woman I was before 2020 is not the woman I am today, and I continue to grieve what I have lost while learning to live with my body as it is.

January 2026: Finally Having a Diagnosis 

In January 2026, three months after the CDC approved a new ICD-10 diagnosis code for FQAD, I met with my primary care doctor to pursue official documentation of the long-term effects I had experienced after receiving fluoroquinolones.

My medical records now include: T36.AX5 — Adverse effect of Fluoroquinolone antibiotics, sequela (long-term effects).

After years of pain, confusion, and dismissal, I finally had validation, a diagnosis, and a name for what happened to me. 💜

This documentation does not erase my pain or restore my former life, but it matters. I wish I had known about the potential risks before receiving those medications. I wish I had been warned that serious, prolonged, and disabling reactions were possible.

I cannot change what happened, but I can tell my story.
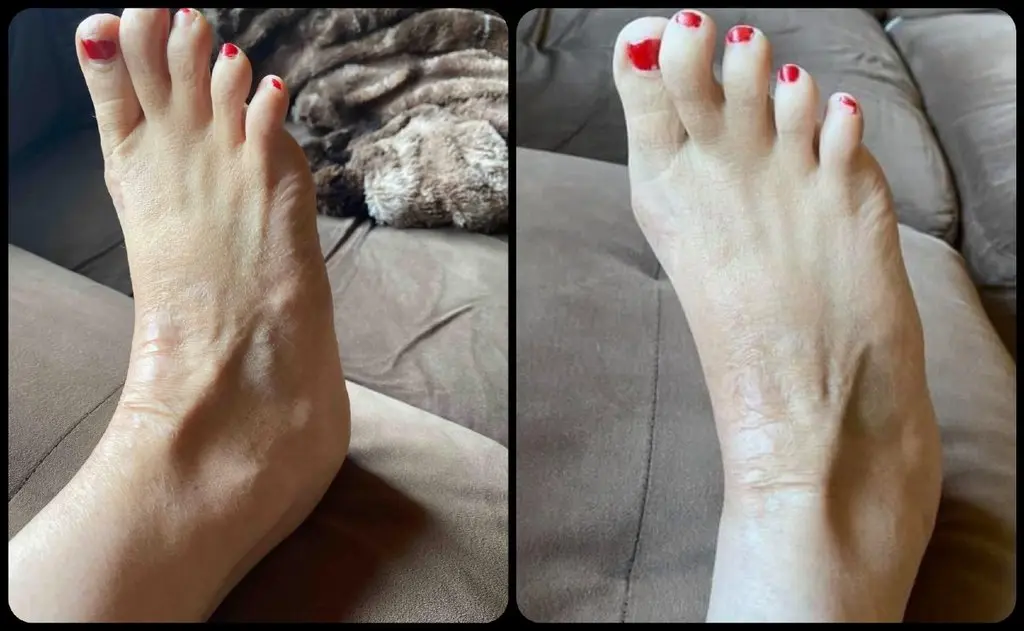
What Fluoroquinolones Did to My Right Foot

My right foot has become a visible reminder of the physical suffering I have experienced since receiving fluoroquinolones.

I want people to understand that serious adverse drug reactions can extend far beyond a hospital stay. When symptoms begin suddenly and pain becomes disabling, people deserve to be listened to and taken seriously.

I cannot undo what happened to my body, but I can raise awareness about fluoroquinolone-associated disability and encourage others to learn about the potential risks of these medications and seek medical care if concerning symptoms develop.

Many people are suffering, searching for answers, and struggling to be believed.

I am a daughter, a wife, a mother, a nana, and a woman who has survived experiences I never imagined facing.

I am more than my diagnoses, my surgeries, and the pain I live with.

If sharing helps someone find answers or feel understood, I will keep sharing.

Because after everything I have endured, I still have a voice, and I intend to use it!


*I dedicate this story to my family, my greatest blessings and my strongest support system throughout this difficult journey. To my husband, Martin, and our three beautiful daughters: Thank you for loving me through the pain, the tears, and the setbacks. Thank you for standing beside me, holding me up when I felt like I was falling apart, and loving me through the long haul. I am forever grateful for each of you. To Mom and Dad, and to my Wolf Pack, thank you for being part of my journey and for the love, strength, and support you have given me along the way. To Dr. Mark Ghalili, who saved my life. And to my fellow Floxies and everyone suffering from Fluoroquinolone Toxicity: this story is for you, too. For those living with invisible pain, grieving the lives they once knew, fighting to be believed, and finding the strength to keep going. You are not alone. Your pain matters, your story matters, and your voice deserves to be heard.

To read more on the safety issues surrounding fluoroquinolones, check out our article: “When “Safe and Effective” Fails: Fluoroquinolones and the Erosion of Public Trust.”


For decades, patients seeking medical care trusted a simple, foundational principle of medicine: First, do no harm. When a doctor handed down a prescription, patients assumed the medication had been thoroughly vetted for safety. Adverse reactions were presented as statistically negligible cases—unintended side effects in the march of modern medical progress.

Yet for millions of patients, especially those living with connective tissue disorders like Hypermobile Ehlers-Danlos Syndrome (hEDS) or Chiari Malformation, that trust has been shattered.

The history of fluoroquinolone antibiotics stands as a stark case study in institutional failure. Marketed for decades as routine frontline treatments, these powerful drugs were later retroactively hit with severe Black Box warnings. This story reveals a deeper crisis: the ongoing breakdown of public faith in corporate medicine.

The Rise of Fluoroquinolones: Profit Over Caution

Introduced widely in the 1980s and 1990s, fluoroquinolones were hailed as broad-spectrum miracle drugs. The class includes well-known medications like Ciprofloxacin (Cipro), Levofloxacin (Levaquin), and Moxifloxacin (Avelox). They were fast-acting, effective, and convenient.

Driven by aggressive pharmaceutical marketing, doctors routinely prescribed them for minor, uncomplicated issues: sinus infections, mild UTIs, bronchitis, and ear infections. Millions of prescriptions were written every year.

Behind the scenes, however, a troubling reality emerged. Early clinical trials—often funded and designed by the drug manufacturers themselves—were never structured to catch delayed, long-term, or multi-systemic damage. As these drugs dominated the market, reports of life-altering side effects began piling up in patient communities around the world.

A History of Withdrawals and Delayed Warnings

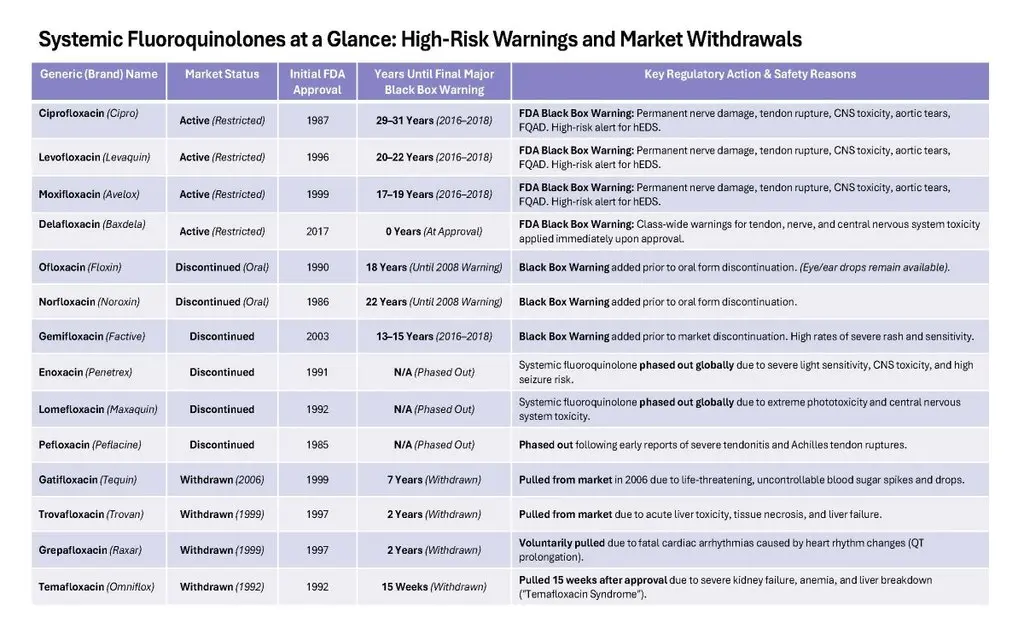
For years, regulatory agencies insisted that severe reactions were statistically negligible. Yet the safety history of fluoroquinolones tells a different story—one marked by sudden market withdrawals and late, reactive warnings.

Decades to Acknowledge the Damage

Decades of fierce patient advocacy, ruined lives, and overwhelming real-world evidence were needed for the FDA to intervene. Between 2008 and 2018, the agency issued a series of increasingly severe Black Box warnings—the strongest safety alert short of a total ban:

  • 2008: Warning added for an increased risk of severe tendinitis and tendon rupture.
  • 2013: Warning updated to explicitly state that nerve damage (peripheral neuropathy) can happen rapidly and become permanent.
  • 2016: The FDA stated that for simple infections (like sinus or mild bladder infections), the risks of fluoroquinolones outweigh the benefits, advising doctors to use them strictly as a last resort.
  • 2018: Warning issued specifically for high-risk populations—including individuals with Ehlers-Danlos Syndrome, hypermobility, or aortic aneurysms—due to the risk of aortic tears, tissue breakdown, and permanent disability.

The Hidden Peril for hEDS and Chiari Patients

For patients living with Hypermobile Ehlers-Danlos Syndrome (hEDS) or structural conditions like Chiari Malformation, these delayed warnings came at a devastating cost.

hEDS is a connective tissue disorder caused by defective collagen. Collagen is the physical scaffolding that holds together tendons, ligaments, blood vessels, and fascia throughout the body.

Fluoroquinolones interfere with collagen production and break down connective tissue. Giving a collagen-degrading antibiotic to a person whose body already struggles with fragile collagen is a dangerous combination. The result is often Fluoroquinolone-Associated Disability (FQAD)—a severe syndrome marked by widespread joint damage, tendon tears, burning nerve pain, and profound loss of mobility.

To make matters worse, patients who experienced these sudden post-antibiotic breakdowns were routinely dismissed. Because standard bloodwork and imaging rarely catch subtle cellular damage, patients were gaslit, told their symptoms were “just anxiety,” or referred to mental health providers. They were left to suffer both physical destruction and severe medical trauma.

How Medical Hegemony Shattered Public Trust

The tragedy of fluoroquinolones is not an isolated mistake or a single company’s oversight. It reveals a repeating pattern within modern healthcare:

  1. Declarations of Safety: A pharmaceutical product is launched, backed by industry-sponsored trials, and declared safe and necessary for broad populations.
  2. Suppression of Early Warnings: Patients and independent clinicians who raise early alarms about side effects are ignored, dismissed as “anecdotal,” or accused of spreading misinformation.
  3. A Slow, Reluctant Retreat: Years or decades later—after thousands of lives have been disrupted—institutions quietly update labels, attach Black Box warnings, or pull drugs off shelves, rarely acknowledging the damage done.
  4. The Informed Consent Loophole: Even after Black Box warnings are issued, doctors are not legally required to verbally inform patients of these warnings before handing down a prescription. Patients are left to discover the risks on their own—often only after irreversible harm has already occurred.

When public health institutions demand uncritical trust while enforcing rigid corporate consensus, they destroy the foundation of real science: open debate, continuous reassessment, and listening to patient outcomes.

When guidance shifts from “safe and routine” to “risk of permanent disability”—and patients are kept in the dark at the exam table—public skepticism is not irrational. It is a logical tool for self-preservation. Patients can no longer afford to blindly trust institutions or providers that prioritize commercial convenience over genuine patient safety.

What You Can Do to Protect Yourself

If you or a loved one live with hEDS, hypermobility, or any connective tissue disorder:

  • Always Disclose Your Diagnosis: Make sure every doctor, surgeon, and pharmacist knows you have a connective tissue condition before you accept any new prescription.
  • Ask for Alternatives: Unless you face a life-threatening infection with no other option, request a safer, non-fluoroquinolone antibiotic.
  • Listen to Your Body: If a medication causes sudden, burning nerve pain, joint stiffness, or extreme weakness, seek medical evaluation immediately and advocate for your safety.

Science is an ongoing process of testing, learning, and refining—not an unquestionable doctrine. By speaking up, sharing real experiences, and demanding accountability, patients are leading the way toward a safer medical system.

Real progress in medicine will not come from top-down decrees or silencing debate. It comes from empowered patients, transparent science, and true informed consent.

Surviving Chiari Malformation, tethered cord syndrome, and FQAD taught Michelle Nieves that staying silent is not an option. Her journey exposes why independent advocacy like Chiari Bridges is indispensable—it pushes back against dogmatic diagnostic criteria, shines a light on undocumented drug toxicities, and demands that medical institutions prioritize real-world patient outcomes over corporate consensus. Read her story, “The Michelle Nieves Story – Reclaiming My Voice: hEDS, Chiari, and the Hidden Dangers of Fluoroquinolones.”

Standard sugars cause dangerous blood glucose spikes, but for many in our community, standard sugar-free alternatives are off the table because of Mast Cell Activation Syndrome (MCAS).

Many common artificial sweeteners (like aspartame, sucralose, and saccharin), and even certain sugar alcohols (like erythritol or xylitol), can trigger mast cell degranulation. They can spark systemic inflammation, brain fog, digestive distress, and skin flares [1].

Fortunately, a fascinating molecule pulls triple duty: L-glycine.

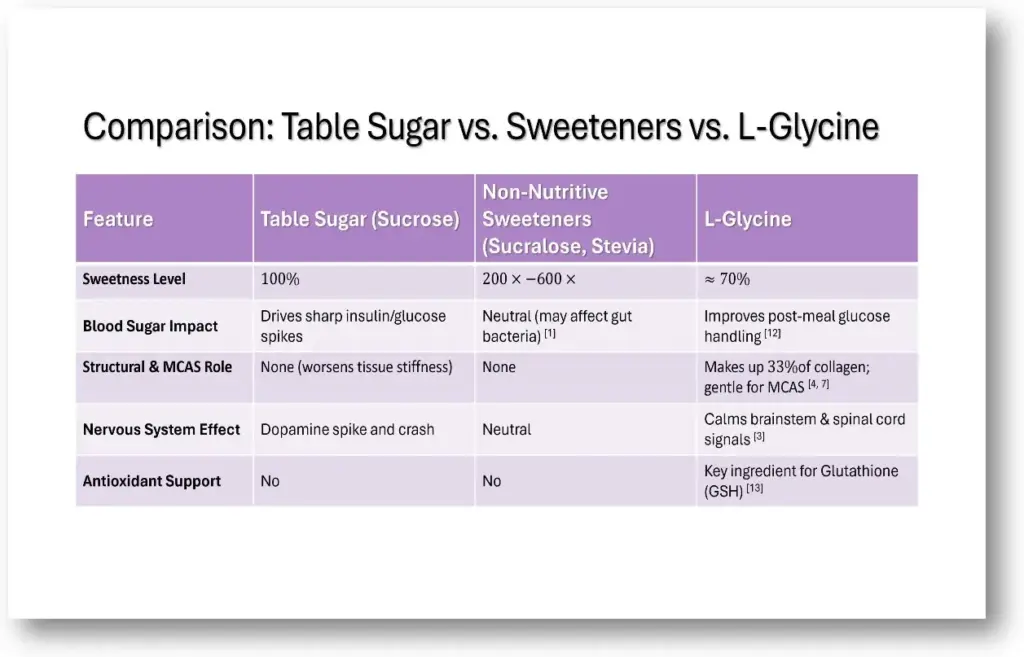
Metabolically speaking, glycine isn’t a sugar or an artificial sweetener—it is a functional amino acid (a protein building block). It tricks your tongue into tasting sweetness by binding to your mouth’s sweet flavor receptors and sending a “sweet” signal to your brain with zero actual sugar or synthetic chemicals [2].

People often dismiss glycine as just a sleep aid or simple sweetener. In reality, it is a key amino acid that supports tissue repair, immune stability, blood sugar control, and nervous system balance.

For people navigating hypermobile Ehlers-Danlos Syndrome (hEDS), Chiari Malformation, Craniocervical Instability (CCI), MCAS, or dysautonomia, glycine offers targeted benefits far beyond replacing sugar.

1. The Mast Cell Side: A Stabilizer-Friendly Option

  • Bypasses Artificial Triggers: Because pure L-glycine is a natural amino acid already native to the human body, it doesn’t trigger the chemical-induced mast cell flares common with synthetic sweeteners [1].
  • Calming to the Nervous System: Glycine acts as an inhibitory neurotransmitter in the central nervous system. By helping calm an overactive sympathetic nervous system (fight-or-flight), it can indirectly lower the systemic stress response that often drives mast cell reactivity [3, 4].
  • Soothing to the Digestive Tract: Many artificial options feed gut dysbiosis or irritate a sensitive GI tract. Glycine is rapidly absorbed via specific amino acid transporters in the upper small intestine, so it won’t ferment in the gut or cause bloating. Instead, it actively helps protect and repair the fragile intestinal mucosal barrier [5].

2. The Structural Side: Supporting the hEDS Collagen Matrix

  • The Premier Collagen Building Block: Collagen is structurally made up of a repeating chain of amino acids (Glycine - X - Y), and glycine makes up roughly one-third (33%) of that entire matrix [6]. In hEDS, genetic mutations make connective tissue inherently fragile, leading to chronic wear and tear that requires constant cellular turnover [7]. While supplemental glycine cannot alter these underlying genetic mutations, ensuring adequate amino acid availability matters because standard human metabolism naturally falls short of the massive daily demands of baseline collagen synthesis [8].
  • Protecting Tissues from Glycation: High blood sugar causes sugar molecules to bond to proteins in a destructive process called glycation, creating Advanced Glycation End-products (AGEs). This process stiffens collagen and makes it brittle—a double hit to tissue integrity for an hEDS patient. Glycine acts as a shield, helping to protect fragile connective tissues from this sugar-driven erosion [9].

3. Brainstem & Nervous System Support (Chiari & CCI)

Chiari Malformation and Craniocervical Instability can compress the brainstem and spinal cord, disrupting cerebrospinal fluid (CSF) flow and over-exciting the central nervous system.

  • Natural “Brakes” for Pain & Spasms: Glycine is the primary inhibitory (calming) neurotransmitter in the spinal cord and brainstem [3]. When it binds to its receptors (GlyR), it acts as a nerve damper, helping quiet motor hyperexcitability, muscle spasticity, and chronic pain signals [3, 10].
  • Autonomic & Vagal Balance: Many Chiari and hEDS patients struggle with dysautonomia (like POTS). Glycine exerts central anti-inflammatory effects and modulates brainstem tone, helping buffer against hyper-adrenergic “fight-or-flight” surges [3, 11].
  • Balanced Brain Function: In the brainstem and forebrain, glycine also works alongside glutamate as an NMDA co-agonist, supporting healthy memory and neuroplasticity without driving excitotoxicity [3].

4. Blood Sugar Control & Glutathione Production

Rather than spiking blood sugar, glycine actively helps your body manage glucose and protect against cellular stress.

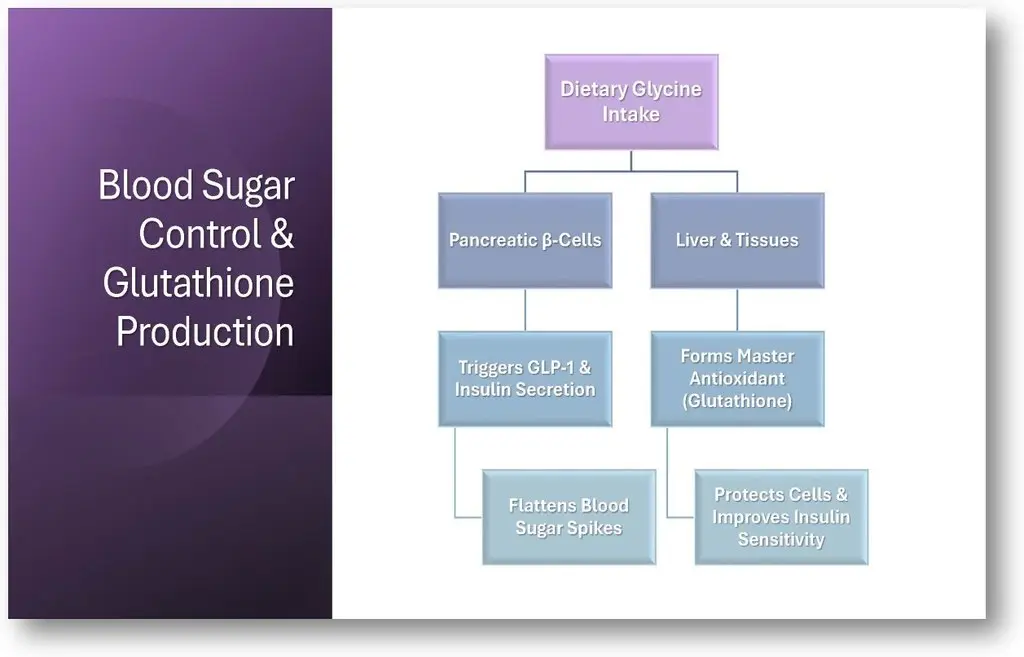
  • Flattens Glucose Spikes: When taken with food, glycine stimulates the gut hormone GLP-1 and triggers insulin release, helping prevent sharp blood sugar spikes after meals [12].
  • Builds Glutathione (GSH): Glycine is a required precursor for glutathione—the body’s master antioxidant [12]. Keeping glutathione levels high protects against liver inflammation and systemic oxidative stress [13].
  • Protects Tissue Elasticity: Glycine inhibits Advanced Glycation End-products (AGEs), “sticky sugars” that cross-link with collagen and stiffen joints and blood vessels over time [9].

5. The Glutathione Bottleneck: Why Glycine Often Pairs with NAC (GlyNAC)

While glycine is essential for glutathione synthesis, it doesn’t work alone. Glutathione is a tripeptide composed of three amino acids: glycine, glutamate, and cysteine [13].

Because cysteine is typically the hardest precursor for the liver to source, dietary cysteine (most commonly supplemented as N-acetylcysteine, or NAC) acts as the primary rate-limiting step [13].

  • The GlyNAC Synergy: Clinical trials demonstrate that combining glycine with NAC (GlyNAC) dramatically boosts intracellular glutathione levels, reduces systemic oxidative stress, and improves mitochondrial energy production better than either amino acid alone [14].
  • A Note of Caution for MCAS & Sensitive Stomachs: While GlyNAC is a powerful metabolic tool, NAC contains sulfur and can sometimes trigger histamine release or gastric distress in sensitive MCAS patients.
  • Best Practice: Ensure glycine tolerance first before introducing low-dose NAC, and always discuss new amino acid protocols with your healthcare provider.

💡 How to Use It in Your Routine

Pure L-glycine comes as a clean, white powder that dissolves easily in warm liquids. With a gentle, smooth sweetness, it pairs well as a functional sweetener in custom herbal blends—like morning coffee or my personal favorite, Spiced Dandelion Root Tea—to help protect metabolic health, soothe mast cells, and nourish connective tissue.

  • Standard Therapeutic Dose: Clinical studies generally look at 3g to 15g per day, divided into smaller doses with meals or before bed [11, 13].
  • Sleep Quality: Taking a 3g dose 30–60 minutes before bed helps lower core body temperature via peripheral vasodilation, promoting deeper slow-wave sleep [14].
  • Avoid Stomach Upset: High single doses (> 10 g at once) can pull water into the bowel, causing loose stools or cramping in people with slow GI motility.
    • Tip: Start with a low dose (1-2 g per meal) and slowly work your way up to see what your body tolerates best.

References

  1. Afrin, Lawrence B., et al. “Some Cases of Hypermobile Ehlers–Danlos Syndrome May Be Rooted in Mast Cell Activation Syndrome.” American Journal of Medical Genetics Part C: Seminars in Medical Genetics, vol. 175, no. 1, Mar. 2017, pp. 48–69, doi:10.1002/ajmg.c.31944. onlinelibrary.wiley.com/doi/abs/10.1002/ajmg.c.31944.
  2. Schmidt, Robert W., and Meghan L. Thompson. “Glycinergic Signaling in the Human Nervous System: An Overview of Therapeutic Drug Targets and Clinical Effects.” Mental Health Clinician, vol. 6, no. 6, Nov. 2016, pp. 266–76, doi:10.9740/mhc.2016.11.266. PubMed Central, pmc.ncbi.nlm.nih.gov/articles/PMC6007534/.
  3. Li, Xiangli, et al. “Dietary Glycine Prevents Peptidoglycan Polysaccharide-Induced Reactive Arthritis in the Rat: Role for Glycine-Gated Chloride Channel.” Infection and Immunity, vol. 69, no. 9, Sept. 2001, pp. 5883–91, doi:10.1128/IAI.69.9.5883-5891.2001. PubMed Central, pmc.ncbi.nlm.nih.gov/articles/PMC98707/.
  4. Howard, Alison, et al. “Glycine Transporter GLYT1 Is Essential for Glycine-Mediated Protection of Human Intestinal Epithelial Cells Against Oxidative Damage.” The Journal of Physiology, vol. 588, no. 6, Mar. 2010, pp. 995–1009, doi:10.1113/jphysiol.2009.186262. physoc.onlinelibrary.wiley.com/doi/full/10.1113/jphysiol.2009.186262.
  5. Shoulders, Matthew D., and Ronald T. Raines. “Collagen Structure and Stability.” Annual Review of Biochemistry, vol. 78, no. 1, June 2009, pp. 929–58, doi:10.1146/annurev.biochem.77.032207.120833. PubMed Central, pmc.ncbi.nlm.nih.gov/articles/PMC2846778/.
  6. Tinkle, Brad, et al. “Hypermobile Ehlers–Danlos Syndrome (a.k.a. Ehlers–Danlos Syndrome Type III and Joint Hypermobility Syndrome): Clinical Description and Natural History.” American Journal of Medical Genetics Part C: Seminars in Medical Genetics, vol. 175, no. 1, Mar. 2017, pp. 48–69, doi:10.1002/ajmg.c.31538. onlinelibrary.wiley.com/doi/10.1002/ajmg.c.31538.
  7. Meléndez-Hevia, Enrique, et al. “A Weak Link in Metabolism: The Metabolic Capacity for Glycine Biosynthesis Does Not Satisfy the Need for Collagen Synthesis.” Journal of Biosciences, vol. 34, no. 6, Dec. 2009, pp. 853–72, doi:10.1007/s12038-009-0100-9. Indian Academy of Sciences, www.ias.ac.in/article/fulltext/jbsc/034/06/0853-0872.
  8. Wang, Xuan, et al. “Glycine Suppresses AGE/RAGE Signaling Pathway and Subsequent Oxidative Stress by Restoring Glo1 Function in the Aorta of Diabetic Rats and in HUVECs.” The Journal of Nutritional Biochemistry, vol. 70, Aug. 2019, pp. 16–25, doi:10.1016/j.jnutbio.2019.03.018. PubMed, pubmed.ncbi.nlm.nih.gov/30944692/.
  9. Gundersen, Rune Y., Pål S. Opstad, and Frode Fonnum. “Glycine – An Important Neurotransmitter and Cytoprotective Agent.” Acta Anaesthesiologica Scandinavica, vol. 49, no. 8, Sept. 2005, pp. 1108–16, doi:10.1111/j.1399-6576.2005.00786.x. onlinelibrary.wiley.com/doi/abs/10.1111/j.1399-6576.2005.00786.x.
  10. Zafra, Francisco, et al. “Glycine Transporters and Its Coupling with NMDA Receptors.” Advances in Neurobiology, vol. 16, no. 1, Meeting 2017, pp. 55–83, doi:10.1007/978-3-319-55769-4_4. PubMed, pubmed.ncbi.nlm.nih.gov/28828606/.
  11. McCarty, Mark F., and James J. DiNicolantonio. “The Cardiometabolic Benefits of Glycine: Is Glycine an ‘Antidote’ to Dietary Fructose?” Open Heart, vol. 1, no. 1, May 2014, pp. 1–9, doi:10.1136/openhrt-2014-000103. PubMed Central, pmc.ncbi.nlm.nih.gov/articles/PMC4195924/.
  12. Sekhar, Rajagopal V., et al. “Glutathione Synthesis Is Diminished in Patients with Uncontrolled Diabetes and Restored by Dietary Supplementation with Cysteine and Glycine.” Diabetes Care, vol. 34, no. 1, Jan. 2011, pp. 162–67, doi:10.2337/dc10-1006. PubMed Central, pmc.ncbi.nlm.nih.gov/articles/PMC3005481/.
  13. Kumar, Premranjan, et al. “Supplementing Glycine and N-Acetylcysteine (GlyNAC) in Older Adults Improves Glutathione Deficiency, Oxidative Stress, Mitochondrial Dysfunction, Inflammation, Physical Function, and Aging Hallmarks: A Randomized Clinical Trial.” The Journals of Gerontology: Series A, vol. 78, no. 1, Jan. 2023, pp. 75–89, doi:10.1093/gerona/glac135. https://academic.oup.com/biomedgerontology/article/78/1/75/6668639.
  14. Yamadera, Wataru, et al. “Glycine Ingestion Improves Subjective Sleep Quality in Human Volunteers, Correlating with Polysomnographic Changes.” Sleep and Biological Rhythms, vol. 5, no. 2, Apr. 2007, pp. 126–31, doi:10.1111/j.1479-8425.2007.00262.x. https://onlinelibrary.wiley.com/doi/full/10.1111/j.1479-8425.2007.00262.

Some names have no meaning, and some names mean absolutely everything to and about the bearer of the name. Our name falls into the latter category. Despite the more popular acronym, WTF! stands for Worth The Fight!

The origins of our name began with someone whom I love to the moon and back, who was struggling with depression. This person was cutting themselves, tried to mask their pain with drugs and alcohol, and attempted suicide before I ever realized what was going on with them.

Life isn’t easy for a Chiari family. From the moment that I was told that my head and neck pain wasn’t just pain, but something wrong with my brain, everything in our family dynamic changed. Everything became centered on me.

“Don’t stress mom out.” “Let Mom rest.” “Can’t you see how much pain she’s in?”

Surgery came just weeks after diagnosis for me. It was in the hope that I could become the wife and mother that I once was, the wife and mother that my family so desperately needed me to be. Two years after decompression, I had a revision to fix a pseudomeningocele (leak) with an SP shunt (Subgaleo-peritoneal). It was about a month after this second brain surgery that I realized that there was much more going on in my house than I’d ever dreamed.

It was just after 2 am when there was a bone-chilling pounding on our front door. It was the kind of pounding that would awaken even the heaviest of sleepers – the kind of pounding that you’d never forget. My husband and I rushed to the front room, where siren lights and multiple people shone flashlights into our windows. A fire truck, an ambulance, and the police arrived. We opened the door, and one of the officers informed us that they had reason to believe that our daughter had attempted suicide. Words could never express the feelings that I had as I ran desperately to her room, unsure about what I’d find when I opened the door. She was alive, but incoherent and unaware of her surroundings. The officer intervened to assess her condition, asking if she could get up and come out of her room to talk. One officer spoke with her, and two others pulled us aside to talk to us while the paramedics stood by. Everything was surreal. How could I concentrate on hearing and answering questions when I didn’t even know if our daughter was going to live or die? The officer explained that she had called a friend after taking pills with wine. The friend told his mom, and together they called the police while he continued talking with her. She had initially told this friend that she was in a park across town, so the police had been scouring the park looking for an overdosed teenage girl, and when they couldn’t find her, they pinged her cell phone, which led them to our home just in the nick of time. My emotions raced. How could this be when she had come to our room earlier that night, looking tired, telling us how much she loved us, and that she was going to bed? (We should have known that something was wrong, but again, I had been so lost in my own world that I couldn’t see all that my children were going through at the time.) After assessing our daughter, the attempt was deemed “credible and in immediate need of emergency care,” and she was transported by ambulance to the county hospital emergency room.

My husband and I followed in our car. At the hospital, we were informed that she had taken multiple doses of my husband’s blood pressure medications and multiple doses of my opioids. The doctors said that the first concern was her heart, “if” she survived through the night. The next concern would be liver toxicity since the opioids all contained Tylenol. And that if she survived and made it through those steps and was deemed stable, she would be held on a 5150 (Involuntary Psychiatric Hold). While we prayed at her side, her blood pressure dropped to the low 50s/20s. We called for the doctor and they told us that there was nothing more they could do (it was too late to try to pump her stomach), she would either survive the night or wouldn’t. They told us to try to keep her awake, so we walked laps around the ER every single time her blood pressure dropped in an attempt to keep her awake. I don’t know how I held up my head that night; I was running on pure adrenaline at the thought of losing my only daughter. She survived the night, and while we still had to wait for the toxicity reports on the liver tests, they allowed us to walk with her over to the Psychiatric Department of the hospital.

After a twenty-four-hour evaluation, our daughter was moved to a San Francisco hospital for a week-long intensive therapy program. We couldn’t visit her for the first few days. We were limited to scheduled phone conversations. At first, she just wanted us to go get her. It’s incredibly hard as a parent to be in a position where you legally cannot just take your child home. But we knew she needed help beyond what we could offer, and eventually she realized that too.

Over the week, she worked on herself, and we worked on creating a safer environment for her to come home to (they actually have a checklist when something like this happens involving a teen). I won’t go into all the details of how we tried to safeguard our home and family after realizing that Chiari hadn’t simply set out to steal from me physically, but that its attack extended to our entire family in every way. But I came across a website that really caught my attention.

I happened upon a story, “To Write Love On Her Arms,” by Jamie Tworkowski. It’s a story of a group of friends learning how to fiercely love a friend struggling with depression, addiction, self-injury, and suicide. They would write the word “LOVE” on her arms; the same arms that she had been carving the words “FUCK UP” on. They figured that if she went to cut her arms again, she’d be reminded how greatly loved she really was.

Chronic pain conditions (such as Ehlers-Danlos, Chiari Malformation, and the other comorbidities) can take a toll on us and how we think, how we see our future, and the value that we see ourselves having in this world. As we become increasingly dependent on our family members, we see the burden it places on them, and it hurts. We know that they say that we’re ‘not a burden,’ but we see it. When we hear those that we love deny that a burden exists, we know they’re just saying that because they love us. “It’s nothing,” they tell us. IT’S NOT NOTHING! IT’S EVERYTHING! BECAUSE THEY MEAN EVERYTHING TO US! Perhaps it would be healthier to say that ‘we’re worth the burden,’ instead. No mother can deny that having a newborn baby is a burden of love. It’s absolutely exhausting, but we know that despite the burden, no matter how hard it gets, that little baby in our weary arms is absolutely worth the work! (Just like my daughter and all that she went through, there’s nothing that I wouldn’t have given to see her through it. She was worth it!” As I continued my fight, I realized I was too, and if we were going to fight to win this battle, we had to have real conversations about my fight. My family had to be allowed [encouraged even] to admit that they get exhausted without fear of hurting me or offending me. It enabled us as a family to put the blame on my condition so that it was Chiari that had robbed us, not me. It had robbed all of us, and we weren’t going to play games and put it on anything or anyone else. We were going to fight back as a family!

So if anyone has a problem with our name or our acronym, I’m perfectly okay with letting that be THEIR PROBLEM.

If you have a family member struggling with our conditions, you’re going to have to strengthen one another through it! WE HAVE TO STOP DENYING THE MAGNITUDE OF THE FIGHT, acknowledge it (every part of it), and fight back as a family, where every single person in that family KNOWS (beyond a shadow of a doubt) that they’re WORTHY! That even if we as a family must go to the ends of the earth together, it’s worth it, because each of us is WORTH THE FIGHT! And if someone forgets, write it on their arm to remind them!


This article is dedicated to my daughter, MyKaella, who taught me what it means to live knowing that we’re WTF! I’m so proud of the woman you’ve become and the woman that you helped me to become!


This mindset influences your actions and shapes how others perceive, believe in, and respond to you. It also determines the extent to which your medical team and support systems can assist you. Others can only support us as much as we value ourselves and are willing to invest in our own well-being. Your self-image and self-appreciation directly impact your ability to advocate for yourself and assert your rights as a deserving individual and patient. You have the right to take the time to express your concerns and ask questions, with the expectation of being listened to, supported, and respected without bias. Furthermore, you are entitled to all information about your health so you can make informed decisions about your care and livelihood. Unfortunately, we do not always receive this from medical professionals or government agencies, despite years of contributing to these systems. Therefore, it is essential to be prepared to advocate for yourself when necessary.

EMPOWER YOURSELF THROUGH EDUCATION

Learn and understand your diagnosis. Researching and understanding a Chiari diagnosis is crucial for self-advocacy; learning to utilize online resources, articles, and support groups to gather information. Finding reputable, evidence-based sources, such as those referencing peer-reviewed studies, helps justify concerns to medical professionals despite encountering conflicting information due to ongoing, rapid research in the field. For more information, visit Chiari Bridges.

Learn and understand your diagnosis. Researching and understanding a Chiari diagnosis is crucial for self-advocacy, which includes learning to utilize online resources, articles, and support groups to gather information. Most of the information available is found online in articles, websites, videos, and online support groups. Finding accurate, up-to-date, and reputable sources is paramount. Here at Chiari Bridges, we try to reference the studies and peer-reviewed articles behind our information, so you know the official sources that the information came from and will be better able to justify your requests and concerns to your doctors. Regardless of your source, be prepared to find a lot of conflicting information. These contradictions mainly exist because Chiari and its co-morbid conditions are being researched like never before, so it’s an exciting time, but that fails to give much comfort to those having to fight with their doctors on the existence of every symptom they face.

Know your rights as a patient and your doctor’s legal responsibilities. Rights and responsibilities are often governed by state and federal laws and are outlined and included in the paperwork given to you from medical practices, health care systems, hospitals, and facilities. Your providers will likely require you to sign that you agree to and understand them. In doing so, these are legally binding for both parties. Thus, you will want to make sure you understand them fully before signing them and get a copy for your own records (if they don’t give them to you, don’t be afraid to ask for a copy).

Learn and understand your health insurance. Know what your policy does and does not cover. Become familiar with which doctors, medical services, and facilities are covered. Find out about copays, deductibles, out-of-pocket costs, and other relevant information. Find out if your policy includes out-of-network benefits and associated costs, including out-of-state benefits. If no out-of-network/out-of-state benefits exist, find out if exceptions can be made. Almost all insurance plans do have some form of exceptions and/or appeals process for this very purpose. There are commonly two stages of appeal: an internal review (your appeal is reviewed in-house) and an external review (where you are specifically asking for a review made by an outside organization that has not been a part of your provision of care and has no conflict of interest).

Learn about Advance Directives, Living Wills, Durable Healthcare Power of Attorneys, etc. You will want to familiarize yourself with all of these and decide what, if any, is right for you.


EMPOWER YOURSELF BY DEVELOPING SKILLS AND ACCESSING TOOLS

Communication Skills and Tools. Learning to know when and how to communicate your needs and desires to others is important, especially when you have a limited amount of time with your doctor. Brevity, clarity, relevance, problem-solving, negotiating, and preparation are key skills and tools. It might be beneficial to sit down beforehand and write the specific points you want to address and your ultimate goal for the appointment. Maintaining a respectful dialogue is always of utmost importance. Keeping your emotions under control is crucial.  Otherwise, your doctor might take you less seriously or assume your symptoms stem from psychological causes.

Medical Records. As a patient, it is important to always obtain a copy of your medical records and review them for accuracy. It was once thought amongst medical professionals that a patient’s medical records were solely for doctors to communicate amongst themselves. Some medical professionals still hold to this antiquated ideology and become obviously disgruntled that you have chosen to exercise your patient right to not only obtaining your medical records but also, demanding they are 100% accurate. What is listed in those medical records will be used to treat you. It is important they are accurate and are corrected if they are not.

Keep copies of all imaging and radiology reports. Images are not kept forever, nor are other medical records. Sometimes doctors do not tell you some of the things found in your imaging/reports and other tests because they deem them “incidental” or irrelevant. Sometimes, doctors miss what is obviously clear altogether. Many Chiarians go through years of misdiagnosis before being properly diagnosed. Often, a look back through your medical records will show patterns and assist in the discovery, diagnosis, and treatment.

Patient Portals. With the advent of portals being used in many practices and facilities, patients now have easier, free access to many of their medical records. The same rules apply to the information retained in the portals regarding how long it is kept there. Any conversations you might have with your provider through the portals should be saved as well.

Organization and Preparation. Every person has their own way of “organizing.” This extends to your medical records keeping as well as preparation for appointments. There are some free online resources to help you with this organization. Some like to make a “chart” for their medical records by creating a binder with tabs. Some use digital charts/record-keeping tools for free online or for purchase. Many phone apps exist to help as well. However you decide to organize is up to you, but it is an invaluable tool to help you arm and equip yourself for self-advocacy.

Self-Care and Coping Skills. We often underestimate the necessity of self-care, as well as the power of developing positive, healthy coping skills and techniques. Self-care is pretty standard for all: getting proper nutrition, rest, appropriate and safe exercise, taking meds faithfully, taking time for recreation and refreshment, and tending to the beauty that is your body, mind, and spirit. Everyone has ways they “cope” in life in general and within the framework of chronic illness. It’s important to find the ones that work for you.


EMPOWER YOURSELF BY FINDING THE RIGHT DOCTOR(S)

Self-Education. Self-education precedes the ability to find a good doctor. If you are not aware and knowledgeable about your diagnoses and disorders, you will not recognize whether a doctor is the right one for you. Educate yourself on your conditions and on what your potential doctor has published on your conditions: What are their credentials, experience, affiliations, number of cases they have treated, and specialties and sub-specialties? Look for any official publications, scientific journals, or other research that your provider may have written. Additional information can be found online through state records and other sources regarding your physician.

Ask family, friends, and other medical professionals. Find others who have PERSONAL FIRST-HAND doctor/patient experience with the potential provider. Keep in mind a doctor can be a great fit for one patient but not for another. You can also ask for the opinion of your present doctors or other medical professionals.

Getting 2nd Opinions and When to Find Another Doctor. It is never wrong, always wise, and completely within your rights as a patient to seek a second opinion (or more). If you are facing a potential surgery or procedure that could be risky and/or permanent, it is prudent to get multiple opinions. It is your right to ask for and change doctors at any time or facility. You do not need to give any reason nor explain yourself, though you will likely be asked to do so. Be careful not to burn bridges or become “blacklisted.” Always find a new doctor before leaving the old one.


EMPOWER YOURSELF BY DEVELOPING YOUR SUPPORT SYSTEM AND GETTING HELP. Being a self-advocate does not mean “going it alone.” Developing and surrounding yourself with a support system is vitally important, and many consider it to be “their lifeline” to keep going.

Local or online support groups. Finding the right local or online group can be just as important as finding the right doctor and educating yourself. Remember, there is a lot of accurate and inaccurate info out there (even amongst our medical professionals). A support group is only as good as the respect they have for you in your fight. If they respect the Chiari fight, it will be evident in the way they treat one another and in the accuracy of the information they espouse and share. Online groups each tend to have a different set of rules that members are expected to follow: some allow and encourage advice and recommendations amongst their members, and some do not allow it at all. Not every group will be the right fit for each Chiarian, but you can expect any good group to be kind, supportive, respectful, accurate in the information disseminated, gentle in correcting inaccurate information shared, respectful of your autonomy and choices, and zero-tolerance for bullying.

Workplace Support. There are laws that protect you, and that can even provide assistance and support within the workplace that you should familiarize yourself with. The Family and Medical Leave Act of 1993 (FMLA) is a federal law in the United States requiring employers to provide employees with up to 12 weeks of job-protected, unpaid leave for qualified medical and family reasons annually; but you must file it as FMLA leave to get the protection.

School Support. There are programs and opportunities within schools that you should also familiarize yourself with and use to protect yourself if your Chiarian is in school. In the United States, the US Department of Education has worked hard to incorporate federal laws to help reduce discrimination and increase structured programs to help ensure the success of students with disabilities. As a result, most schools, including colleges, have programs where students with disabilities can get special allowances for recording devices, note takers, removal of time limits on tests, etc. These programs are usually subsidized at a state level and have different names depending on your state, but a school counselor should be able to point you in the right direction. These protections may be limited in privately funded colleges and universities that do not receive any public funds.

Support and Assistance Programs. There are many programs, assistance, and support available in nearly every local area (through county trustees, charitable organizations, and churches), as well as state and federal programs. Just are few examples of help available are assistance with mortgage, rent, utilities, food, clothing, medical bills, medical insurance, free or reduced-cost prescriptions, holiday assistance, back-to-school, free or reduced-cost dental clinics, pro-bono legal help, cash assistance programs, etc.

Professional Advocate Support. While self-advocacy is important, you might find that you need more help than you can accomplish alone. Managing your health can be confusing and overwhelming. Sometimes it can be hard to get your voice heard by the healthcare professionals around you. The healthcare system itself is very complicated. If you are having difficulty finding your way through the complex maze of healthcare, you might want to consider seeking the help of a professional advocate. There are hospital advocates, non-profit patient advocates, for-profit (employer-based) advocates, and independent advocates for you to turn to.

Family and Friends Support. Chronic illness can take a huge toll on relationships. We all want and need the love and support of our family and friends. Not everyone has this support, making it all the more painful. No two families or friendships are alike. If you find a lack of support amongst your friends and family members, seek to restore it and, in the meantime, find another means of support, as Chiari is not something you want to fight alone. Support groups are a good alternative means to help find the support you need.

Counseling Support. Sometimes we all find ourselves struggling to cope. Maybe we lack support or want to protect our relationships by not always talking about our problems to friends and family, yet need an outlet. Finding a therapist can be one of the best things we can do for ourselves. Doing so doesn’t mean you’re crazy or weak. It is a sign of strength and indicates that you value and respect yourself in every facet of your life, which brings us back to the reason we learn to self-advocate in the first place. Believe you are worth it – all of your body, mind, and spirit! If you ever find yourself in a life-threatening crisis, don’t be ashamed to contact a crisis hotline.

When to get a lawyer. If you believe you are the victim of abuse, harm, malpractice, or neglect, consider speaking with a malpractice attorney. If you think your workplace rights are at risk, contact an employment lawyer. If you can no longer work due to your condition, look for a disability lawyer. Elder law attorneys may also be helpful, and their services are not limited to the elderly. Whenever you feel your rights have been violated, it may be time to seek legal counsel.

Self-advocacy will empower you to know and speak up for yourself, make your own decisions, learn and exercise your rights and responsibilities, learn about your condition(s), and how to get accurate up-to-date information in order to make decisions concerning your care, treatment, and overall well-being. It will help you find the right doctors, support systems, options, resources, and get other help available to you. As you journey along in self-advocacy, you will grow both as a patient and a person. You will also discover many additional ways that self-advocacy benefits and empowers you, and in turn, you’ll be able to help pass those benefits on to others as well.


Most Chiarians go to see a surgeon with an expectation of them being knowledgeable in their field. However, while they might be a neurosurgeon, their knowledge of Chiari and its comorbid/pathological conditions might not rank high in their practice. Make the most of your initial appointment by interviewing them and what they really know about Chiari Malformations. Be cautious of inflated success rates. Chiari decompression in general offers a just over a 50% success rate (which means it has a nearly 50% failure rate). Surgeons that claim a 100% (or near 100% success rate) are usually not basing their success on how their patients feel afterward, it is based on if they were successful with the aspects of the surgery:
         Removal of the occipital bone ✓
          Opening the dura and adding the patch/graft ✓
          Laminectomy ✓
          Cauterization/resection of cerebellar tonsils ✓

WE DESERVE BETTER THAN THAT!


HERE IS A LIST OF CHIARI QUESTIONS WE RECOMMEND ASKING AT YOUR FIRST NEUROSURGERY APPOINTMENT:

General Questions:

  • How do you define a Chiari Malformation?
  • What do you believe causes a Chiari malformation?
    • Are all Chiari malformations from a small posterior fossa?
    • Do I have a small posterior fossa? If yes, how big is it? If size is unknown, was my posterior fossa measured? If not, why not? How did you come to the conclusion that I have a small posterior fossa?
    • How common do you believe Acquired Chiari malformations to be?
  • Do you always recommend decompression surgery for all of your patients with herniated cerebellar tonsils? Why/why not?
  • In an average month, how many Chiari decompressions do you perform? How many tethered cord releases? How many craniocervical fusions? What percentage of your practice is spent treating patients with these connective tissue related conditions?
  • Looking at my brain scan, is any part of my “brainstem” herniated (below the posterior fossa)? If so, does that make me a Chiari 1.5?

Intracranial Hypotension (low pressure) Questions:
*Article to help you understand CSF Leaks & Intracranial Hypotension prior to your appointment.
If you have SYMPTOMS OF LOW INTRACRANIAL PRESSURE and/or suspect a cerebrospinal fluid leak, we recommend asking the following questions:

  • S.E.E.P.S.
    • Looking at my brain scan, do you see any Subdural fluid collections?
    • Looking at my brain scan, do you see an Enhancement of pachymeninges?
    • Looking at my brain scan, do you see an Engorgement of my venous structures? Should we do an MRV to make sure?
    • Looking at my brain scan, does my Pituitary appear to be enlarged?
    • Looking at my brain scan, does my brain appear to be Sagging?
  • Looking at my corpus callosum:
    • Does there appear to be a depression?
    • Is there an inferior pointing of the splenium?

If he/she answers affirmatively to any of the above S.E.E.P.S. questions, ask: 

  • What should be done to find/repair a potential leak?
  • Are you aware that it is common for CSF Leaks to not show up on MRI?
  • Are you willing to do a CT Myelogram and/or a digital subtraction myelogram, if I develop symptoms of a leak and none can be found on MRI?
  • Are you aware that it can often take multiple epidural blood patches to try and seal a leak, and sometimes when a blood patch fails to work, a surgical dural repair might be necessary?

Intracranial Hypertension (high pressure) Questions:
*Article to help you understand Intracranial Hypertension prior to your appointment.
If you have SYMPTOMS OF HIGH INTRACRANIAL PRESSURE, we recommend asking the following questions:

  • Looking at my brain scan, do I have cerebrospinal fluid in my sella turcica (Empty Sella Syndrome)?
  • Looking at my brain scan, do you see any evidence of my optic nerves are swollen (papilledema)?
    • If so, should I be referred to a neuro-ophthalmologist?
  • Looking at my brain scan, do my lateral ventricles appear small or flattened?
    • If so, do I need to have my pressures checked?
      • If yes, are you aware of the risks of developing a CSF Leak from a lumbar puncture?
    • What are the symptoms of a CSF Leak, should one develop?
      • What is your plan of action if I should develop these leak symptoms?
      • Are you aware that it is common for CSF Leaks to not show up on MRI?
      • Are you willing to do a CT Myelogram if I develop symptoms of a leak, and none can be found on MRI?
    • Should a leak be found, are you aware that it can often take multiple epidural blood patches to try and seal a leak?

Tethered Cord Questions: 
*Article to help you understand Tethered Cord: Sorry, Coming Soon.
If you have SYMPTOMS OF TETHERED CORD, we recommend asking the following questions:

  • Looking at my brain/cervical scan, does my brainstem appear to be elongated?
  • Looking at my cervical scan, does my spinal cord appear to be stretched?
  • Looking at my lumbar scan, does my conus reach my mid/low L2?
  • Looking at my thoracic and lumbar scan, does my spinal cord appear to be pulling to the back, or one particular side?
    • If so, should we do a prone MRI to see if it has actually adhered to that side?
  • Looking at my lumbar scan, do I appear to have fatty tissue inside the epidermis?
    • If the answer to any of these questions is affirmative, do you suspect that I have a tethered spinal cord?
    • If so, should we plan for a Tethered Cord Release before or soon after decompression surgery, so the likelihood of a failed decompression is reduced?
    • If I have urological issues, can I get a referral for urodynamic testing to rule out any other potential causes of my urological issues?

Craniocervical Instability (CCI) & Atlantoaxial Instability (AAI):
*Article to help you understand CCI & AAI prior to your appointment.
If you have SYMPTOMS OF CRANIOCERVICAL INSTABILITY or SYMPTOMS OF ATLANTOAXIAL INSTABILITY, we recommend asking the following questions:

  • Looking at my brain/cervical scans, what are the measurements of my clivoaxial angle, Grabb-Oakes, and Harris Measurements?
  • Do these measurements meet the diagnostic criteria for Craniocervical Instability?
  • Looking at my flexion and extension imaging, how many millimeters of translation are there between flexion and extension?
  • Does Chamberlain’s Line cross my odontoid? If so, does it cross at a level that would indicate Basilar Invagination?
  • Looking at my rotational imaging, what is the percentage of uncovering of the right and left articular facets on rotation?
  • Do the percentages from my rotational imaging meet the diagnosis criteria for Atlantoaxial Instability?

IF A DIAGNOSIS CRITERIA IS MET IN ANY OF THE ABOVE, WE STRONGLY RECOMMEND THAT YOU WAIT ON DECOMPRESSION AND PURSUE THE TREATMENT OF SAID CONDITION(S) AND THAT OF EHLERS-DANLOS SYNDROME, AS EACH OF THESE CONDITIONS CAN BE PATHOLOGICAL TO AN ACQUIRED CHIARI AND EACH IS A STRONG INDICATOR THAT A CONNECTIVE TISSUE PROBLEM EXISTS. 

*The questions in this article will periodically change as we are able to expand our recommended questions.


*Original version released September 2018, revised 2023.


INGREDIENTS:

Blueberry Balsamic Vinaigrette:

    • ½ cup fresh blueberries
    • ¼ cup aged balsamic vinegar
    • 2 teaspoons honey
    • ¼ cup avocado oil or light olive oil
    • ¼ tsp sea salt
    • ¼ tsp ground black pepper
    • ¼ teaspoon onion powder
    • ½ tablespoon whole grain Dijon mustard

Walnut-Crusted Chicken:

    • 2 cups walnuts
    • ½ tsp onion powder
    • ½ tsp garlic powder
    • ½ tsp sea salt
    • ½ tsp ground black pepper
    • 2 eggs, whisked with 1 T water
    • 2 large boneless, skinless chicken breasts
    • 2 TBSP olive, coconut or avocado oil

Salad:

    • 2 cups kale, washed, ribs removed, and roughly chopped
    • 4 cups 50/50 Spinach/Spring Mix salad greens
    • 8 radishes, thinly sliced
    • ½ cucumber, sliced into half moons
    • ¼ red onion, thinly sliced
    • ½ cup fresh blueberries
    • 1 medium carrot, shaved with a vegetable peeler or grated with a cheese grater
    • 1 medium avocado, sliced

DIRECTIONS:

In a blender, combine all dressing ingredients. Blend on high speed about 20 seconds, or until dressing is smooth and emulsified. Taste dressing and add more honey if it is too tart. The sweetness may vary depending upon the ripeness of your blueberries and the quality of your balsamic vinegar. Set aside at room temperature.

Place walnuts in a food processor and pulse until walnuts are ground, resembling course breadcrumbs. Avoid the temptation to leave the food processor on high, as this can result in a nut butter. Mix ground walnuts, onion and garlic powders, salt and pepper in a medium bowl or pie plate. In a separate medium bowl or pie plate, whisk together eggs and water.

Cut each chicken breast in half by thickness by laying the breast on a cutting board and pressing down on it with the palm of one hand. Using a chef’s knife in your other hand, hold the blade parallel to the cutting board and slice through the thickness of the breast, using a sawing motion. Repeat with the other chicken breast. You should now have four fairly thin chicken cutlets. Pat them dry with a paper towel.

Heat your chosen cooking oil on medium heat in a large, nonstick skillet. If your skillet is not large enough to accommodate all four cutlets, use half the oil at a time and work in two batches. Dip each cutlet in the egg wash, then the walnut mixture, pressing the walnuts onto the chicken. Place chicken in heated pan and cook approximately 3-4 minutes on each side, until walnut coating is deep golden brown and chicken is cooked through. Remove to a CLEAN cutting board to rest. Allow to rest and cool for five minutes, then cut into ½-inch slices.

While chicken is resting, assemble your salad, by combining all the ingredients except avocado in a large bowl. Divide the salad into four bowls and top each bowl with a sliced walnut-crusted chicken cutlet and ¼ of the sliced avocado. Drizzle prepared vinaigrette over chicken and salad and serve immediately. Leftover dressing can be stored in the refrigerator, but will be best if you let it return to room temperature before serving.

Read More

When I was first diagnosed with Chiari Malformation, I believed everything that my neurosurgeon told me. I was originally diagnosed with a Chiari 1 Malformation. I was told that it was congenital and due to my mother either using drugs or not getting proper prenatal care, which was crushing to hear, but not all that unlikely since I was born in the early 1970s. Little did I know, that these assumptions weren’t based on my findings, but on what textbooks have said since before the advent of the MRI in the early 1980s. Sadly, the percentage of Chiari patients that are given these same faulty assumptions remains near 100%. It didn’t take much time after my decompression surgery for me to realize, that it wasn’t quite as easy or cut-and-dry as it had been made out to be. When you have a connective tissue disorder, that is the root cause behind your Chiari diagnosis, the risk of postoperative complications is high, especially when pathological conditions went undiagnosed and untreated when the decompression was done. The difficulties of having a genetic mutation that can cause problems throughout your entire body, can make a patient seem like a hypochondriac, and that is exactly what most doctors think when they have a subpar understanding of Ehlers-Danlos Syndromes. When something goes wrong structurally, it can cause a cascading effect that manifests throughout the body. We go into the Chiari fight understanding that something is wrong with our brain and neck, but when it crosses over to problems with the autonomic nervous system (for instance), we don’t realize that the continued compression on our brainstem is why our hearts are now beating so fast, why we are now so short of breath, or why we are having fainting spells. We find ourselves wishing for someone, or a panel of experts to help us navigate through it all. While it is still far from the panel that we really need, Palliative Care can offer help with some essentials.

What is Palliative Care?

Palliative Care (pronounced “pal-lee-uh-tiv” care) is a subspecialty of medical care, where an interdisciplinary team of professionals (both medical and social) are committed to helping provide “relief from symptoms and stress” for patients with serious, life-altering illnesses, and their families. [1] Palliative Care is “supportive care,” by professionals committed to you as a patient with a serious illness! Your Palliative Care Team generally consists of a Palliative Doctor, a nurse, pharmacist, social worker, nutritionist, and a chaplain [2] (all as needed). Together, they will seek to:

  • Ease symptoms and/or help control pain to relieve suffering
  • Help improve your quality of life
  • Help coordinate with your care team
  • Assist with stress, fears, anxiety, and/or depression in the patient, caregiver, and/or family
  • Help you create a plan for end-of-life care (directives)


Benefits to Palliative Care:

  • Both Chiari Malformations and Ehlers-Danlos Syndromes are relatively complex. Both conditions can spur a vast array of symptoms. One of the objectives of your Palliative Team is to help you find a way to alleviate symptoms and/or help you with coping mechanisms through them.
  • Because Palliative Care is designed for patients with “serious” medical conditions, being accepted as Palliative Care patient, means that they recognize the seriousness of our condition. For those of us that have spent years/decades with our symptoms being dismissed, this alone is no small thing.
  • The CDC Guideline for Prescribing Opioids, as well as many of the state laws regarding the same, have exemptions for palliative patients (along with cancer and end-of-life patients). Doctors can still decide to discontinue prescriptions, taper your prescriptions, or require an “opioid contract,” but it will be 100% by their choice, and not due to CDC Guidelines and laws. Although, you may have to tell them that. [4]


Misconceptions Surrounding Palliative Care:

  • While it is outlined in the U.S. Department of Heath & Human Services (NIH) under the “National Institute on Aging” (NIA), there is NO AGE CRITERIA to qualify as a Palliative Care patient. [1]
  • While Palliative Care is frequently listed beside Hospice Care and/or End-of-Life Care, there is no national requirement for a patient to be in an end-of-life situation (or even an expected early demise). [1] Hospice care falls under palliative care, but palliative care expands beyond the scope of just hospice. Palliative care may begin at any stage of a serious illness. [2]
  • You can continue treatments (even curative treatments) with your personal doctor/specialist, while receiving palliative care. There is no “incurable condition” requirement for a serious condition under palliative care. [2][3] In fact, a patient can qualify and receive Palliative Care whether their illness is curable, chronic or life-threatening. [2]
  • You do not need to wait until your condition reaches a certain level of severity, you can start with Palliative Care at any stage of your illness. In fact, Palliative Care works best when it begins as early as possible in the illness, as some symptoms may be avoidable or more manageable if addressed early.
  • Palliative Care does not replace or override your pain management doctor, or any of our doctors for that matter. Instead, we give them permission to discuss our case with our medical professionals, so they can help coordinate our care, especially in regard to our pain/suffering and quality of life care.
  • Your Palliative Care Team will not consist of the medical specialists that we specifically need, but they can help navigate you to the type of doctor you may need and discuss these recommendations with your doctors.


Problems Surrounding Palliative Care:

  • Primary Care Doctors (who are supposed to be offering referrals to Palliative Care for their patients with serious medical conditions) often fail to fully understand the spectrum of Palliative Care. Because of their faulty understanding, most of us are never offered Palliative Care, and when we request it, we are often told that it is equivalent to hospice care or set aside for hospice patients, and therefore they believe that we do not qualify. THEY ARE WRONG!

  • Our medical professionals often fail to recognize just how “serious” of a condition and life-altering Chiari and EDS really are (on us as patients and on our families).
  • Not all insurance companies cover Palliative Care. Because some insurance companies fail to see the seriousness of our conditions, qualifying may be difficult. Private insurance and HMOs are more likely to offer Palliative Care. Different states have different policies regarding the level of Palliative Care (if any) they offer. [2] If cost concerns are an issue, the social worker on your Palliative Team can assist you in ways that might help you qualify. [3]


[wpedon id=”4396″ align=”center”]


References:

1. “What Are Palliative Care and Hospice Care?” U.S. Department of Health and Human Services, National Institute on Aging, 17 May, 2017. <https://www.nia.nih.gov/health/what-are-palliative-care-and-hospice-care>

2. “Frequently Asked Questions About Hospice and Palliative Care.” American Academy of Hospice and Palliative Medicine. <http://palliativedoctors.org/faq>

3. “Handout for Patients and Families.” Center to Advance Palliative Care. <https://getpalliativecare.org/handouts-for-patients-and-families/>

4. “CDC Guideline for Prescribing Opioids for Chronic Pain.” Centers for Disease Control and Prevention, National Center for Injury Prevention and Control, Division of Unintentional Injury Prevention. 29 Aug, 2017 <https://www.cdc.gov/drugoverdose/prescribing/guideline.html>

When a person suffers from a chronic condition, we sometimes equate our value to how we feel. Chiari, Ehlers-Danlos, CSF Leaks, Chronic Fatigue Syndrome, etc. all cause pain. Sometimes we tend to carry that pain along with us as baggage. If we carry our self-value as related to pain, we are more likely to let healthcare professionals bully us and eventually, all this baggage compromises the relationships that matter most to us. Well, it’s time to look deep inside ourselves and find our inner strength.

Take a step back and pretend for a moment that a loved one had the conditions you have. Imagine knowing all the struggles they have fought. Imagine them hoping for a diagnosis so that they could have a name to fight. Imagine them enduring countless appointments and procedures. Imagine them in pain and struggling to go to important events, so they are not letting people down. Imagine them doing hours and hours of research to find help. Now, stop for a moment and ask yourself a question. Would you call that person strong or weak? Really stop and think about it. They aren’t famous and probably not wealthy. I know what I would call them. I would call them the epitome of strength! I hope you would consider a loved one like that to be a super strong person too. Wouldn’t you have respect for them? Wouldn’t you wonder how they kept functioning and be in amazement of their abilities? Now stop again. This person we imagined as a loved one is now back to being YOU!!!

That’s right! YOU, with these chronic conditions, feeling as battered and bruised as you do, are like Superman or Superwoman. You have done more while enduring pain, than most people do that are completely healthy!

Now, how do you value your life? You should value your life as a beautiful person that finds strength deep down inside. You should find joy in small things and accept love that is given to us as someone that is deserving of such love. Let them love you and cherish the special moments you have in life. Value your health and fight for what you feel is the right treatment. Don’t be afraid to ask questions of your medical professionals and fight to get back and keep whatever quality of life that you can, because you matter! But we must learn to fight right! Not with fists or harsh words, but by articulating the extent of our pain at every level allotted to us!

When your doctor provides substandard care, he subjects himself/herself to a formal complaint. Misdiagnosis or delayed diagnosis that leads to incorrect treatment, delayed treatment, or no treatment at all, can cause you harm and is complaint worthy. Overprescribing, underprescribing, and failure to prescribe adequate treatment for your condition(s) are also grounds for a formal complaint.


 

Preparing to make your complaint(s):

• Calmly articulate your condition(s) and how difficult treatment has been on you and your family thus far.

• Explain the treatment options you have been presented with, the options you have tried and why they should not be considered efficient treatment for you, and why you feel that the option being declined to you is the best course of treatment for you personally.

• Directly ask the recipient at each level for help and express your desire to resolve the issue at their level.


Preparing to send your complaint:

• Write the department and/or division head and request a meeting with him/her about it.

• Write the members services of the hospital or medical group that you are a part of and request an internal review.

• If the internal review failed to bring about the action that you need, request an external review.

• File a complaint with the state medical board that the doctor is in. Be sure to provide all supporting evidence that you have. They will enter your complaint into database and review your case to determine if disciplinary action should be taken against your doctor. Even if the state medical board doesn’t agree with you, it will go on record and might be reviewed again when/if additional patients make similar complaints about that doctor.

• Contact your state legislators asking for their help. While they usually wont respond to you directly, they have state aides that are armed with lists of resources to help. If state laws are a reason behind the lack of treatment you are getting, let them know how these laws are having a negative impact on the quality of care that you are receiving in their state.

• Contact your federal legislators asking for help at a national level. You might feel intimidated, like they are not going to care about what is happening with a sick constituent, but the truth is that you are not the only patient experiencing these problems, and their ability to hear from multiple patients with similar problems can raise red flags. Federal legislators are officials paid to represent your state at a federal level. If federal laws are a reason behind the lack of treatment you are getting, let them know how these laws are having a negative impact on the quality of care that you are receiving.

• Write letters to all government agencies, such as the Centers for Disease Control (CDC), Federal Drug Administration (FDA), etc. They might not do anything specifically about your doctor, but they are responsible (at least in part) for many of the rules and regulations governing aspects of our care. Let them know how you’re doing under the policies their responsible for. 

• Write the United States Attorney General and the President of the United States and let them hear directly from you on how these laws, rules and regulations are affecting your health care.

The bottom line is, everything has been accomplished for Chiarians, has been done by us working together. They might not care about one letter, but how about tens of thousands? Let’s unite and fight for our rights to proper medical care, including proper pain relief, while we can!

You can do this! Together we C.A.N. do this!


[wpedon id=”4396″ align=”center”]

✕
Chiaribridges

FREE
VIEW