Born Different, but Not Knowing Why

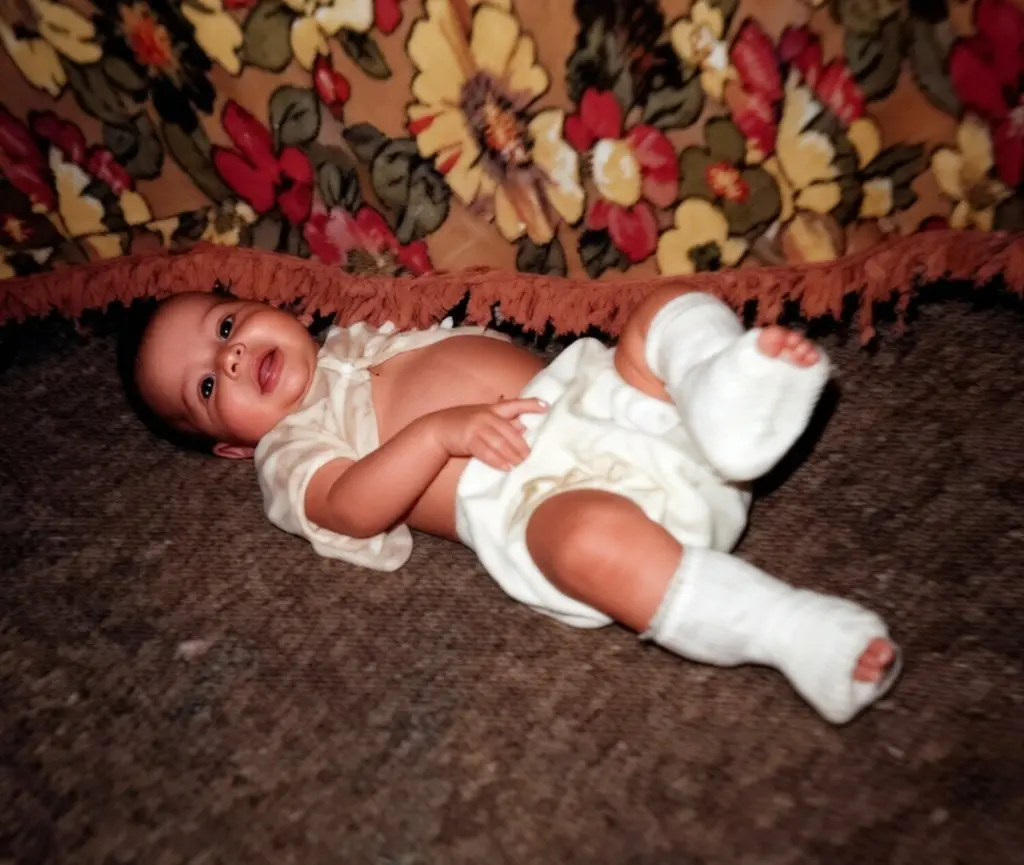
I was born into a body that was different from the beginning.

  • Clubfoot.
  • Left hip dysplasia.
  • Leg casts as an infant.

As an adolescent, I experienced severe growing pains, never realizing they might be connected to conditions that would take years to identify. Years passed. I lived life pain-free. 

By 2006, I was in the best shape of my life after losing 100 pounds through exercise and a low-carb diet. On May 9, 2006, I donated a kidney to my husband, Martin, an act of love I will never regret. We just celebrated our 20-year kidney transplant anniversary this year. 

At that time, I had not yet developed the debilitating symptoms of Chiari Malformation or Tethered Cord Syndrome (TCS). Then, in my 30s, everything changed.

2008: When the Symptoms Began

After riding a roller coaster in 2008, I immediately began experiencing symptoms that would eventually be associated with Chiari Malformation and TCS.

Brain imaging showed evidence of Chiari, but doctors didn’t interpret the findings in a way that led to answers. Because my cerebellar tonsillar herniation measured “only” 5 millimeters, doctors dismissed my symptoms as insignificant.

I knew something was wrong, but I struggled to get neurologists and neurosurgeons to take me seriously. Exhausted and frightened, I researched and advocated for myself until I finally found a specialist who understood.

Finding My Hero: Dr. John Oro

At 39, I found Dr. John Oro at the Colorado Chiari Institute. He diagnosed me with Chiari Malformation and Tethered Cord Syndrome.

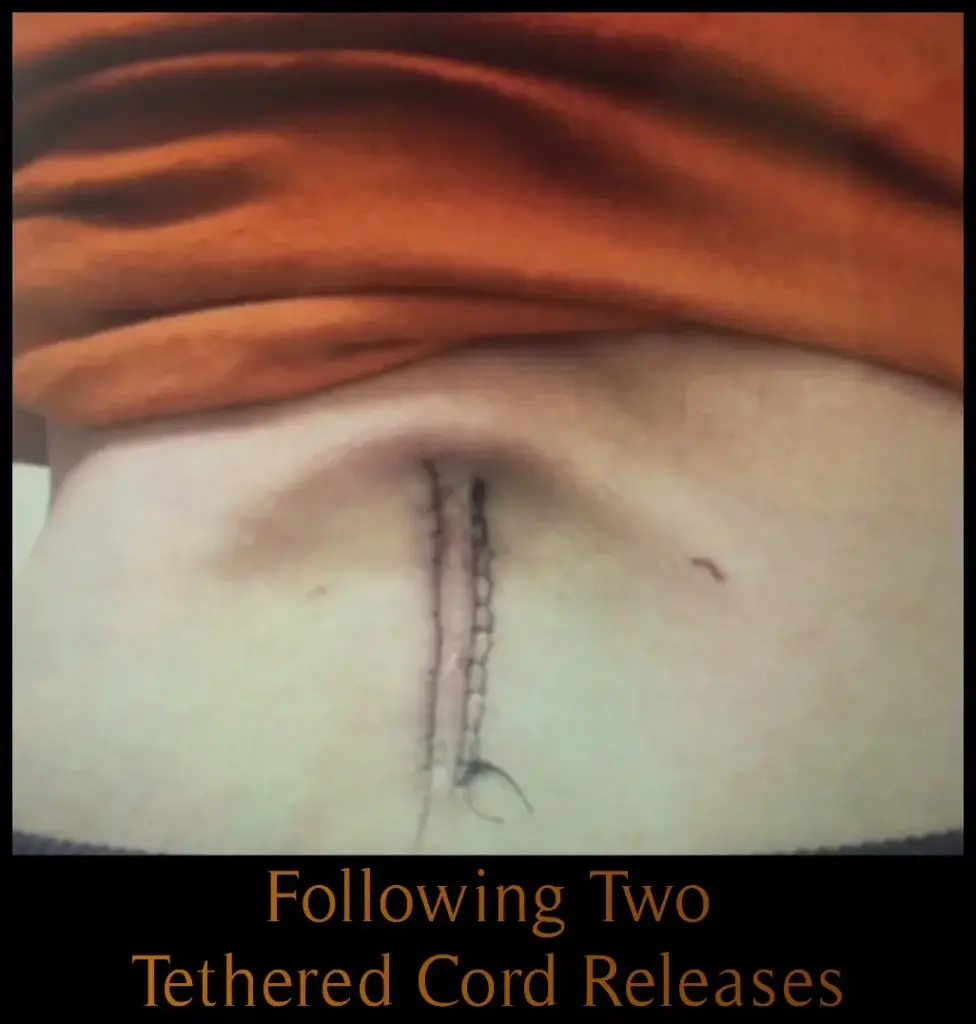
My TCS symptoms were more severe than my Chiari symptoms at the time, so in 2009, Dr. Oro performed my first spinal cord detethering surgery. For the first time, I felt understood.

Five Years Later: The Tethered Cord Returned

Approximately five years later, my spinal cord retethered, and my symptoms returned worse than before.

I traveled back to Colorado, where Dr. Oro performed another detethering surgery that lasted about four and a half hours. Afterward, I was able to “manage” my Chiari and TCS symptoms for a year.  

I hoped I could finally move forward, but my medical journey was far from over.
2016: The Crack in My Neck

In 2016, I heard and felt a crack in my neck. From that day forward, my Chiari symptoms became severe, and I began desperately seeking decompression surgery.

Dr. Oro had retired, so I had to find another specialist. Eventually, a UCLA neurosurgeon agreed to perform the procedure.

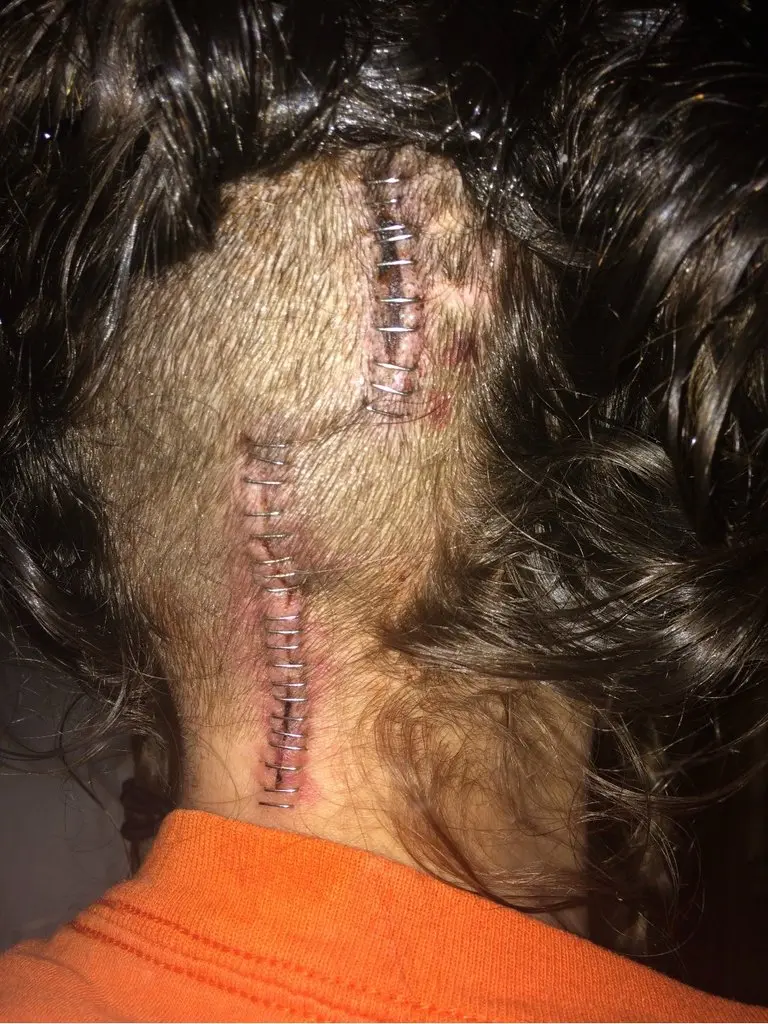
The six-hour surgery included cauterizing my cerebellar tonsils. Waking up was the most painful experience I had ever endured. I begged the medical staff to knock me out because the pain control was not working.

I eventually recovered, carrying the memory of that experience and 30 staples in my head. For approximately eight months, I felt some relief.

Then my symptoms returned.
The Clear Fluid: Discovering My Cranial CSF Leak

After those eight months, clear fluid began dripping from my nose, followed by horrific head pain. Local testing for a cranial cerebrospinal fluid (CSF) leak was negative.

Through my own research, I found Dr. Edward Hepworth in Colorado, a cranial ENT specialist who treats difficult-to-diagnose CSF leaks. After waiting eight months for an appointment, I traveled to Colorado and underwent a 48-hour hospital admission for a pledget study.

The leak was finally found.

In 2019, Dr. Hepworth repaired my cranial leak. During that same trip, I also had a hole in my heart closed.  

Hypermobile Ehlers-Danlos Syndrome: Connecting My Issues

In 2021, I was finally diagnosed with Hypermobile Ehlers-Danlos Syndrome (hEDS), a connective tissue disorder affecting joints, ligaments, and other tissues.

I had suspected hEDS for years, but obtaining a diagnosis was extremely difficult. The diagnosis helped connect some of the many conditions I had experienced, including clubfoot, hip dysplasia, Chiari symptoms, TCS, and my cranial CSF leak.

Each diagnosis added clarity, but none erased the pain or the years I had spent fighting to be heard.

Eighteen Surgeries: Learning the Language of Hospitals

Over the years, I have undergone 18 surgeries.

I learned the smell of hospitals, the sound of monitors, the fear before anesthesia, and the vulnerability of waking up unsure what pain would come next. I also learned how to navigate medical care and advocate for myself.

For years, I thought brain surgery was the worst pain I would ever experience.

I was wrong.

2020: The Day I Was Floxed

In 2020, I was hospitalized for an infected cyst below my parotid gland. I received Ciprofloxacin followed by intravenous Levaquin (levofloxacin), both fluoroquinolone antibiotics, over two days.

The day I was discharged, my life changed.

Severe, systemic pain began almost immediately. It spread throughout my body, making every movement difficult. I could barely walk, couldn’t tolerate anyone touching my feet, and couldn’t wear shoes.

I had survived brain surgery and spinal cord surgeries, so I knew what pain and recovery felt like. This was different. Surgery has an ending, an incision that heals, and the hope of recovery. Being floxed became something I had to live inside.

I felt like a walking corpse. At times, the suffering was so overwhelming that I wanted to die.

A Year of Medical Trauma and Gaslighting

For the next year, I lived in severe pain without answers. Doctors referred me to behavioral health because they could not explain my physical symptoms.

Being unable to walk normally, tolerate touch, or wear shoes while feeling disbelieved caused profound emotional harm. The experience became medical PTSD.

Then I learned about Fluoroquinolone Associated Disability, commonly known as FQAD. For the first time, I found information that connected my symptoms to the antibiotics I had received.

I finally had a name for what I believed had happened to me.

Spending Our Savings to Find Relief

My husband and I spent $23,000 of our savings on a five-day IV treatment followed by stem cell therapy. We made that decision because I was suffering so severely and needed a chance at a better quality of life.

I believe those treatments helped keep me from ending up in a wheelchair, but they did not restore my former life.

I am disabled now and live with severe pain every day. The woman I was before 2020 is not the woman I am today, and I continue to grieve what I have lost while learning to live with my body as it is.

January 2026: Finally Having a Diagnosis 

In January 2026, three months after the CDC approved a new ICD-10 diagnosis code for FQAD, I met with my primary care doctor to pursue official documentation of the long-term effects I had experienced after receiving fluoroquinolones.

My medical records now include: T36.AX5 — Adverse effect of Fluoroquinolone antibiotics, sequela (long-term effects).

After years of pain, confusion, and dismissal, I finally had validation, a diagnosis, and a name for what happened to me. 💜

This documentation does not erase my pain or restore my former life, but it matters. I wish I had known about the potential risks before receiving those medications. I wish I had been warned that serious, prolonged, and disabling reactions were possible.

I cannot change what happened, but I can tell my story.
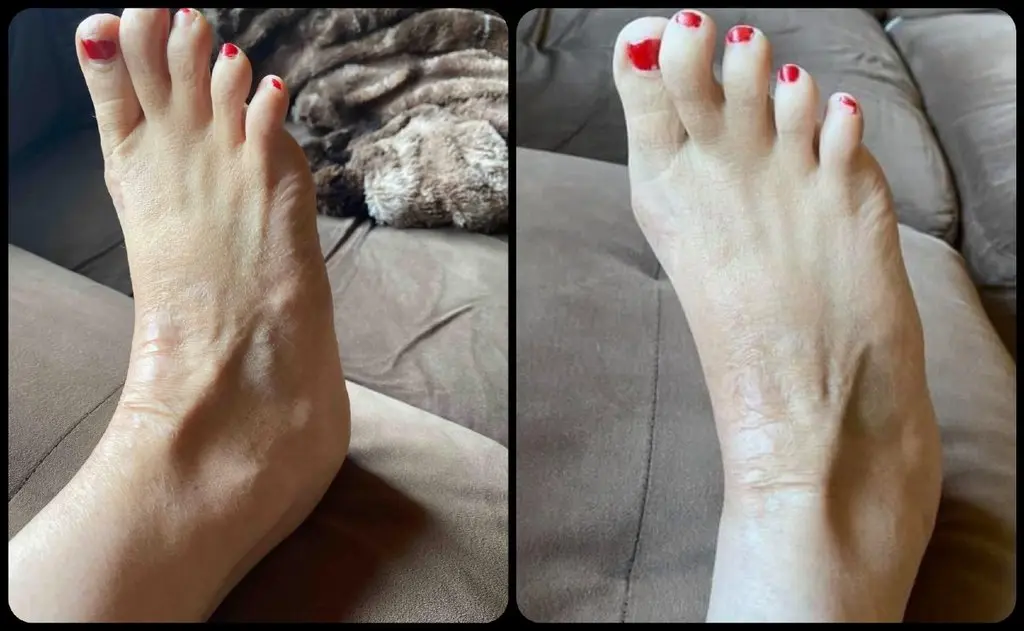
What Fluoroquinolones Did to My Right Foot

My right foot has become a visible reminder of the physical suffering I have experienced since receiving fluoroquinolones.

I want people to understand that serious adverse drug reactions can extend far beyond a hospital stay. When symptoms begin suddenly and pain becomes disabling, people deserve to be listened to and taken seriously.

I cannot undo what happened to my body, but I can raise awareness about fluoroquinolone-associated disability and encourage others to learn about the potential risks of these medications and seek medical care if concerning symptoms develop.

Many people are suffering, searching for answers, and struggling to be believed.

I am a daughter, a wife, a mother, a nana, and a woman who has survived experiences I never imagined facing.

I am more than my diagnoses, my surgeries, and the pain I live with.

If sharing helps someone find answers or feel understood, I will keep sharing.

Because after everything I have endured, I still have a voice, and I intend to use it!


*I dedicate this story to my family, my greatest blessings and my strongest support system throughout this difficult journey. To my husband, Martin, and our three beautiful daughters: Thank you for loving me through the pain, the tears, and the setbacks. Thank you for standing beside me, holding me up when I felt like I was falling apart, and loving me through the long haul. I am forever grateful for each of you. To Mom and Dad, and to my Wolf Pack, thank you for being part of my journey and for the love, strength, and support you have given me along the way. To Dr. Mark Ghalili, who saved my life. And to my fellow Floxies and everyone suffering from Fluoroquinolone Toxicity: this story is for you, too. For those living with invisible pain, grieving the lives they once knew, fighting to be believed, and finding the strength to keep going. You are not alone. Your pain matters, your story matters, and your voice deserves to be heard.

To read more on the safety issues surrounding fluoroquinolones, check out our article: “When “Safe and Effective” Fails: Fluoroquinolones and the Erosion of Public Trust.”


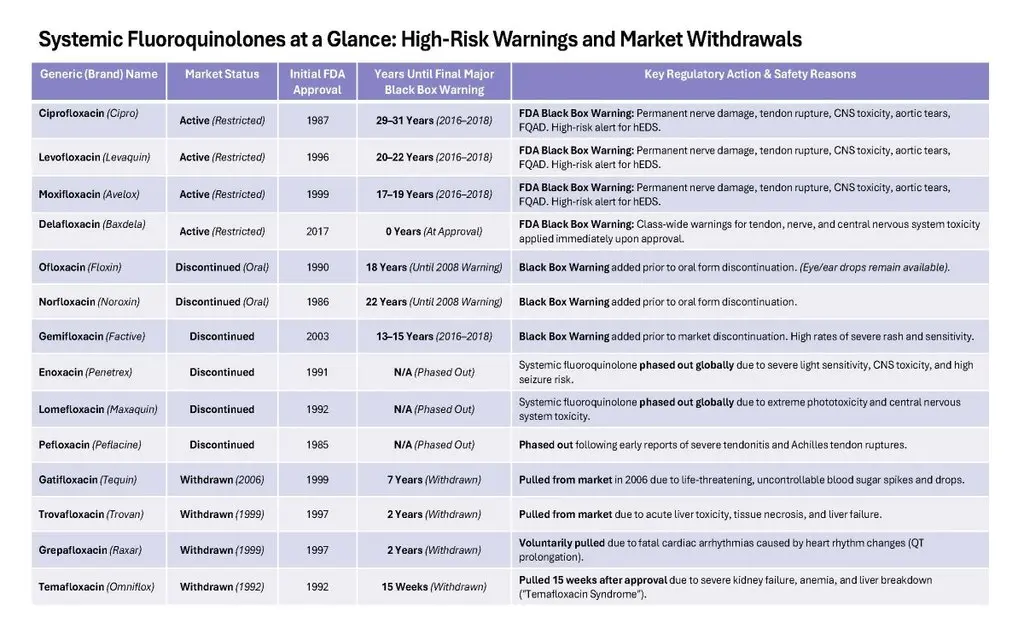
For decades, patients seeking medical care trusted a simple, foundational principle of medicine: First, do no harm. When a doctor handed down a prescription, patients assumed the medication had been thoroughly vetted for safety. Adverse reactions were presented as statistically negligible cases—unintended side effects in the march of modern medical progress.

Yet for millions of patients, especially those living with connective tissue disorders like Hypermobile Ehlers-Danlos Syndrome (hEDS) or Chiari Malformation, that trust has been shattered.

The history of fluoroquinolone antibiotics stands as a stark case study in institutional failure. Marketed for decades as routine frontline treatments, these powerful drugs were later retroactively hit with severe Black Box warnings. This story reveals a deeper crisis: the ongoing breakdown of public faith in corporate medicine.

The Rise of Fluoroquinolones: Profit Over Caution

Introduced widely in the 1980s and 1990s, fluoroquinolones were hailed as broad-spectrum miracle drugs. The class includes well-known medications like Ciprofloxacin (Cipro), Levofloxacin (Levaquin), and Moxifloxacin (Avelox). They were fast-acting, effective, and convenient.

Driven by aggressive pharmaceutical marketing, doctors routinely prescribed them for minor, uncomplicated issues: sinus infections, mild UTIs, bronchitis, and ear infections. Millions of prescriptions were written every year.

Behind the scenes, however, a troubling reality emerged. Early clinical trials—often funded and designed by the drug manufacturers themselves—were never structured to catch delayed, long-term, or multi-systemic damage. As these drugs dominated the market, reports of life-altering side effects began piling up in patient communities around the world.

A History of Withdrawals and Delayed Warnings

For years, regulatory agencies insisted that severe reactions were statistically negligible. Yet the safety history of fluoroquinolones tells a different story—one marked by sudden market withdrawals and late, reactive warnings.

Decades to Acknowledge the Damage

Decades of fierce patient advocacy, ruined lives, and overwhelming real-world evidence were needed for the FDA to intervene. Between 2008 and 2018, the agency issued a series of increasingly severe Black Box warnings—the strongest safety alert short of a total ban:

  • 2008: Warning added for an increased risk of severe tendinitis and tendon rupture.
  • 2013: Warning updated to explicitly state that nerve damage (peripheral neuropathy) can happen rapidly and become permanent.
  • 2016: The FDA stated that for simple infections (like sinus or mild bladder infections), the risks of fluoroquinolones outweigh the benefits, advising doctors to use them strictly as a last resort.
  • 2018: Warning issued specifically for high-risk populations—including individuals with Ehlers-Danlos Syndrome, hypermobility, or aortic aneurysms—due to the risk of aortic tears, tissue breakdown, and permanent disability.

The Hidden Peril for hEDS and Chiari Patients

For patients living with Hypermobile Ehlers-Danlos Syndrome (hEDS) or structural conditions like Chiari Malformation, these delayed warnings came at a devastating cost.

hEDS is a connective tissue disorder caused by defective collagen. Collagen is the physical scaffolding that holds together tendons, ligaments, blood vessels, and fascia throughout the body.

Fluoroquinolones interfere with collagen production and break down connective tissue. Giving a collagen-degrading antibiotic to a person whose body already struggles with fragile collagen is a dangerous combination. The result is often Fluoroquinolone-Associated Disability (FQAD)—a severe syndrome marked by widespread joint damage, tendon tears, burning nerve pain, and profound loss of mobility.

To make matters worse, patients who experienced these sudden post-antibiotic breakdowns were routinely dismissed. Because standard bloodwork and imaging rarely catch subtle cellular damage, patients were gaslit, told their symptoms were “just anxiety,” or referred to mental health providers. They were left to suffer both physical destruction and severe medical trauma.

How Medical Hegemony Shattered Public Trust

The tragedy of fluoroquinolones is not an isolated mistake or a single company’s oversight. It reveals a repeating pattern within modern healthcare:

  1. Declarations of Safety: A pharmaceutical product is launched, backed by industry-sponsored trials, and declared safe and necessary for broad populations.
  2. Suppression of Early Warnings: Patients and independent clinicians who raise early alarms about side effects are ignored, dismissed as “anecdotal,” or accused of spreading misinformation.
  3. A Slow, Reluctant Retreat: Years or decades later—after thousands of lives have been disrupted—institutions quietly update labels, attach Black Box warnings, or pull drugs off shelves, rarely acknowledging the damage done.
  4. The Informed Consent Loophole: Even after Black Box warnings are issued, doctors are not legally required to verbally inform patients of these warnings before handing down a prescription. Patients are left to discover the risks on their own—often only after irreversible harm has already occurred.

When public health institutions demand uncritical trust while enforcing rigid corporate consensus, they destroy the foundation of real science: open debate, continuous reassessment, and listening to patient outcomes.

When guidance shifts from “safe and routine” to “risk of permanent disability”—and patients are kept in the dark at the exam table—public skepticism is not irrational. It is a logical tool for self-preservation. Patients can no longer afford to blindly trust institutions or providers that prioritize commercial convenience over genuine patient safety.

What You Can Do to Protect Yourself

If you or a loved one live with hEDS, hypermobility, or any connective tissue disorder:

  • Always Disclose Your Diagnosis: Make sure every doctor, surgeon, and pharmacist knows you have a connective tissue condition before you accept any new prescription.
  • Ask for Alternatives: Unless you face a life-threatening infection with no other option, request a safer, non-fluoroquinolone antibiotic.
  • Listen to Your Body: If a medication causes sudden, burning nerve pain, joint stiffness, or extreme weakness, seek medical evaluation immediately and advocate for your safety.

Science is an ongoing process of testing, learning, and refining—not an unquestionable doctrine. By speaking up, sharing real experiences, and demanding accountability, patients are leading the way toward a safer medical system.

Real progress in medicine will not come from top-down decrees or silencing debate. It comes from empowered patients, transparent science, and true informed consent.

Surviving Chiari Malformation, tethered cord syndrome, and FQAD taught Michelle Nieves that staying silent is not an option. Her journey exposes why independent advocacy like Chiari Bridges is indispensable—it pushes back against dogmatic diagnostic criteria, shines a light on undocumented drug toxicities, and demands that medical institutions prioritize real-world patient outcomes over corporate consensus. Read her story, “The Michelle Nieves Story – Reclaiming My Voice: hEDS, Chiari, and the Hidden Dangers of Fluoroquinolones.”

When I was first diagnosed with Chiari Malformation, I believed everything that my neurosurgeon told me. I was originally diagnosed with a Chiari 1 Malformation. I was told that it was congenital and due to my mother either using drugs or not getting proper prenatal care, which was crushing to hear, but not all that unlikely since I was born in the early 1970s. Little did I know, that these assumptions weren’t based on my findings, but on what textbooks have said since before the advent of the MRI in the early 1980s. Sadly, the percentage of Chiari patients that are given these same faulty assumptions remains near 100%. It didn’t take much time after my decompression surgery for me to realize, that it wasn’t quite as easy or cut-and-dry as it had been made out to be. When you have a connective tissue disorder, that is the root cause behind your Chiari diagnosis, the risk of postoperative complications is high, especially when pathological conditions went undiagnosed and untreated when the decompression was done. The difficulties of having a genetic mutation that can cause problems throughout your entire body, can make a patient seem like a hypochondriac, and that is exactly what most doctors think when they have a subpar understanding of Ehlers-Danlos Syndromes. When something goes wrong structurally, it can cause a cascading effect that manifests throughout the body. We go into the Chiari fight understanding that something is wrong with our brain and neck, but when it crosses over to problems with the autonomic nervous system (for instance), we don’t realize that the continued compression on our brainstem is why our hearts are now beating so fast, why we are now so short of breath, or why we are having fainting spells. We find ourselves wishing for someone, or a panel of experts to help us navigate through it all. While it is still far from the panel that we really need, Palliative Care can offer help with some essentials.

What is Palliative Care?

Palliative Care (pronounced “pal-lee-uh-tiv” care) is a subspecialty of medical care, where an interdisciplinary team of professionals (both medical and social) are committed to helping provide “relief from symptoms and stress” for patients with serious, life-altering illnesses, and their families. [1] Palliative Care is “supportive care,” by professionals committed to you as a patient with a serious illness! Your Palliative Care Team generally consists of a Palliative Doctor, a nurse, pharmacist, social worker, nutritionist, and a chaplain [2] (all as needed). Together, they will seek to:

  • Ease symptoms and/or help control pain to relieve suffering
  • Help improve your quality of life
  • Help coordinate with your care team
  • Assist with stress, fears, anxiety, and/or depression in the patient, caregiver, and/or family
  • Help you create a plan for end-of-life care (directives)


Benefits to Palliative Care:

  • Both Chiari Malformations and Ehlers-Danlos Syndromes are relatively complex. Both conditions can spur a vast array of symptoms. One of the objectives of your Palliative Team is to help you find a way to alleviate symptoms and/or help you with coping mechanisms through them.
  • Because Palliative Care is designed for patients with “serious” medical conditions, being accepted as Palliative Care patient, means that they recognize the seriousness of our condition. For those of us that have spent years/decades with our symptoms being dismissed, this alone is no small thing.
  • The CDC Guideline for Prescribing Opioids, as well as many of the state laws regarding the same, have exemptions for palliative patients (along with cancer and end-of-life patients). Doctors can still decide to discontinue prescriptions, taper your prescriptions, or require an “opioid contract,” but it will be 100% by their choice, and not due to CDC Guidelines and laws. Although, you may have to tell them that. [4]


Misconceptions Surrounding Palliative Care:

  • While it is outlined in the U.S. Department of Heath & Human Services (NIH) under the “National Institute on Aging” (NIA), there is NO AGE CRITERIA to qualify as a Palliative Care patient. [1]
  • While Palliative Care is frequently listed beside Hospice Care and/or End-of-Life Care, there is no national requirement for a patient to be in an end-of-life situation (or even an expected early demise). [1] Hospice care falls under palliative care, but palliative care expands beyond the scope of just hospice. Palliative care may begin at any stage of a serious illness. [2]
  • You can continue treatments (even curative treatments) with your personal doctor/specialist, while receiving palliative care. There is no “incurable condition” requirement for a serious condition under palliative care. [2][3] In fact, a patient can qualify and receive Palliative Care whether their illness is curable, chronic or life-threatening. [2]
  • You do not need to wait until your condition reaches a certain level of severity, you can start with Palliative Care at any stage of your illness. In fact, Palliative Care works best when it begins as early as possible in the illness, as some symptoms may be avoidable or more manageable if addressed early.
  • Palliative Care does not replace or override your pain management doctor, or any of our doctors for that matter. Instead, we give them permission to discuss our case with our medical professionals, so they can help coordinate our care, especially in regard to our pain/suffering and quality of life care.
  • Your Palliative Care Team will not consist of the medical specialists that we specifically need, but they can help navigate you to the type of doctor you may need and discuss these recommendations with your doctors.


Problems Surrounding Palliative Care:

  • Primary Care Doctors (who are supposed to be offering referrals to Palliative Care for their patients with serious medical conditions) often fail to fully understand the spectrum of Palliative Care. Because of their faulty understanding, most of us are never offered Palliative Care, and when we request it, we are often told that it is equivalent to hospice care or set aside for hospice patients, and therefore they believe that we do not qualify. THEY ARE WRONG!

  • Our medical professionals often fail to recognize just how “serious” of a condition and life-altering Chiari and EDS really are (on us as patients and on our families).
  • Not all insurance companies cover Palliative Care. Because some insurance companies fail to see the seriousness of our conditions, qualifying may be difficult. Private insurance and HMOs are more likely to offer Palliative Care. Different states have different policies regarding the level of Palliative Care (if any) they offer. [2] If cost concerns are an issue, the social worker on your Palliative Team can assist you in ways that might help you qualify. [3]


[wpedon id=”4396″ align=”center”]


References:

1. “What Are Palliative Care and Hospice Care?” U.S. Department of Health and Human Services, National Institute on Aging, 17 May, 2017. <https://www.nia.nih.gov/health/what-are-palliative-care-and-hospice-care>

2. “Frequently Asked Questions About Hospice and Palliative Care.” American Academy of Hospice and Palliative Medicine. <http://palliativedoctors.org/faq>

3. “Handout for Patients and Families.” Center to Advance Palliative Care. <https://getpalliativecare.org/handouts-for-patients-and-families/>

4. “CDC Guideline for Prescribing Opioids for Chronic Pain.” Centers for Disease Control and Prevention, National Center for Injury Prevention and Control, Division of Unintentional Injury Prevention. 29 Aug, 2017 <https://www.cdc.gov/drugoverdose/prescribing/guideline.html>

When a person suffers from a chronic condition, we sometimes equate our value to how we feel. Chiari, Ehlers-Danlos, CSF Leaks, Chronic Fatigue Syndrome, etc. all cause pain. Sometimes we tend to carry that pain along with us as baggage. If we carry our self-value as related to pain, we are more likely to let healthcare professionals bully us and eventually, all this baggage compromises the relationships that matter most to us. Well, it’s time to look deep inside ourselves and find our inner strength.

Take a step back and pretend for a moment that a loved one had the conditions you have. Imagine knowing all the struggles they have fought. Imagine them hoping for a diagnosis so that they could have a name to fight. Imagine them enduring countless appointments and procedures. Imagine them in pain and struggling to go to important events, so they are not letting people down. Imagine them doing hours and hours of research to find help. Now, stop for a moment and ask yourself a question. Would you call that person strong or weak? Really stop and think about it. They aren’t famous and probably not wealthy. I know what I would call them. I would call them the epitome of strength! I hope you would consider a loved one like that to be a super strong person too. Wouldn’t you have respect for them? Wouldn’t you wonder how they kept functioning and be in amazement of their abilities? Now stop again. This person we imagined as a loved one is now back to being YOU!!!

That’s right! YOU, with these chronic conditions, feeling as battered and bruised as you do, are like Superman or Superwoman. You have done more while enduring pain, than most people do that are completely healthy!

Now, how do you value your life? You should value your life as a beautiful person that finds strength deep down inside. You should find joy in small things and accept love that is given to us as someone that is deserving of such love. Let them love you and cherish the special moments you have in life. Value your health and fight for what you feel is the right treatment. Don’t be afraid to ask questions of your medical professionals and fight to get back and keep whatever quality of life that you can, because you matter! But we must learn to fight right! Not with fists or harsh words, but by articulating the extent of our pain at every level allotted to us!

When your doctor provides substandard care, he subjects himself/herself to a formal complaint. Misdiagnosis or delayed diagnosis that leads to incorrect treatment, delayed treatment, or no treatment at all, can cause you harm and is complaint worthy. Overprescribing, underprescribing, and failure to prescribe adequate treatment for your condition(s) are also grounds for a formal complaint.


 

Preparing to make your complaint(s):

• Calmly articulate your condition(s) and how difficult treatment has been on you and your family thus far.

• Explain the treatment options you have been presented with, the options you have tried and why they should not be considered efficient treatment for you, and why you feel that the option being declined to you is the best course of treatment for you personally.

• Directly ask the recipient at each level for help and express your desire to resolve the issue at their level.


Preparing to send your complaint:

• Write the department and/or division head and request a meeting with him/her about it.

• Write the members services of the hospital or medical group that you are a part of and request an internal review.

• If the internal review failed to bring about the action that you need, request an external review.

• File a complaint with the state medical board that the doctor is in. Be sure to provide all supporting evidence that you have. They will enter your complaint into database and review your case to determine if disciplinary action should be taken against your doctor. Even if the state medical board doesn’t agree with you, it will go on record and might be reviewed again when/if additional patients make similar complaints about that doctor.

• Contact your state legislators asking for their help. While they usually wont respond to you directly, they have state aides that are armed with lists of resources to help. If state laws are a reason behind the lack of treatment you are getting, let them know how these laws are having a negative impact on the quality of care that you are receiving in their state.

• Contact your federal legislators asking for help at a national level. You might feel intimidated, like they are not going to care about what is happening with a sick constituent, but the truth is that you are not the only patient experiencing these problems, and their ability to hear from multiple patients with similar problems can raise red flags. Federal legislators are officials paid to represent your state at a federal level. If federal laws are a reason behind the lack of treatment you are getting, let them know how these laws are having a negative impact on the quality of care that you are receiving.

• Write letters to all government agencies, such as the Centers for Disease Control (CDC), Federal Drug Administration (FDA), etc. They might not do anything specifically about your doctor, but they are responsible (at least in part) for many of the rules and regulations governing aspects of our care. Let them know how you’re doing under the policies their responsible for. 

• Write the United States Attorney General and the President of the United States and let them hear directly from you on how these laws, rules and regulations are affecting your health care.

The bottom line is, everything has been accomplished for Chiarians, has been done by us working together. They might not care about one letter, but how about tens of thousands? Let’s unite and fight for our rights to proper medical care, including proper pain relief, while we can!

You can do this! Together we C.A.N. do this!


[wpedon id=”4396″ align=”center”]

TORTURE EXISTS IN 2018 IN THE US AND IT IS SPREADING GLOBALLY. IT’S HAPPENING IN MEDICAL FACILITIES. IT’S HAPPENING TO CHRONIC PAIN PATIENTS (CPP), PEOPLE WHO ARE RECOVERING FROM SURGERY AND TRAUMATIC INJURY AND PEOPLE WITH PAINFUL, INCURABLE DISEASES. THE GENERAL ASSEMBLY OF THE UNITED NATIONS HAS GONE ON RECORD STATING THAT, “UNTREATED PAIN IS TANTAMOUNT TO TORTURE OR CRUEL, INHUMAN OR DEGRADING TREATMENT OR PUNISHMENT.” [1] BY DENYING PAIN CONTROL TO PATIENTS WITH ACUTE OR CHRONIC PAIN, WE ARE LOSING A BASIC HUMAN RIGHTS ISSUE.

Now is the time for us ALL to UNITE and take ACTION!

“Opioid Crisis” is a new buzz term being overused by national news and government officials to evoke a negative feeling about a drug that was created for helping people. The definition of “crisis” by Merriam-Webster dictionary is partially defined as “an unstable or crucial time or state of affairs in which a decisive change is impending; especially: one with the distinct possibility of a highly undesirable outcome.”

There is much ignorance from our government officials. One example is from the US Attorney General, Jeff Sessions. In a visit to Tampa in February, Sessions remarked, “I am operating on the assumption that this country prescribes too many opioids. People need to take an aspirin sometimes and tough it out a little.”[2] This statement underlies the lack of understanding of chronic pain and its detrimental effects among the government officials who have been tasked with solving this opioid crisis.

President Trump made this comment on March 19, 2018 and was quoted in an article by NPR: “Whether you are a dealer or doctor or trafficker or a manufacturer, if you break the law and illegally peddle these deadly poisons, we will find you, we will arrest you, and we will hold you accountable.”[3] While he is attacking the problem in multiple ways, he still seems to want to go after the legal prescription side in this battle.

Sixteen senators (now 15, since Al Franken resigned) had approached the DEA and requested and received a 20% cut in production in legal opioids in 2018 after cuts in 2017, and they want more cuts in 2019. Less production of legal meds creates big problems. And the DEA and Sessions have responded to this request, proposing a new rule that would allow the DEA to reduce the amount of opioids that drug companies can manufacture and sell, if it believes that a company’s opioids are being diverted for misuse.[4] Meanwhile, hospitals are already experiencing a shortage of many injectable opioids used for surgical anesthesia and for the treatment of post-surgical, traumatic and disease-produced severe pain.[5]

There have been a lot of statistics used to sway opinions in this fight. A group of anti-prescription opioid zealots known as PROP (Physicians for Responsible Opioid Prescribing) have made claims about prescription opioids that most patients and doctors alike would disagree with. Members of PROP, including Andrew Kolodny, MD, an addiction specialist who serves as PROP’s executive director, have been very influential in the media and with government bodies alike. They were very involved with the formation of the 2016 CDC Opioid Prescribing Guidelines. In a 2015 Q&A for the Kolmac Outpatient Recovery Center, Kolodny said, “Many Americans are truly convinced that opioids are helping them. They can’t get out of bed without them.”[6] And in an interview with The Fix in 2016, Kolodny was quoted as saying “Heroin users will use some of the exact same language pain patients use to explain how opioids help them. They wake up and feel agonizing pain, and they take their opioid and their pain becomes bearable.”[7] While PROP and its members are busy trying to convince the public and the US government that opioids are almost never appropriate for chronic pain and that patients who use long-term prescribed opioid therapy are tantamount to addicts, the science seems to disagree. In a recent white paper published by the Alliance for the Treatment of Intractable Pain, a review of the applicable research laid out the case for opioid prescriptions for chronic pain being both effective and posing a very low risk for addiction.[8]

In addition, the Centers for Disease Control (CDC) continued to count all deaths with legal or illegal opioids in a body, as an opioid death and using these statistics as an impetus to develop their 2016 guidelines, as well as listing them on their website to be cited by the media and other government officials who were tasked with developing policies to curb the overdose crisis. Using these statistics, it is no wonder that government officials came away with a belief that prescribing fueled the overdose crisis. However, in an article in April 2018 in a publication of the American Public Health Association, four CDC officials quietly admitted that the CDC statistics were miscalculated, and over-inflated by about double.[9] So far, the CDC itself has not officially admitted that the numbers are wrong, and continue to stand by their 2016 prescribing guidelines.

The PDMP (Prescription Drug Monitoring Program) was an answer government officials put in place to ensure that legal drug users were brought into compliance with the new standards being enforced on doctors and pharmacies. The legal prescription opioid users that still have access to pain medication sign contracts, subject themselves to random drug testing and agree to use one pharmacy. Well, the reduction in production of opioids in 2018 has caused many pharmacies to have a drug shortage. Many pharmacists are also reticent to fill opioid prescriptions out of fear of the DEA, or worry about fueling the opioid crisis because of the false media narrative. Pain patients drive to the doctor’s office to pick up their paper prescription, take it to their pharmacy and wait. If that pharmacy is out of your medication, you now go to another pharmacy and this trend continues in hopes of a refill. Then we need to call our doctor’s office back and let them know we filled our prescription at another location. This is a lot on people with chronic pain.

There is also a negative stigma attached to having to take pain meds. Many chronic pain patients take prescription opioids to continue meaningful work. This could be a huge problem because they are afraid to speak out, afraid of losing their job, or at least bringing suspicion upon themselves from employers. Many patients are afraid that if those around them know they take pain medication, they will be seen as addicts. But it is time to brush off the stigma and the fear and to stand up for our rights to access proper and effective medical treatment. If we don’t, we may lose access permanently and keeping our jobs, social lives, and other important activities and relationships will not be possible due to disability from pain.

Doctors that want to be doctors are now caught up wasting time in government “guidelines” or laws and pressure from insurance companies that do not want to cover pain control prescribed by our doctors. Many doctors who have continued to prescribe despite the current hostile regulatory environment have been threatened, raided, and even arrested by the DEA.[10] Our doctors are having to choose between upholding the Hippocratic Oath and keeping their ability to practice medicine and earn a livelihood altogether.

On April 3, 2018, the Centers for Medicare and Medicaid Services adopted a new policy governing opioid prescriptions for Medicare patients. While they backed down from a proposed “hard limit” where opioid prescriptions above 90 mg MME would be rejected at the pharmacy and could only be overridden by the insurer, they did end up passing a 200mg MME hard limit, and a “soft edit” at the 90 mg MME mark. This requires pharmacists to speak with the prescribing physician about the appropriateness of the dose for all prescriptions above 90MME. The pharmacist must then document this conversation and may fill the prescription at their discretion. The new rule also limits all new opioid prescriptions to 7 days, meaning Medicare will no longer pay for new opioid prescriptions that last more than 7 days, regardless of the circumstances. Many Chiari and EDS patients undergoing major surgery such as decompression or fusion, will no longer be able to receive more than a week of post-surgical pain medication without returning to their doctors for a new prescription. And patients who develop severe chronic pain in the future may not be able to get appropriate treatment for their pain. The only thing that kept CMS’ original proposal of a hard limit at 90mg MME was a severe backlash resulting in hundreds of strongly worded comments on their public docket from patients and physicians alike.[11] It is proof that our voices do matter and that we can make a difference when we speak out.

Despite some backlash from the chronic pain and medical communities, the government pushes forward with their agenda. Some states have lost their right to proper pain control and many are being threatened. It is time for those patients who have been sitting on the sidelines waiting for someone else to fight this battle for them, to rise and make some noise. It’s time for ALL of us to unite to make changes for ourselves and the future Pain Patients and our children. Imagine our children, inheriting these conditions from us and suffering the same or worse pain as we do, and having zero access to effective pain treatment because we allowed our government to take away one of our most effective treatment options!

What we all need to do is contact our elected officials. It easy to type up your email regarding your story and what pain meds mean to you or loved ones. You can look up your elected officials email address and copy and paste your email and send to many people. The elected official I spoke with said they have not heard from Chronic Pain Patients. Please take time and do this. You can send out emails laying down from your bed. You can also follow our CALL TO ACTION posts, which will inform you of key legislation and administrative actions and how you can act to make sure that our voices are heard.

My voice is one, but if many are sent in, they might listen. There is strength in numbers and together, we CAN make a difference! Please help.


[wpedon id=”4396″ align=”center”]


References:

1 Tennant, Forest. “Editor’s Memo October 2017: United Nations Says Untreated Pain Is ‘Inhumane and Cruel.’” Practical Pain Management, PracticalPainManagement, <www.practicalpainmanagement.com/treatments/pharmacological/opioids/united-nations-says-untreated-pain-inhumane-cruel>.

2Slattery, Denis. “AG Sessions Says Patients Should Take Aspirin or Suffer through Pain to Prevent Opioid Addiction – NY Daily News.” Nydailynews.com, New York Daily News, 8 Feb. 2018, <www.nydailynews.com/news/national/sessions-patients-aspirin-fight-opioid-crisis-article-1.3808114>.

3Horsley, Scott. “President Trump Vows To ‘Liberate’ U.S. From Opioid Crisis.” NPR, NPR, 19 Mar. 2018, <www.npr.org/2018/03/19/594999711/president-trump-vows-to-liberate-u-s-from-opioid-crisis>.

4Anson, Pat. “Sessions Wants More Cuts in Opioid Production.” Pain News Network, 17 Apr. 2018, <www.painnewsnetwork.org/stories/2018/4/17/sessions-wants-more-cuts-in-opioid-production>.

5 Bartolone, Pauline. “The Other Opioid Crisis: Hospitals Are Running Short of Powerful Painkillers.” Los Angeles Times, Los Angeles Times, 16 Mar. 2018, <www.latimes.com/business/la-fi-opioid-painkiller-hospitals-20180316-story.html#nws=mcnewsletter>.

6 Kolodner, George. “Q&A: Dr. Andrew Kolodney, Chief Medical Officer, Phoenix House.”Kolmac Outpatient Recovery Centers, 14 Dec. 2015, <www.kolmac.com/2015/12/qa-dr-andrew-kolodny-chief-medical-officer-phoenix-house/>.

7Siegel, Zachary. “Pain Patients Fear the Future Amid Opioid Crisis.” The Fix, 27 Nov. 2018, <www.thefix.com/pain-patients-fear-future-amid-opioid-crisis>.

8Lawhern, Richard A. “Prescription Opioids and Chronic Pain.” The Alliance for the Treatment of Intractable Pain, Mar. 2018, <www.atipusa.org/2018/04/02/atip-white-paper-on-prescription-opioids-and-chronic-pain/>.

9Seth, Puja, et al. “Quantifying the Epidemic of Prescription Opioid Overdose Deaths.”American Journal of Public Health, 7 Mar. 2018, <www.ajph.aphapublications.org/doi/10.2105/AJPH.2017.304265>.

10Bernstein, Lenny. “DEA’s Opioid Crackdown Brings Arrests of Prescribers, Pharmacists.” The Washington Post, WP Company, 2 Apr. 2018, <www.washingtonpost.com/national/health-science/deas-opioid-crackdown-brings-arrests-of-prescribers-pharmacists/2018/04/02/64ded32a-368f-11e8-8fd2-49fe3c675a89_story.html?noredirect=on&utm_term=.ef5781020422>.

11Roubein, Rachel. “CMS Tweaks Opioid Proposal after Backlash.” TheHill, The Hill, 3 Apr. 2018, <www.thehill.com/policy/healthcare/381493-cms-tweaks-opioid-proposal-after-sparking-backlash>.


✕
Chiaribridges

FREE
VIEW