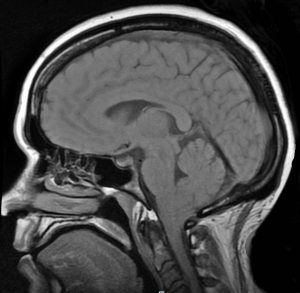
CHIARI MALFORMATIONS (PRONOUNCED: KEE-AH-REE) ARE STRUCTURAL DEFECTS IN WHICH THE CEREBELLUM, THE HIND PART OF THE BRAIN, DESCENDS BELOW THE FORAMEN MAGNUM INTO THE SPINAL CANAL.

While Arnold Chiari Malformation (Type 2) was first identified in the late 19th century by the Austrian pathologist Hans Chiari, much of the current medical knowledge has developed since 1985 with the expanded use of Magnetic Resonance Imaging (MRI). The number of patients diagnosed with Chiari malformations continues to increase, and with that increase Chiari Malformation is getting some of the attention the condition has always demanded.

Chiari malformations (“CMs”) are neurological disorders in which the cerebellum extends out of the skull and into the spinal canal, which in turn blocks the flow of cerebrospinal fluid, puts pressure on the brainstem and spine, and may result in varying degrees of nerve compression. Once thought to occur in 1 in 1000 people, it is now believed to be much more frequent of an occurrence. A 2016 pediatric study found it to occur in 1 in 100 children[1]. However, since the most common type (Type 1) tends to become symptomatic during late teens and early adulthood, it is likely to be much more common when adults are factored in. Females are more likely than males to have a Chiari Malformation (at a ratio of 3:1), and significantly higher amongst those with both Chiari Malformation and Ehlers-Danlos Syndrome (9:1)[2]. We affectionately refer to those that live with this condition, including the attendant pain and frequent disregard from the medical community, as Chiarians (regardless of whether they have had surgical intervention or not).

While some Chiarians are symptomatic throughout their lifetime, the vast majority of Chiarians (those with Type 1) develop symptoms in their late teens or early adulthood. Those symptoms can range from mild to crippling, and can become severe enough to cause paralysis (often associated with syringomyelia) or death.


WHAT CAUSES A CHIARI MALFORMATION?

Multiple factors have been identified which can either cause or attribute to Chiari malformations. Although they too were once thought to be rare, Acquired Chiari malformations are now being diagnosed in increasing numbers. A brief overview of what each of these labels entail, together with a summary of the different types of CM’s, is provided below:

  • Congenital Chiari, is believed to be caused by a posterior cranial fossa hypoplasia (PCFH)[3], which can also be caused by a connective tissue disorder such as Ehlers-Danlos.[4] While the cerebellum continued to grow in utero, the posterior skull failed to grow proportionately. Problems resulting from this size discrepancy continue and eventually the overcrowding of the hindbrain squeezes the cerebral tonsils downward into the opening of the spinal canal (cranial constriction). While the herniation of the cerebellar tonsil(s) can take place during gestation or after birth, because the cause is 100% congenital, and the process most likely began in utero, it is usually considered a Congenital Chiari Malformation when the only pathology found is a small posterior cranial fossa. In one large study, they found those with a Chiari Malformation and no associated etiological/pathological co-factors, with only slightly over 52% having a small PCF. When other co-factors were present, the number of Chiarians found with a small PCF plummeted, and therefore it should be considered acquired until proven otherwise.[5]

  • Acquired Chiari can have one or more possible pathological co-factors; any of which can result in the descent of the cerebellar tonsils. Many Chiarians often mistakenly conceptualize an Acquired Chiari Malformation as being brought on only by trauma; however, “acquired” is an antonym for “congenital,” so an Acquired Chiari Malformation in medical terms is one that a person was not born with. While this can include Acquired Chiari malformations resulting from trauma, it can also include Acquired Chiari malformations resulting from a variety of other medical conditions:
    • Heritable Disorders of Connective Tissue (HDCTs), most commonly Ehlers-Danlos Syndromes (EDS), make the tonsils more prone to prolapse below the foramen magnum.
    • Multiple conditions are known to create a pushing/pulling effect that can result in a tonsillar herniation. These conditions include: Intracranial Hypertension (IH), Atlantoaxial Instability and Craniocervical Instability (AAI/CCI), Tethered Cord Syndrome (TCS), and Intracranial Hypotension (cerebrospinal fluid leaks), Hydrocephalus, and a variety of cysts and brain tumors.[2]

    Special care should be taken when any of these co-morbid conditions exist in conjunction with a Chiari Malformation. Before the consideration of decompression surgery, a plan should be developed which addresses each possible comorbid condition before decompression. This can reduce the likelihood of complications and/or a failed decompression surgery.

SEVEN TYPES OF CHIARI MALFORMATIONS WORTH DISCUSSING (asterisks “*” indicate commonly known types)

Chiari Zero:  The lower part of the cerebellum (the cerebral tonsils) are blocking the foramen magnum, but are not descended through. Because of the cerebellum’s position, it blocks the flow of cerebrospinal fluid and all the effects of that blockage are comparable to Type 1.

Diagnosis Requirements: Symptomology; MRI showing no herniation but the low-lying tonsils that are pressing against the top of the foramen magnum; MRI showing a syrinx (despite the name, Chiari Zero is classified under Syringomyelia and not Chiari Malformation – so a syrinx is technically required for diagnoses). [6][7]

Treatment Options: With few symptoms, non-surgical treatments might be recommended. When a syrinx is present, a decompression is often recommended before the syrinx has a chance to further develop and cause additional damage to the spine. However, even when a syrinx is present, all pathological cofactors should be explored and addressed prior to decompression surgery.

Chiari 0.5: In cases of Chiari 0.5, the lower part of the cerebellum (the cerebral tonsils) are descended through the foramen magnum, but descends < 5mm (which is the measurement that some doctors use to define Chiari). Usually labeled “tonsillar ectopia” on radiology reports, the symptoms and effects of the obstruction are generally the same as those experienced with Type 1 or Chiari 1.5.[3]

Diagnosis Requirements: Symptomology; MRI showing a herniation of < 5mm, unless already properly diagnosed with a Type 1 or Chiari 1.5; presence of a syrinx is not “required” for diagnosis, but as with Chiari Zero, it illustrates that it is causing a problem obstructing the flow of cerebrospinal fluid and may be relevant when deciding between various courses of treatment.

Treatment Options: The same as Type 1 or Chiari 1.5, respectively.

*Chiari Malformation Type 1: The most common type of Chiari Malformation, Type 1 is diagnosed when the cerebral tonsils descend below the foramen magnum. Medical professionals unfamiliar with current research surrounding Chiari Zero and Chiari 0.5 (and the symptomology surrounding the blockage of cerebrospinal fluid), believe that a tonsillar herniation of less than 5mm is simply a tonsillar ectopia and only diagnose a Chiari Malformation when the descent is > 5mm. However, the 5mm requirement is controversial, and many doctors now base their diagnoses not solely on measurements, but rather on symptomology and a combination of other factors, including cine MRI’s, a patient’s symptoms, and other relevant factors.[6] Many people with a Chiari Zero, Chiari 0.5, or Type 1 can be asymptomatic for a lifetime: one large study found that approximately 30% of those with a CM measuring between 5-10mm were asymptomatic.[8] If symptoms develop, they often present in adolescence or early adulthood. Anecdotal evidence supports the proposition that once symptoms start, the symptoms often progress rapidly until the damage is stopped surgically.

Diagnosis Requirements: Symptomology; MRI indicating at least one herniated tonsil (without the brainstem descending as well).[9]

Treatment Options: Prior to surgery any/all comorbidities should be explored and treated especially if you are found to have a normal sized posterior fossa. However, if you have classic Chiari 1 Malformation with a small posterior fossa, the risks of surgery should be weighed against the severity of symptoms and the impact that symptoms are having on the patient’s quality of life. It is often recommended to treat mild symptoms with medication, with surgical options typically reserved for cases in which symptoms cause more serious medical and quality of life problems. However, symptoms do tend to progress, and studies have shown a correlation between successful decompression surgery and the amount of time between the onset of any symptoms and surgical intervention[10]. See “Decompression Surgery” below.

Chiari 1.5: This type of CM (often referred to as a “Complex Chiari”) is often acquired as opposed to congenital.  Chiari 1.5 should be the diagnosis when the tonsil(s) and all/part of the lower brainstem (the medulla oblongata) has descended past the foramen magnum. This is usually indicative of another comorbid condition pushing the brainstem downward from above or pulling downward from below.[5][11][12]

Diagnosis Requirements: symptomology; MRI indicating at least one herniated tonsil AND a downward displacement of all/part of the brainstem; without the other radiological findings associated with Type 2.

Treatment Options: Treatment options can vary significantly from patient to patient depending on the cause of the Chiari 1.5. While a variety of medical options might initially be used to treat symptoms, it is extremely important that all possible causes and/or comorbidities are thoroughly investigated and treated prior to the consideration of decompression surgery. Failure to identify and treat any such conditions can increase the likelihood of a failed decompression and further complications such as brain slumping, increased cervical instability, etc.

*Chiari Malformation Type 2 (also known as Arnold Chiari Malformation): Type 2 involves a herniation of the cerebellar tonsils and lower part of the brainstem (the medulla oblongata). Unlike in Chiari 1.5, in Type 2 the fourth ventricle is usually herniated, all/part of the cerebellar vermis (the tissue connecting both halves of the cerebellum) is missing or herniated, the corpus callosum (nerve fibers connecting both hemispheres of the brain) is fully/partially absent (agenesis), and it is almost always accompanied by a myelomeningocele (the most serious form of Spina Bifida, a congenital neural tube defect where the spinal canal does not close properly).[13][14][15]

Diagnosis Requirements: While a myelomeningocele is usually evident and diagnosed at birth, a brain MRI should confirm the radiological aspects of Type 2.

Treatment Options: Myelomeningocele is usually treated surgically at birth. If other related problems develop, such as hydrocephalus and/or tethered cord, they are often dealt with surgically as they become problematic. While some with Type 2 are decompressed, anecdotal evidence reflects a general trend of an increased failure rate with decompression surgeries as compared to those with Type 1. Because of this, some neurosurgeons choose not to decompress those with Type 2.

*Chiari Malformation Type 3: Type 3 is a serious type of Chiari Malformation involving herniated cerebellar tonsils, brainstem, and fourth ventricle. However, in most cases of Type 3, a sac forms out of the back of the skull (encephalocele) that contains brain matter from the cerebellum and the meninges. Type 3 causes severe neurological problems that are evident at birth and has a high infant mortality rate.[16][17]

 *Chiari Malformation Type 4: Type 4 is the most severe type of Chiari Malformation, but does not involve a hindbrain herniation (and therefore arguments have been made that it is not a Chiari Malformation). Instead, it consists of an undeveloped or underdeveloped cerebellum. Most infants born with Type 4 die in infancy.[16][17]


S
URGICAL INTERVENTION 

Decompression surgery is currently the only available means of attempting to stop the progression of symptoms of a congenital chiari (with no other pathological cofactors), but decompression is not a cure (not even close). Statistics show that up to 69% of decompressed patients find some measure of relief from surgery (usually headaches)[18]. Most neurosurgeons will give only a 50% chance of helping each individual symptom. Some of the symptoms are irreversible once they develop. Recent studies show that there is a correlation between early surgical intervention and positive post-surgical outcomes.[19] However, we cannot over emphasize the importance of your doctors taking time to find, diagnose, and treat co-morbid conditions BEFORE decompression surgery. If they are not willing to consider comorbidities, they are probably not the doctor for you!


[wpedon id=”4396″ align=”center”]

*Original version released January 2018, revised October 2018.


References:

1
Eltorai, Ibrahim M. “Rare Diseases and Syndromes of the Spinal Cord” Cham: Springer International Publishing: Imprint: Springer, 2016. Page 43, 15.2, <www.springer.com/us/book/9783319451466>.

2 Henderson, Fraser C., et al. “Neurological and Spinal Manifestations of the Ehlers–Danlos Syndromes.” American Journal of Medical Genetics Part C: Seminars in Medical Genetics, 21 Feb. 2017, <www.onlinelibrary.wiley.com/doi/10.1002/ajmg.c.31549/full>.

3 Sekula, Raymond F, et al. “Dimensions of the Posterior Fossa in Patients Symptomatic for Chiari I Malformation but without Cerebellar Tonsillar Descent.” Cerebrospinal Fluid Research, BioMed Central, 2005, <www.ncbi.nlm.nih.gov/pmc/articles/PMC1343586>.

4 Stagi, Stefano, et al. “The Ever-Expanding Conundrum of Primary Osteoporosis: Aetiopathogenesis, Diagnosis, and Treatment.” Italian Journal of Pediatrics, BioMed Central, 2014, <www.ncbi.nlm.nih.gov/pmc/articles/PMC4064514>.

5 Milhorat, Thomas H., et al. “Mechanisms of Cerebellar Tonsil Herniation in Patients with Chiari Malformations as Guide to Clinical Management.” Acta Neurochirurgica, Springer Vienna, July 2010, <www.ncbi.nlm.nih.gov/pmc/articles/PMC2887504>.

6 Isik, N, et al. “A New Entity: Chiari Zero Malformation and Its Surgical Method.” Turkish Neurosurgery., U.S. National Library of Medicine, <www.ncbi.nlm.nih.gov/pubmed/21534216>.

7 “JNS JOURNAL OF Neurosurgery OFFICIAL JOURNALS OF THE AANS since 1944.” The Resolution of Syringohydromyelia without Hindbrain Herniation after Posterior Fossa Decompression | Journal of Neurosurgery, Vol 89, No 2, <www.thejns.org/doi/abs/10.3171/jns.1998.89.2.0212?url_ver=Z39.88-2003&rfr_id=ori%3Arid%3Acrossref.org&rfr_dat=cr_pub%3Dpubmed>.

8 Elster, A D, and M Y Chen. “Chiari I Malformations: Clinical and Radiologic Reappraisal.”Radiology., U.S. National Library of Medicine, May 1992, <www.ncbi.nlm.nih.gov/pubmed/1561334>.

9 Wilson, Eugene. “Chiari.” CEDSA Home, <www.cedsa.org/index.php/59-quick-reference/73-chiari.html>.

10 Hindawi. “Surgical Management of Patients with Chiari I Malformation.” International Journal of Pediatrics, Hindawi, 28 June 2012, <www.hindawi.com/journals/ijpedi/2012/640127>.

11 Kim, In-Kyeong, et al. “Chiari 1.5 Malformation : An Advanced Form of Chiari I Malformation.”Journal of Korean Neurosurgical Society, The Korean Neurosurgical Society, Oct. 2010, <www.ncbi.nlm.nih.gov/pmc/articles/PMC2982921>.

12 Malik, Amita, et al. Chiari 1.5: A Lesser Known Entity. Annals of Indian Academy of Neurology, <www.annalsofian.org/article.asp?issn=0972-2327;year=2015;volume=18;issue=4;spage=449;epage=450;aulast=Malik>.

13 Wolpert, Samuel M, et al. “Chiari II Malformation: MR Imaging.” American Journal of Roentgenology, <www.ajronline.org/doi/pdf/10.2214/ajr.149.5.1033>.

14 Yumer, M H, et al. “Chiari Type II Malformation: a Case Report and Review of Literature.”Folia Medica., U.S. National Library of Medicine, <www.ncbi.nlm.nih.gov/pubmed/16918056>.

15 Kim, Irene. “Chiari II Decompression in Patients with Myelomeningocele in the National Spina Bifida Patient Registry (NSBPR).” <http://spinabifidaassociation.org/sbworldcongress/wp-content/uploads/sites/10/2017/04/B.4-Kim-Neurosurgery.pdf>.

16 “Chiari Malformation Fact Sheet.” National Institute of Neurological Disorders and Stroke, U.S. Department of Health and Human Services, <www.ninds.nih.gov/Disorders/Patient-Caregiver-Education/Fact-Sheets/Chiari-Malformation-Fact-Sheet>.

17 “Chiari Malformations.” NORD (National Organization for Rare Disorders), <www.rarediseases.org/rare-diseases/chiari-malformations>.

18 14 Aliaga, L, et al. “A Novel Scoring System for Assessing Chiari Malformation Type I Treatment Outcomes.” Neurosurgery., U.S. National Library of Medicine, Mar. 2012, <www.ncbi.nlm.nih.gov/pubmed/21849925>.

19  Siasios, John, et al. “Surgical Management of Patients with Chiari I Malformation” International Journal of Pediatrics, Article ID 640127, Hindawi, 2012, <www.hindawi.com/journals/ijpedi/2012/640127>.


THE DEFINITION OF A CHIARI MALFORMATION HAS BEEN LONG DEBATED. IT REALLY IS NO WONDER THAT PATIENTS AND MEDICAL PROFESSIONALS ALIKE ARE CONFUSED. THEN, WITH US FULLY UNDERSTANDING ALL SIDES OF THE DEBATE, WE DEFINED A CHIARI MALFORMATION AS STRUCTURAL DEFECTS IN WHICH THE CEREBELLUM, THE HIND PART OF THE BRAIN, DESCENDS BELOW THE FORAMEN MAGNUM INTO THE SPINAL CANAL. THIS DEBATE IS BEING ANALYZED THIS YEAR, AS CERTAIN ORGANIZATIONS ARE BRAVING TO ATTEMPT TO BRING DOCTORS ALL UNDER ONE UNIFORM DEFINITION AND DIAGNOSTIC CRITERIA. THEREFORE, AMIDST ALL THE CONFUSION AND DEBATE, WE WANTED TO EXPLAIN THE FACTORS INVOLVED, AND WHY WE WENT WITH THE DEFINITION THAT WE DID, AND WHY ONE STANDARD IS SO IMPORTANT!

To better facilitate our explanation, we will call all associated terms by their specific medical names:

Tonsillar Ectopia (TE) = tonsillar herniation of any size
Posterior Fossa Hypoplasia (PFH) = an underdeveloped posterior fossa

Chiari Malformation Vs. Arnold Chiari Malformation

The most common type of Chiari is Type 1 (which includes a Chiari 1.5, where the brainstem is also below the foramen magnum). Many people use the term “Chiari Malformation” when diagnosed with Type 1, while others cling to the name “Arnold Chiari Malformation” with the same diagnosis. Is there a difference? The name “Chiari Malformation” came from Hans Chiari, an Austrian pathologist, who first discovered the malformation in the late 19th century.[1, 2] Julius Arnold, a German pathologist, later expanded on Chiari Type 2, and Type 2 took on his name “Arnold Chiari Malformation.” Therefore, technically speaking, a Chiari Malformation and an Arnold Chiari Malformation are not the same; Arnold Chiari Malformation is specific to Chiari Type 2 (which usually includes a myelomeningocele, the most serious form of Spina Bifida). However, they are used interchangeably by many, even by medical professionals and the misnomer is of little consequence one way or the other.[3]

Chiari Malformation = Posterior Fossa Hypoplasia Theory

Many ascribe to the theory that a Chiari Malformation ONLY consists of a posterior fossa hypoplasia (which means that the back of the skull is malformed, and therefore the cranial area (space) at the rear is too small). They believe that a tonsillar ectopia is only a symptom, and a Chiari Malformation can exist with or without an accompanying ectopia. This argument is not without merit, because much of what was initially being looked at by Hans Chiari were deformities in the posterior skull upon postmortem examination (so there wasn’t soft tissue to analyze). He originally attributed much to hydrocephalus, but expanded his research into the pons, medulla oblongata, and cerebellum (which can all be attributed to intracranial pressure as a pathology of a “tonsillar ectopia”). To ascribe to this belief would also mean that “Acquired Chiari Malformations” cannot exist, as one doesn’t “acquire” a small posterior fossa. And that would also mean that Chiari Type 2, Type 3 and Type 4 technically would not be a Chiari Malformation at all either, since their definitions do not require a posterior fossa hypoplasia. Perhaps type 3, which has an opening at the back of the skull, but no “small posterior fossa” is even implied in the definitions.

But to look at the full history of what became known as a Chiari Malformation, we can begin by looking at the research of a German pathologist, named Theodor Langhans. In his research in 1881 (a decade before Hans Chiari conducted his research on what became known as a Chiari Malformation), while looking at syringomyelia (“a cavity created in the spinal cord”), he noted a “change in the cerebellar cavity.” Upon dissection of the cerebellum, he described the cerebellar tonsils as “two symmetrical pyramidal tumors,” pushing the brainstem forward.[4] In fact, the other noted researchers: Nicholas Tulp (1593–1674), John Cleland (1835–1925), and Julius Arnold (1835–1915), all centered on the hindbrain hernia [herniation] without speculation as to its etiology/pathology. It is said that “many of the English translations of Chiari’s work contain inaccuracies.” But note that Chiari’s first paper was on “ectopia of cerebellar tissue,” and that he went on to define Type 1 as showing, “elongation of the tonsils and medial parts of the inferior lobes of the cerebellum into cone shaped projections, which accompany the medulla oblongata into the spinal canal.”[5] Which sounds like what is now known to be a Chiari 1.5. Much later, in 1938, at a time when the posterior fossa decompression became the popular surgical treatment for a Chiari Malformation, a Chiari 2 patient “underwent posterior fossa exploration with the authors not considering hindbrain herniation in their differential. Penfield and Coburn later stated that: ‘In retrospect it seems that we should have suspected the Arnold-Chiari malformation. Instead, a suboccipital craniotomy was carried out…” So even the early neurosurgeons seeking to perfect their surgical treatment felt that it was a mistake to concentrate on the posterior fossa and not take into account etiologies of the hindbrain herniation. That mistake is still going on 80 years later.[6]

The biggest problem that they are going to have with strictly defining a Chiari Malformation as a small posterior fossa resides in the fact that the diagnosis criteria for a Chiari Malformation only consists of ONE MEASUREMENT, the length of the tonsillar ectopia (how far the tonsils herniate below the foramen magnum). Generally, there are no measurements of the posterior fossa taken when radiologists make the initial diagnoses. Furthermore, most neurosurgeons see the radiology reports, and depending on symptomology, they make the decision to decompress or not to decompress without ever measuring the size of the posterior fossa. Most never look for (and often do not know about) etiological/pathological cofactors that could have been causing the tonsillar prolapse in the first place.

Where does this assumption leave us?
Unfortunately it leaves most of us with failed decompressions, fighting with our neurosurgeons that “something is still wrong.” These neurosurgeons look at their post-operative checklist and see that they successfully did everything surgically required in their out-of-date textbooks:
  1. Suboccipital bone was appropriately decompressed. ✔️
  2. Dura was opened and dura patch was successfully inserted. ✔️
  3. Lamina was successfully removed from the C1 (and sometimes the C2 as well). ✔️
They did all that was required of them based on the diagnoses presented! They don’t have time (or don’t care) to look beyond that, so once again, the idea of our continued symptoms are thought of as being psychosomatic.
 
While we applaud the efforts of those seeking to get a measure of consistency in how Chiari is defined, the truth remains that until the diagnosis criteria is changed as well, we are being diagnosed with Chiari Malformation based on our tonsillar herniation; it is presumed to be congenital; we are being surgically treated as though it is congenital, and we are ending up with failed decompressions. This confusion is beyond unacceptable, it’s reprehensible!
When it is all redefined, hopefully we will have a well defined diagnosis criteria, or it is all irrelevant. And the many that really did acquire what was assumed to be “congenital” who are now being told that they do not have Chiari Malformation at all, will be able to get lawyers for “an improper diagnosis” that lead to the incorrect brain surgery being done. There are surgeons coming around and finally seeing that there is merit to these studies that have been done since the late 1990s, that have shown a pushing/pulling effect that can cause the tonsillar ectopia that gets us diagnosed with a Chiari Malformation, and we applaud them for having the integrity to stand up and get it right. That’s exactly what we need and deserve!
If you were diagnosed with a Chiari Malformation and want to know how all of this might be affecting you, we encourage you first to find your initial radiology reports, and see if there were measurements taken of the posterior fossa. And then wait with that information… wait and see what changes are actually made to the definition. While you are waiting learn. Learn everything you can about every etiological/pathological cofactor, and every comorbidity. If it is “officially” redefined as a small posterior fossa, we will have to work together as a community (like we always do) to help lawyers see how we have been getting lost in the shuffle, year after year. If it’s not officially changed and Chiari continues to be defined as a structural defect involving the cerebellar tonsils, we will have to continue in our fight to make these cofactors of Acquired Chiari Malformation known!

[wpedon id=”4396″ align=”center”]


References:

1 Tubbs, et al. “Hans Chiari (1851–1916).” Journal of Neurology, Pioneers in Neurology, Springer Berlin Heidelberg, 26 Mar. 2010, <https://link.springer.com/article/10.1007/s00415-010-5529-0>.

2 “Hans Chiari.” Whonamedit – Dictionary of Medical Eponyms, <www.whonamedit.com/doctor.cfm/1123.html>.

3 Tubbs, R. Shane, and W. Jerry Oakes. The Chiari Malformations: A Historical Context . 2013, <https://pdfs.semanticscholar.org/79dd/127d31820d612600c0b032225437295d86c3.pdf>.

4 Mortazavi, M M, et al. “The First Description of Chiari I Malformation with Intuitive Correlation between Tonsillar Ectopia and Syringomyelia.” Advances in Pediatrics., U.S. National Library of Medicine, Mar. 2011, <https://www.ncbi.nlm.nih.gov/pubmed/21361763>.

5 Pearce, J M S. “Arnold Chiari, or ‘Cruveilhier Cleland Chiari’ Malformation.” Journal of Neurology, Neurosurgery & Psychiatry, BMJ Publishing Group Ltd, 1 Jan. 2000, <https://jnnp.bmj.com/content/68/1/13>.

6 Mortazavi, Martin M., et al. “The First Posterior Fossa Decompression for Chiari Malformation: the Contributions of Cornelis Joachimus Van Houweninge Graftdijk and a Review of the Infancy of ‘Chiari Decompression.’” SpringerLink, Springer, Dordrecht, 6 Apr. 2011, <https://link.springer.com/article/10.1007%2Fs00381-011-1421-1>.

CHIARI (KEE-AR-EE) MALFORMATIONS ARE FAR FROM RARE, THEY ARE JUST RARELY UNDERSTOOD, EVEN BY MOST MEDICAL PROFESSIONALS. A CHIARI MALFORMATION EXISTS WHEN THE LOWEST PART OF THE HIND BRAIN (THE CEREBELLAR TONSILS) PROLAPSES INTO THE HOLE AT THE BOTTOM OF THE SKULL (FORAMEN MAGNUM), ENTERS THE SPINAL CANAL AND OBSTRUCTS THE FLOW OF CEREBROSPINAL FLUID (CSF), PUTS PRESSURE ON THE BRAIN STEM AND SPINE, AND MAY RESULT IN VARYING DEGREES OF NERVE COMPRESSION.

PREVALENCE OF CHIARI: Once thought to occur in 1 in 1000 people, it is now believed to be much more frequent of an occurrence. A 2016 pediatric study found it to occur in 1 in 100 children[1]. Since Chiari Malformation Type 1, the most common type, tends to become symptomatic during late teens and early adulthood, it is likely to be much more common when adults are factored in.

THE CONNECTION: Chiari malformations were originally believed to be caused by a posterior fossa hypoplasia (small area inside the back of the skull) and doctors speculated that lack of maternal prenatal care or drug abuse caused the deformity. However, as studies continue, they are finding that many with this hind brain herniation have connective tissue disorders, such as Ehlers-Danlos Syndromes. Ehlers-Danlos Syndromes involve a mutation in one of the collagen genes. Collagen is a protein that is often described as a “cellular glue” that helps hold the body together. When that glue fails to hold, everything seems to go awry; specifically, as related to Acquired Chiari Malformations: organs tend to prolapse, and bones begin to shift as joint laxity increases (including the bones/vertebrae at the craniocervical junction). They are finding that these acquired Chiari malformations are far more common than originally thought. There are many pathological co-factors that can cause or attribute to the formation of a Chiari Malformation, and most can be linked to these Heritable Disorders of Connective Tissues (HDCTs), including a posterior fossa hypoplasia. In one large study, they found those with a Chiari malformation and no associated co-factors, with only slightly over 52% having a small Posterior Cranial Fossa (PCF). When other co-factors were present, the number of Chiarians found with a small PCF plummeted and therefore it is should be considered acquired until proven otherwise.[2]

DIAGNOSES: A decade ago, it took 10-20 years from the onset of symptoms to be diagnosed and now it takes an average of 1-2 years, because medical professionals are slowly beginning to look for it. Magnetic Resonance Imaging (MRI) remains the best tool for diagnosis. Some medical professionals believe that a tonsillar herniation of less than 5mm is simply a tonsillar ectopia and only diagnose a Chiari malformation when the descent is > 5mm. However, the 5mm requirement is controversial and many doctors now base their diagnoses not solely on measurements, but rather on symptomology and a combination of other factors (including Cine MRI, a patient’s symptoms, and other relevant factors). Due to the prevalence of connective tissue issues, gravity often proves to be a significant factor and should be taken into account by use of an upright MRI whenever possible.[3] EDS should be diagnosed by a geneticist before surgery is considered.

TREATMENT OPTIONS: There is no cure for a Chiari malformation, but there are treatment options. When symptoms are minimal and not life-altering, pain management is usually offered. However, it is important to know that while medications may ease some symptoms, Chiari symptoms tend to be progressive. Decompression surgery is the only treatment available to attempt to halt the progression of the damage being done to your Central Nervous System (CNS). The most common reason that decompression surgeries fail, is undiagnosed co-morbid conditions, especially those that can be etiological/pathological co-factors. More than one surgery might be necessary to successfully treat a Chiari malformation and any/all co-morbid conditions and there is a correlation between early surgical intervention and positive surgical outcomes[4].

[wpedon id=”4396″ align=”center”]


References:

1 Eltorai, Ibrahim M. “Rare Diseases and Syndromes of the Spinal Cord” Cham: Springer International Publishing: Imprint: Springer, 2016. Page 43, 15.2, <www.springer.com/us/book/9783319451466>.

2 Milhorat, Thomas H., et al. “Mechanisms of Cerebellar Tonsil Herniation in Patients with Chiari Malformations as Guide to Clinical Management.” Acta Neurochirurgica, Springer Vienna, July 2010, <www.ncbi.nlm.nih.gov/pmc/articles/PMC2887504>.

3 Henderson, Fraser C., et al. “Neurological and Spinal Manifestations of the Ehlers–Danlos Syndromes.” American Journal of Medical Genetics Part C: Seminars in Medical Genetics, 21 Feb. 2017, <www.onlinelibrary.wiley.com/doi/10.1002/ajmg.c.31549/full>.

4 Siasios, John, et al. “Surgical Management of Patients with Chiari I Malformation” International Journal of Pediatrics, Article ID 640127, Hindawi, 2012, <https://www.hindawi.com/journals/ijpedi/2012/640127>.
From Intracranial Hypertension (formerly known as Pseudotumor Cerebri), Hydrocephalus, Tethered Cord Syndrome, to conditions related to the presence of a connective tissue disorder, such as Ehler’s-Danlos Syndrome, the primary reason for post-decompression complications seen in the Chiari Patient Community continues to be largely related to undiagnosed and untreated comorbid conditions. Time and time again, we see decompression failure, or a recurrence of symptoms after decompression, because there are other underlying conditions that need to be addressed. For this reason, we strongly recommend that patients get evaluated for the possibility of these known comorbid conditions before undergoing decompression surgery, unless circumstances require emergency surgery. (More information about the testing we recommend can be found in “The Treatments” article). Potential complications of decompression surgery may vary, depending upon the specific technique used, such as whether a duraplasty is performed, and how much bone is removed during a suboccipital craniectomy. The most common complications are infection, CSF leak, and Pseudomeningocele in adult patients.


INFECTIONS

Surgical site infections:
A surgical site infection is a risk of any surgery. While hospitals and surgical staff strive to maintain a sterile environment, hospitals are known for harboring pathogens, including many that are antibiotic resistant. Patient factors, including diabetes, age, being overweight, and being a smoker can also increase a patient’s risk of developing a post-operative infection.[1] Antibiotics are typically given post-surgically (and sometimes before surgery) in order to reduce the risk of infection. Some infections require wound revision surgery, to remove pus and infected tissue in order to improve healing.


MENINGITIS

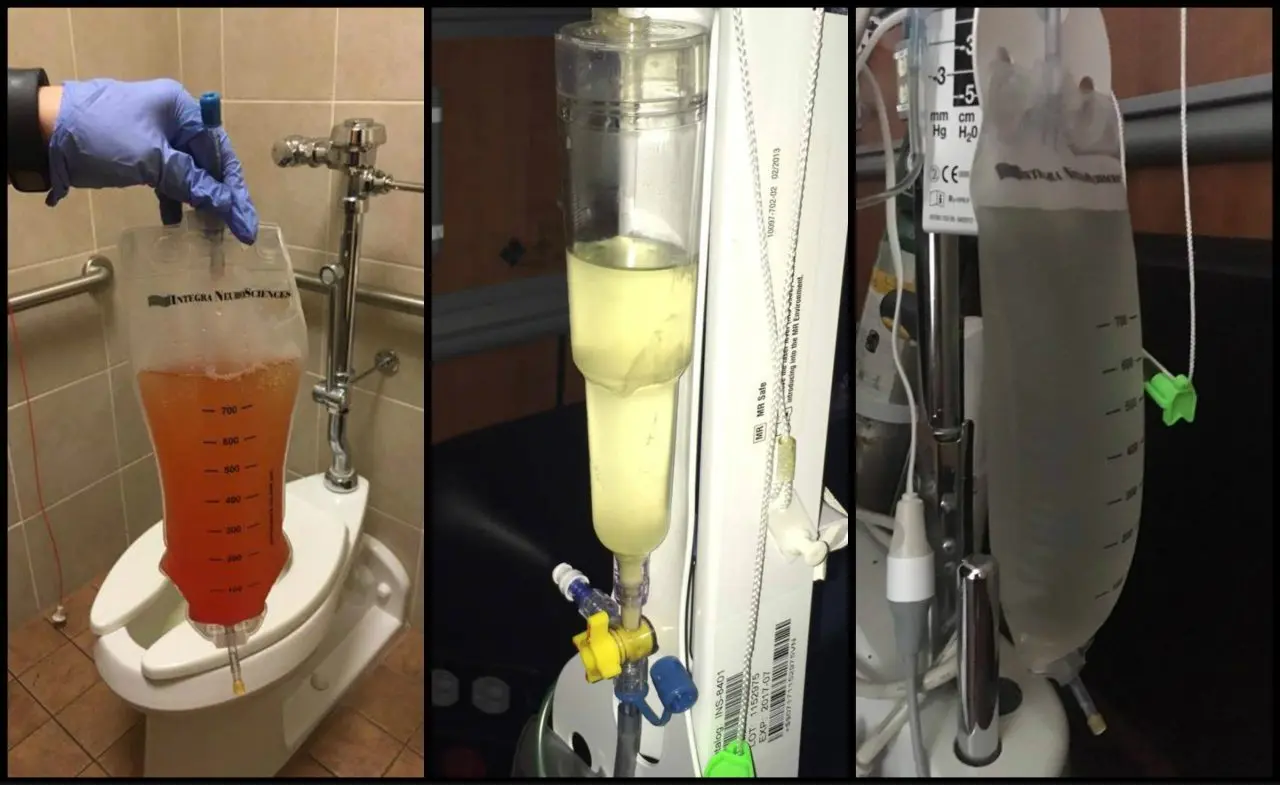
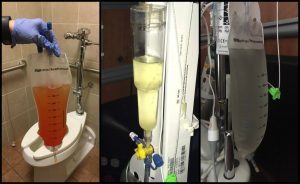
Meningitis is an additional surgical risk when the dura is opened during a decompression. It is characterized by inflammation of the meninges, the linings of the brain. There are three main types of meningitis: aseptic, bacterial and chemical.

CSF Meningitis/Blood (left); CSF Meningitis (middle); CSF (right)

♦ Aseptic Meningitis is by far the most common type, and is generally less severe than the bacterial type. Most cases of aseptic meningitis are caused by viruses, but may rarely be fungal, autoimmune, parasitic or drug-induced.[2] The treatment for aseptic meningitis is usually supportive care.[3] Chemical meningitis is also a risk any time surgery or other procedures or treatments are performed on the brain or spine.[4]

♦ Bacterial Meningitis is much more serious and can be life threatening. Three types of bacteria cause most cases: streptococcus pneumoniae, Group B streptococcus, and Neisseria meningitidis. Typical treatment includes antibiotics and supportive care.


CSF LEAKS

Duraplasty leak:
Post-decompression CSF leaks are a risk of decompression surgery whenever the dura is opened. The risk of a CSF leak dramatically increases with the presence of untreated hydrocephalus[5], intracranial hypertension (IH)[6], and connective tissue disorders, such as Ehlers-Danlos Syndrome. Nationwide statistics indicate that the risk of a CSF leak post-duraplasty is 10-15%. However, some surgeons report a significantly lower incidence of CSF leaks in their patients.[7] The use of biologic glue to seal the dural suture line has greatly reduced the incidence of post-duraplasty CSF leaks. A common sign of a leak is clear fluid leaking from the incision site.

Pseudomeningocele:
A pseudomeningocele is a type of CSF leak, where the leak creates a pocket in the muscles in the back of the neck. It is one of the most common complications of duraplasty. While some surgeons have managed to keep the incidence of pseudomeningocele low in their patients, some report an incidence as high as 18%.[8] A study at Vanderbilt University at 2013 showed that the development of a pseudomeningocele after decompression significantly reduced the benefit of decompression at one-year post-op on pain, disability and quality of life.[9] A smaller pseudomeningocele may re-absorb on its own. However, with large and persistent PM’s, the duraplasty may adhere to the cerebellar tonsils, blocking flow and making a revision surgery more difficult. There is much debate among neurosurgeons as to whether doing routine duraplasty as part of decompression outweighs the risks. Some argue that duraplasty increases the risk of complications, while others say that failure to perform duraplasty often results in inadequate decompression, reduced benefit, and the need for additional surgeries. Some experts argue that duraplasty using the patient’s own pericranial tissue and using water-tight sutures and biologic glue minimizes the risk of a leak and makes routine duraplasty the best option for most patients. A squishy pocket of fluid is often seen near the base of the skull and a PM can be confirmed and monitored with an MRI. In some cases, a surgeon may try draining the pocket of fluid with a needle and syringe.


BLEEDING AND ANESTHESIA-RELATED COMPLICATIONS

Excessive Blood Loss:
Excessive blood loss is a risk of any major surgery, but can be minimized by a careful surgical technique. Patients with connective tissue disorders may have an increased risk of bleeding complications, due to fragile blood vessels, particularly with vascular EDS or vascular crossover symptoms. Cessation of blood-thinning medications, such as warfarin, aspirin and NSAIDS also reduces the risk of bleeding.

Anesthesia Risks:
While risks of general anesthesia are quite low, the risk may be higher if you or someone related to you has had previous adverse interaction to general anesthesia. Some EDS patients are also prone to anesthesia issues, such as requiring more anesthesia or ineffectiveness of local anesthetics. Therefore, it is important to inform your anesthesiologist of your pertinent medical history.[10]


BONY REGROWTH

Regrowth of the bone removed during decompression is a risk associated with the pediatric patient population, particularly patients under the age of 2. Surgeons have reported as much as a 50% incidence of bony regrowth in patients under the age of 5, and as much as 80% in patients under age 2. Regrowth of bone may result in the need for future surgery.[5]


CRANIOCERVICAL INSTABILITY

While Craniocervical Instability is not uncommon among those with connective tissue disorders, it is pretty rare in the general population. However, aggressive bone removal during decompression surgery can create an unstable craniocervical junction. It is important to discuss with your surgeon how much bone they plan to remove, and the risks and benefits of laminectomy, particularly if you also have a connective tissue disorder, which increases your risk for developing instability.


CEREBELLAR SLUMPING (PTOSIS)

Cerebellar slumping (aka cerebellar ptosis) occurs as a result of too much bone being removed around the foramen magnum that there is no longer enough bone to support the weight of the cerebellum. The brain slumps downward toward the spine, re-herniating the cerebellar tonsils, and often compressing the cerebellum itself against the back of the skull and brain stem. This can often result in worse symptoms than the patient had before decompression. Surgical techniques have been developed to revise the decompression and provide more support to the cerebellum.[11]


OCCIPITAL NEURALGIA

Occipital neuralgia is nerve pain, often accompanied by numbness and/or tingling, of the occipital nerve in the back of the head. It can be caused by compression of or damage to the occipital nerve. While the presence of a Chiari malformation itself can cause compression of the cranial nerves, including the occipital nerve, decompression surgery can also cause occipital neuralgia. This can be due to compression of the nerve from the use of retractors to hold apart musculature during surgery, or the build-up of scar tissue around the nerve. More conservative treatment of occipital neuralgia may include medications, such as lidocaine patches and medication that target nerve pain, physical therapy, cutaneous nerve stimulators, and nerve root blocks. Severe and persisting occipital neuralgia may require surgical decompression of the nerve or occipital neurectomy, surgical removal of the occipital nerve.[12]


SCAR TISSUE AND ADHESIONS

Like with occipital neuralgia and pseudomeningocele, the development of scar tissue and adhesions can cause symptoms to return or failure to relieve symptoms after a decompression surgery. Adhesions and scar tissue can develop wherever tissue is cut, including the dural graft, cauterized tonsils and the skin incision. Scar tissue and adhesion can inhibit or block CSF flow and often require revision surgery to remove the scar tissue. A careful selection of the graft material used for a duraplasty may reduce the risk of developing adhesions and scar tissue.[13] 


DECOMPRESSION FAILURE

While perhaps technically not a complication, the failure rate of decompression surgery to alleviate symptoms deserves a mention here. While proper complications can often result in the failure of a decompression to relieve symptoms, or in fact, may make them worse than before decompression, even complication-free decompressions surgeries have a high rate of failure, as much as 40%, depending upon the study. Some reasons for decompression failure in the absence of the above-listed complications include failure to diagnose and treat comorbid conditions that may be causing symptoms, an inadequate decompression (failure to create enough space by removing bone and performing a duraplasty), and some or all of the symptoms being due to another cause, such as migraines. In cases of an inadequate decompression, a more aggressive decompression revision surgery may provide relief. In cases where a comorbid condition exists, that condition must be diagnosed and treated. However, there are still a small percentage of patients who do not get relief, even with further decompression and other treatments. The reason for this is not clearly understood.[5]


[wpedon id=”4396″ align=”center”]


References:

1 Torpy, Janet M. “Postoperative Infections.” JAMA, American Medical Association, 23 June 2010, <www.jamanetwork.com/journals/jama/fullarticle/186132>.

2 Ramachandran, Tarakad S. “Aseptic Meningitis Treatment & Management.” Aseptic Meningitis Treatment & Management: Approach Considerations, Medical Care, Prevention, 22 Aug. 2017, <www.emedicine.medscape.com/article/1169489-treatment>.

3 “Meningitis.” Meningitis | Brain & Spine Foundation, <www.brainandspine.org.uk/meningitis>.

4 McDaniels, Edison. “Chiari Decompression Surgery.” Neurosurgery101-TheBlog, 3 Apr. 2013, <www.surgeonwriter.com/chiari-4/>.

5 Trumble, Eric. “Chiari Overview & Surgical Issues.” Chiari and Syringomyelia Foundation, Chiari and Syringomyelia Foundation, 13 Oct. 2015, <www.csfinfo.org/videos/physician-lecture-videos/csf-lectures-archive/chiari-overview-surgical-issues/>.

6 “Chiari Surgery.” Chiari Surgery | Mayfield Chiari Center, 10 Dec. 2017, <www.mayfieldchiaricenter.com/chiari_surgery.php>.

8 “Pseudomeningocele Following Chiari Surgery Decreases Quality of Life.” CHIARI MEDICINE, 17 May 2015, <www.chiarimedicine.com/blog/2015/5/17/pseudomenigocele-following-chiari-surgery-decreases-quality-of-life>.

9 Parker, S. L., et al. “Effect of Symptomatic Pseudomeningocele on Improvement in Pain, Disability, and Quality of Life Following Suboccipital Decompression for Adult Chiari Malformation Type I.” Journal of Neurosurgery., U.S. National Library of Medicine, Nov. 2013, <www.ncbi.nlm.nih.gov/pubmed/24010974>.

10 “The Risks of Anesthesia and How to Prevent Them.” WebMD, WebMD, 2016, <www.webmd.com/a-to-z-guides/anesthesia-risks-what-patients-should-know>.

11 “Surgical Technique Alleviates Cerebellar Slumping.” Cerebellar Slumping, 31 May 2007, <www.conquerchiari.org/articles/surgery/techniques/cerebellar-slumping.html>.

12 Mueller, Diane. “Occipital Neuralgia and Chiari Malformation.” CHIARI MEDICINE, 4 Apr. 2013, <www.chiarimedicine.com/blog/2013/4/4/occipital-neuralgia-and-chiari-malformation>.

13 Attenello, Frank J., et al. Suboccipital Decompression for Chiari I Malformation: Outcome Comparison of Duraplasty with Expanded Polytetrafluoroethylene Dural Substitute versus Pericranial Autograft. 4 Sept. 2008, <www.link.springer.com/article/10.1007/s00381-008-0700-y>.

Read More
✕
Chiaribridges

FREE
VIEW