Born Different, but Not Knowing Why

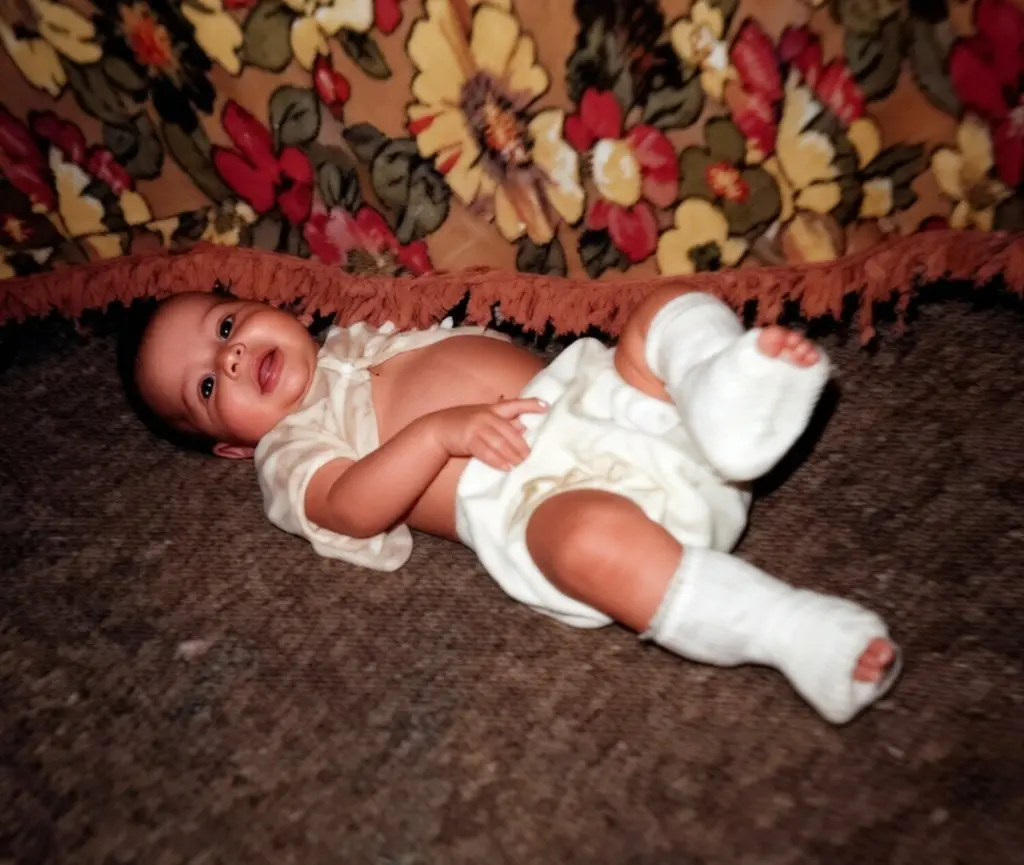
I was born into a body that was different from the beginning.

  • Clubfoot.
  • Left hip dysplasia.
  • Leg casts as an infant.

As an adolescent, I experienced severe growing pains, never realizing they might be connected to conditions that would take years to identify. Years passed. I lived life pain-free. 

By 2006, I was in the best shape of my life after losing 100 pounds through exercise and a low-carb diet. On May 9, 2006, I donated a kidney to my husband, Martin, an act of love I will never regret. We just celebrated our 20-year kidney transplant anniversary this year. 

At that time, I had not yet developed the debilitating symptoms of Chiari Malformation or Tethered Cord Syndrome (TCS). Then, in my 30s, everything changed.

2008: When the Symptoms Began

After riding a roller coaster in 2008, I immediately began experiencing symptoms that would eventually be associated with Chiari Malformation and TCS.

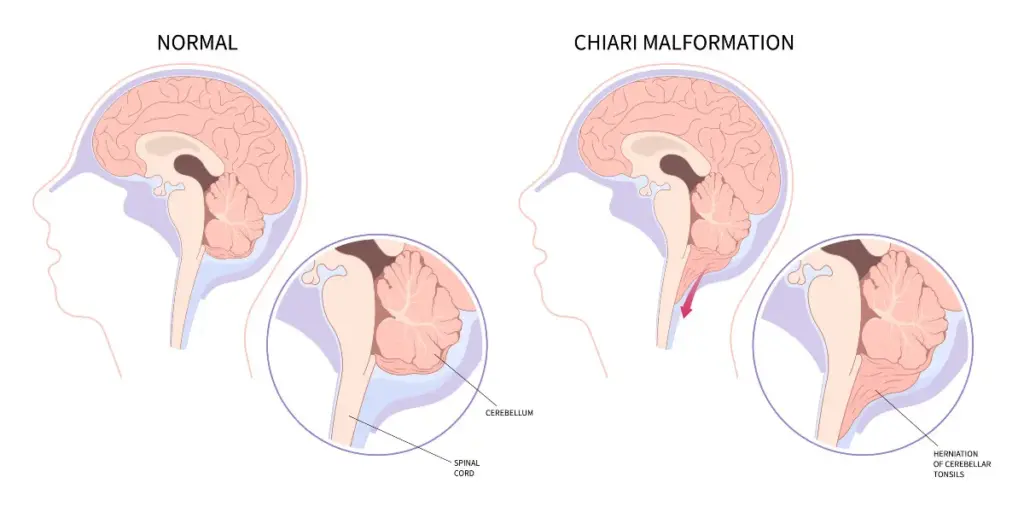
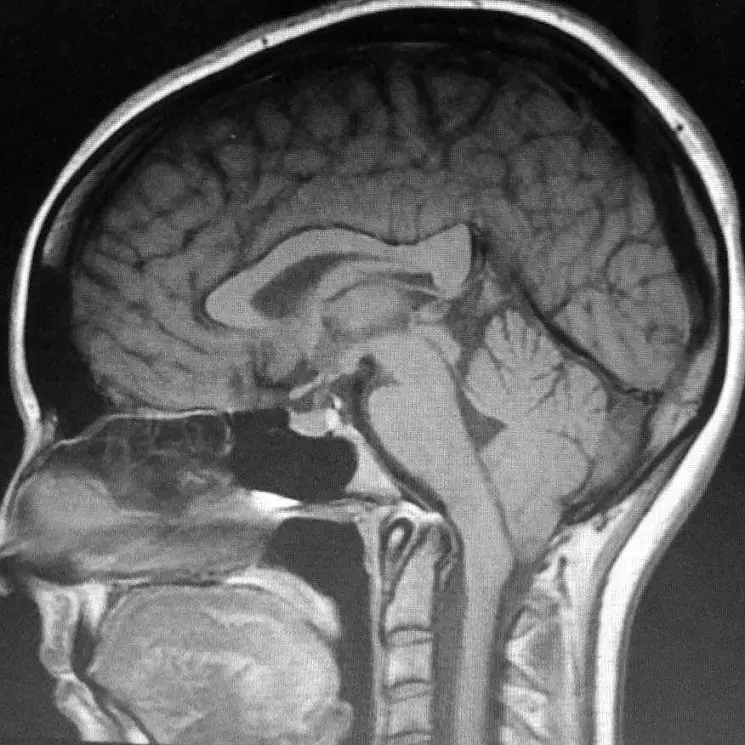
Brain imaging showed evidence of Chiari, but doctors didn’t interpret the findings in a way that led to answers. Because my cerebellar tonsillar herniation measured “only” 5 millimeters, doctors dismissed my symptoms as insignificant.

I knew something was wrong, but I struggled to get neurologists and neurosurgeons to take me seriously. Exhausted and frightened, I researched and advocated for myself until I finally found a specialist who understood.

Finding My Hero: Dr. John Oro

At 39, I found Dr. John Oro at the Colorado Chiari Institute. He diagnosed me with Chiari Malformation and Tethered Cord Syndrome.

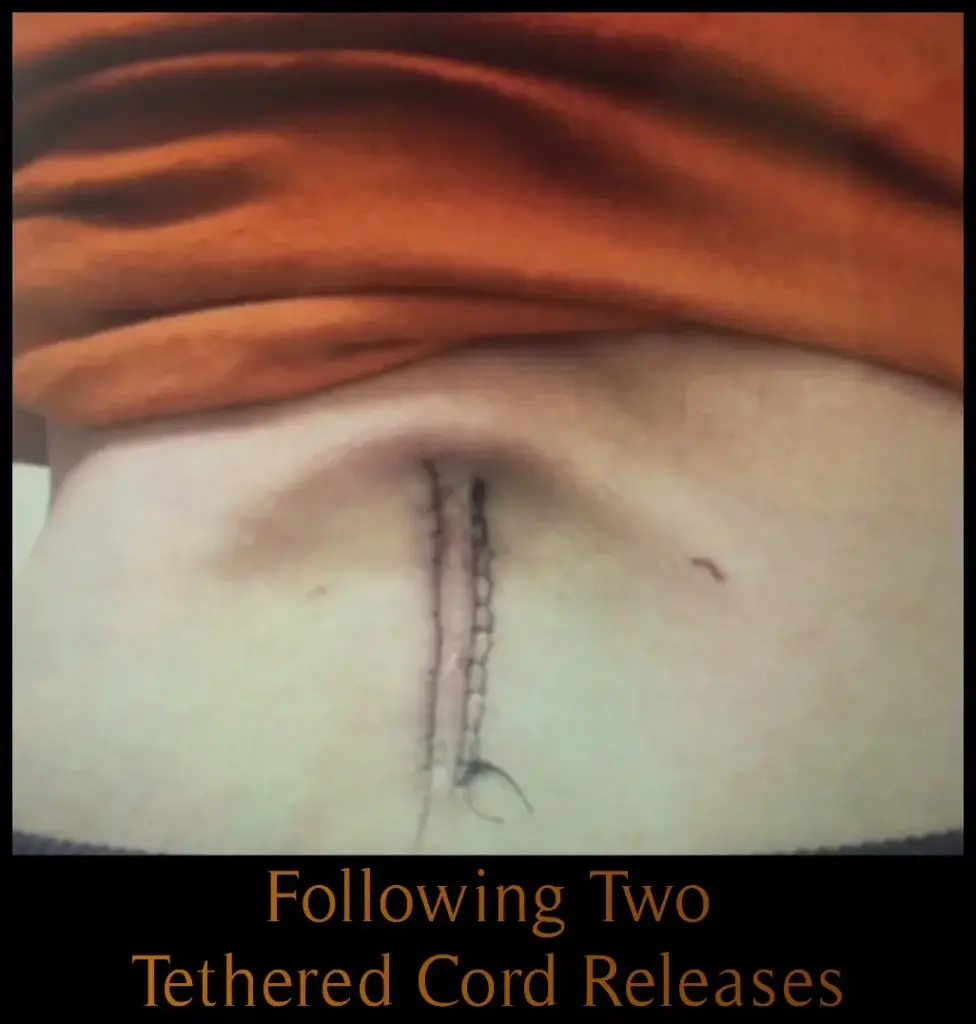
My TCS symptoms were more severe than my Chiari symptoms at the time, so in 2009, Dr. Oro performed my first spinal cord detethering surgery. For the first time, I felt understood.

Five Years Later: The Tethered Cord Returned

Approximately five years later, my spinal cord retethered, and my symptoms returned worse than before.

I traveled back to Colorado, where Dr. Oro performed another detethering surgery that lasted about four and a half hours. Afterward, I was able to “manage” my Chiari and TCS symptoms for a year.  

I hoped I could finally move forward, but my medical journey was far from over.
2016: The Crack in My Neck

In 2016, I heard and felt a crack in my neck. From that day forward, my Chiari symptoms became severe, and I began desperately seeking decompression surgery.

Dr. Oro had retired, so I had to find another specialist. Eventually, a UCLA neurosurgeon agreed to perform the procedure.

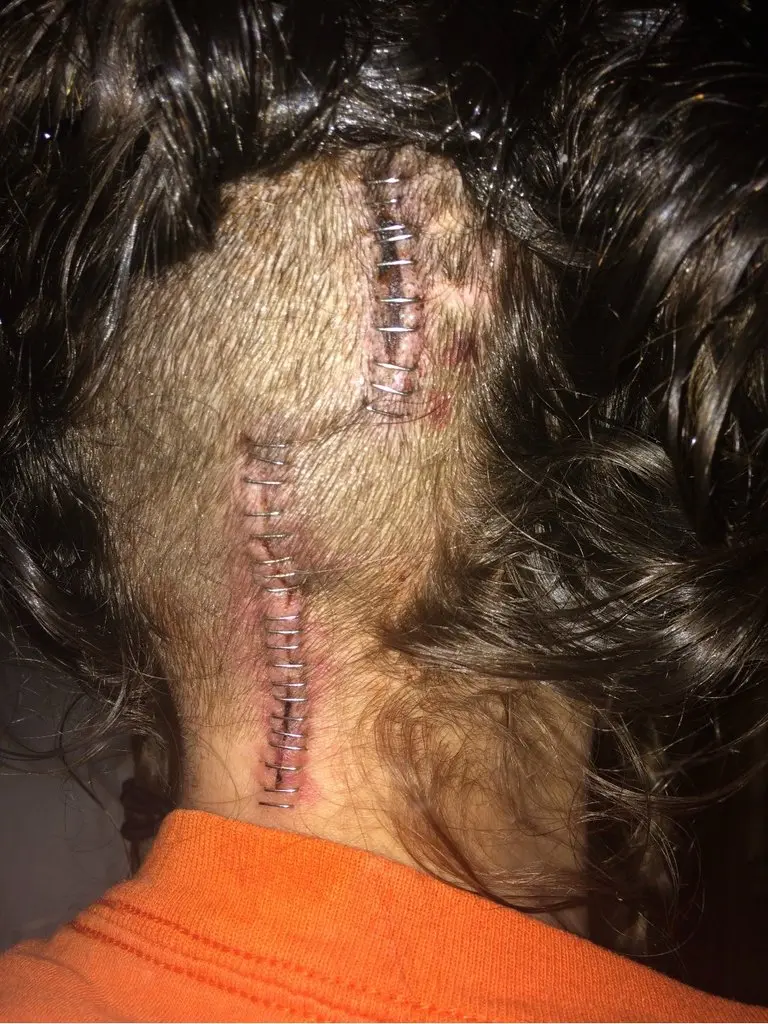
The six-hour surgery included cauterizing my cerebellar tonsils. Waking up was the most painful experience I had ever endured. I begged the medical staff to knock me out because the pain control was not working.

I eventually recovered, carrying the memory of that experience and 30 staples in my head. For approximately eight months, I felt some relief.

Then my symptoms returned.
The Clear Fluid: Discovering My Cranial CSF Leak

After those eight months, clear fluid began dripping from my nose, followed by horrific head pain. Local testing for a cranial cerebrospinal fluid (CSF) leak was negative.

Through my own research, I found Dr. Edward Hepworth in Colorado, a cranial ENT specialist who treats difficult-to-diagnose CSF leaks. After waiting eight months for an appointment, I traveled to Colorado and underwent a 48-hour hospital admission for a pledget study.

The leak was finally found.

In 2019, Dr. Hepworth repaired my cranial leak. During that same trip, I also had a hole in my heart closed.  

Hypermobile Ehlers-Danlos Syndrome: Connecting My Issues

In 2021, I was finally diagnosed with Hypermobile Ehlers-Danlos Syndrome (hEDS), a connective tissue disorder affecting joints, ligaments, and other tissues.

I had suspected hEDS for years, but obtaining a diagnosis was extremely difficult. The diagnosis helped connect some of the many conditions I had experienced, including clubfoot, hip dysplasia, Chiari symptoms, TCS, and my cranial CSF leak.

Each diagnosis added clarity, but none erased the pain or the years I had spent fighting to be heard.

Eighteen Surgeries: Learning the Language of Hospitals

Over the years, I have undergone 18 surgeries.

I learned the smell of hospitals, the sound of monitors, the fear before anesthesia, and the vulnerability of waking up unsure what pain would come next. I also learned how to navigate medical care and advocate for myself.

For years, I thought brain surgery was the worst pain I would ever experience.

I was wrong.

2020: The Day I Was Floxed

In 2020, I was hospitalized for an infected cyst below my parotid gland. I received Ciprofloxacin followed by intravenous Levaquin (levofloxacin), both fluoroquinolone antibiotics, over two days.

The day I was discharged, my life changed.

Severe, systemic pain began almost immediately. It spread throughout my body, making every movement difficult. I could barely walk, couldn’t tolerate anyone touching my feet, and couldn’t wear shoes.

I had survived brain surgery and spinal cord surgeries, so I knew what pain and recovery felt like. This was different. Surgery has an ending, an incision that heals, and the hope of recovery. Being floxed became something I had to live inside.

I felt like a walking corpse. At times, the suffering was so overwhelming that I wanted to die.

A Year of Medical Trauma and Gaslighting

For the next year, I lived in severe pain without answers. Doctors referred me to behavioral health because they could not explain my physical symptoms.

Being unable to walk normally, tolerate touch, or wear shoes while feeling disbelieved caused profound emotional harm. The experience became medical PTSD.

Then I learned about Fluoroquinolone Associated Disability, commonly known as FQAD. For the first time, I found information that connected my symptoms to the antibiotics I had received.

I finally had a name for what I believed had happened to me.

Spending Our Savings to Find Relief

My husband and I spent $23,000 of our savings on a five-day IV treatment followed by stem cell therapy. We made that decision because I was suffering so severely and needed a chance at a better quality of life.

I believe those treatments helped keep me from ending up in a wheelchair, but they did not restore my former life.

I am disabled now and live with severe pain every day. The woman I was before 2020 is not the woman I am today, and I continue to grieve what I have lost while learning to live with my body as it is.

January 2026: Finally Having a Diagnosis 

In January 2026, three months after the CDC approved a new ICD-10 diagnosis code for FQAD, I met with my primary care doctor to pursue official documentation of the long-term effects I had experienced after receiving fluoroquinolones.

My medical records now include: T36.AX5 — Adverse effect of Fluoroquinolone antibiotics, sequela (long-term effects).

After years of pain, confusion, and dismissal, I finally had validation, a diagnosis, and a name for what happened to me. 💜

This documentation does not erase my pain or restore my former life, but it matters. I wish I had known about the potential risks before receiving those medications. I wish I had been warned that serious, prolonged, and disabling reactions were possible.

I cannot change what happened, but I can tell my story.
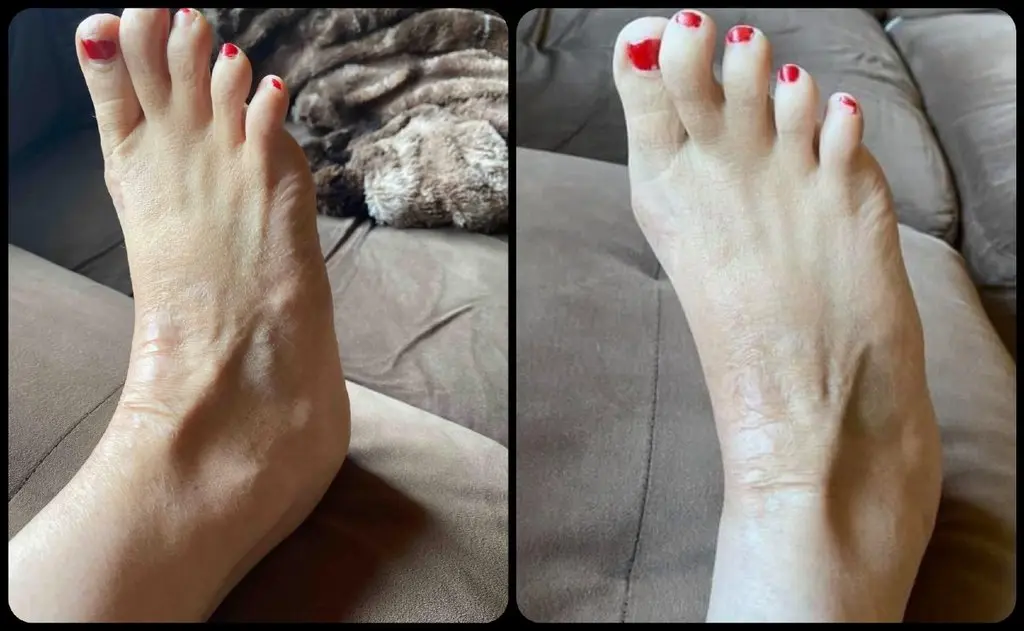
What Fluoroquinolones Did to My Right Foot

My right foot has become a visible reminder of the physical suffering I have experienced since receiving fluoroquinolones.

I want people to understand that serious adverse drug reactions can extend far beyond a hospital stay. When symptoms begin suddenly and pain becomes disabling, people deserve to be listened to and taken seriously.

I cannot undo what happened to my body, but I can raise awareness about fluoroquinolone-associated disability and encourage others to learn about the potential risks of these medications and seek medical care if concerning symptoms develop.

Many people are suffering, searching for answers, and struggling to be believed.

I am a daughter, a wife, a mother, a nana, and a woman who has survived experiences I never imagined facing.

I am more than my diagnoses, my surgeries, and the pain I live with.

If sharing helps someone find answers or feel understood, I will keep sharing.

Because after everything I have endured, I still have a voice, and I intend to use it!


*I dedicate this story to my family, my greatest blessings and my strongest support system throughout this difficult journey. To my husband, Martin, and our three beautiful daughters: Thank you for loving me through the pain, the tears, and the setbacks. Thank you for standing beside me, holding me up when I felt like I was falling apart, and loving me through the long haul. I am forever grateful for each of you. To Mom and Dad, and to my Wolf Pack, thank you for being part of my journey and for the love, strength, and support you have given me along the way. To Dr. Mark Ghalili, who saved my life. And to my fellow Floxies and everyone suffering from Fluoroquinolone Toxicity: this story is for you, too. For those living with invisible pain, grieving the lives they once knew, fighting to be believed, and finding the strength to keep going. You are not alone. Your pain matters, your story matters, and your voice deserves to be heard.

To read more on the safety issues surrounding fluoroquinolones, check out our article: “When “Safe and Effective” Fails: Fluoroquinolones and the Erosion of Public Trust.”


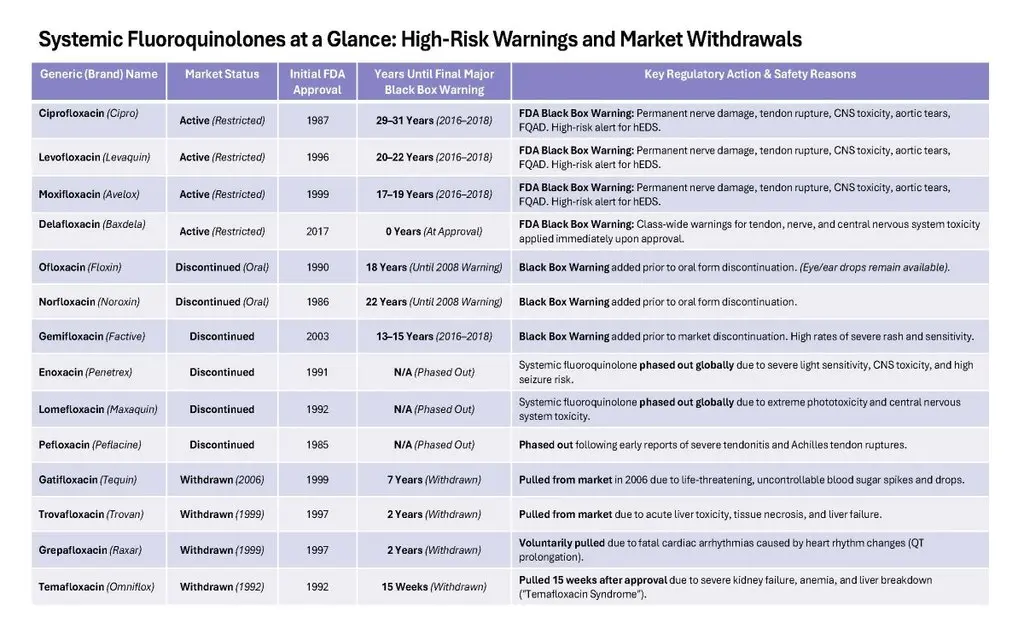
For decades, patients seeking medical care trusted a simple, foundational principle of medicine: First, do no harm. When a doctor handed down a prescription, patients assumed the medication had been thoroughly vetted for safety. Adverse reactions were presented as statistically negligible cases—unintended side effects in the march of modern medical progress.

Yet for millions of patients, especially those living with connective tissue disorders like Hypermobile Ehlers-Danlos Syndrome (hEDS) or Chiari Malformation, that trust has been shattered.

The history of fluoroquinolone antibiotics stands as a stark case study in institutional failure. Marketed for decades as routine frontline treatments, these powerful drugs were later retroactively hit with severe Black Box warnings. This story reveals a deeper crisis: the ongoing breakdown of public faith in corporate medicine.

The Rise of Fluoroquinolones: Profit Over Caution

Introduced widely in the 1980s and 1990s, fluoroquinolones were hailed as broad-spectrum miracle drugs. The class includes well-known medications like Ciprofloxacin (Cipro), Levofloxacin (Levaquin), and Moxifloxacin (Avelox). They were fast-acting, effective, and convenient.

Driven by aggressive pharmaceutical marketing, doctors routinely prescribed them for minor, uncomplicated issues: sinus infections, mild UTIs, bronchitis, and ear infections. Millions of prescriptions were written every year.

Behind the scenes, however, a troubling reality emerged. Early clinical trials—often funded and designed by the drug manufacturers themselves—were never structured to catch delayed, long-term, or multi-systemic damage. As these drugs dominated the market, reports of life-altering side effects began piling up in patient communities around the world.

A History of Withdrawals and Delayed Warnings

For years, regulatory agencies insisted that severe reactions were statistically negligible. Yet the safety history of fluoroquinolones tells a different story—one marked by sudden market withdrawals and late, reactive warnings.

Decades to Acknowledge the Damage

Decades of fierce patient advocacy, ruined lives, and overwhelming real-world evidence were needed for the FDA to intervene. Between 2008 and 2018, the agency issued a series of increasingly severe Black Box warnings—the strongest safety alert short of a total ban:

  • 2008: Warning added for an increased risk of severe tendinitis and tendon rupture.
  • 2013: Warning updated to explicitly state that nerve damage (peripheral neuropathy) can happen rapidly and become permanent.
  • 2016: The FDA stated that for simple infections (like sinus or mild bladder infections), the risks of fluoroquinolones outweigh the benefits, advising doctors to use them strictly as a last resort.
  • 2018: Warning issued specifically for high-risk populations—including individuals with Ehlers-Danlos Syndrome, hypermobility, or aortic aneurysms—due to the risk of aortic tears, tissue breakdown, and permanent disability.

The Hidden Peril for hEDS and Chiari Patients

For patients living with Hypermobile Ehlers-Danlos Syndrome (hEDS) or structural conditions like Chiari Malformation, these delayed warnings came at a devastating cost.

hEDS is a connective tissue disorder caused by defective collagen. Collagen is the physical scaffolding that holds together tendons, ligaments, blood vessels, and fascia throughout the body.

Fluoroquinolones interfere with collagen production and break down connective tissue. Giving a collagen-degrading antibiotic to a person whose body already struggles with fragile collagen is a dangerous combination. The result is often Fluoroquinolone-Associated Disability (FQAD)—a severe syndrome marked by widespread joint damage, tendon tears, burning nerve pain, and profound loss of mobility.

To make matters worse, patients who experienced these sudden post-antibiotic breakdowns were routinely dismissed. Because standard bloodwork and imaging rarely catch subtle cellular damage, patients were gaslit, told their symptoms were “just anxiety,” or referred to mental health providers. They were left to suffer both physical destruction and severe medical trauma.

How Medical Hegemony Shattered Public Trust

The tragedy of fluoroquinolones is not an isolated mistake or a single company’s oversight. It reveals a repeating pattern within modern healthcare:

  1. Declarations of Safety: A pharmaceutical product is launched, backed by industry-sponsored trials, and declared safe and necessary for broad populations.
  2. Suppression of Early Warnings: Patients and independent clinicians who raise early alarms about side effects are ignored, dismissed as “anecdotal,” or accused of spreading misinformation.
  3. A Slow, Reluctant Retreat: Years or decades later—after thousands of lives have been disrupted—institutions quietly update labels, attach Black Box warnings, or pull drugs off shelves, rarely acknowledging the damage done.
  4. The Informed Consent Loophole: Even after Black Box warnings are issued, doctors are not legally required to verbally inform patients of these warnings before handing down a prescription. Patients are left to discover the risks on their own—often only after irreversible harm has already occurred.

When public health institutions demand uncritical trust while enforcing rigid corporate consensus, they destroy the foundation of real science: open debate, continuous reassessment, and listening to patient outcomes.

When guidance shifts from “safe and routine” to “risk of permanent disability”—and patients are kept in the dark at the exam table—public skepticism is not irrational. It is a logical tool for self-preservation. Patients can no longer afford to blindly trust institutions or providers that prioritize commercial convenience over genuine patient safety.

What You Can Do to Protect Yourself

If you or a loved one live with hEDS, hypermobility, or any connective tissue disorder:

  • Always Disclose Your Diagnosis: Make sure every doctor, surgeon, and pharmacist knows you have a connective tissue condition before you accept any new prescription.
  • Ask for Alternatives: Unless you face a life-threatening infection with no other option, request a safer, non-fluoroquinolone antibiotic.
  • Listen to Your Body: If a medication causes sudden, burning nerve pain, joint stiffness, or extreme weakness, seek medical evaluation immediately and advocate for your safety.

Science is an ongoing process of testing, learning, and refining—not an unquestionable doctrine. By speaking up, sharing real experiences, and demanding accountability, patients are leading the way toward a safer medical system.

Real progress in medicine will not come from top-down decrees or silencing debate. It comes from empowered patients, transparent science, and true informed consent.

Surviving Chiari Malformation, tethered cord syndrome, and FQAD taught Michelle Nieves that staying silent is not an option. Her journey exposes why independent advocacy like Chiari Bridges is indispensable—it pushes back against dogmatic diagnostic criteria, shines a light on undocumented drug toxicities, and demands that medical institutions prioritize real-world patient outcomes over corporate consensus. Read her story, “The Michelle Nieves Story – Reclaiming My Voice: hEDS, Chiari, and the Hidden Dangers of Fluoroquinolones.”

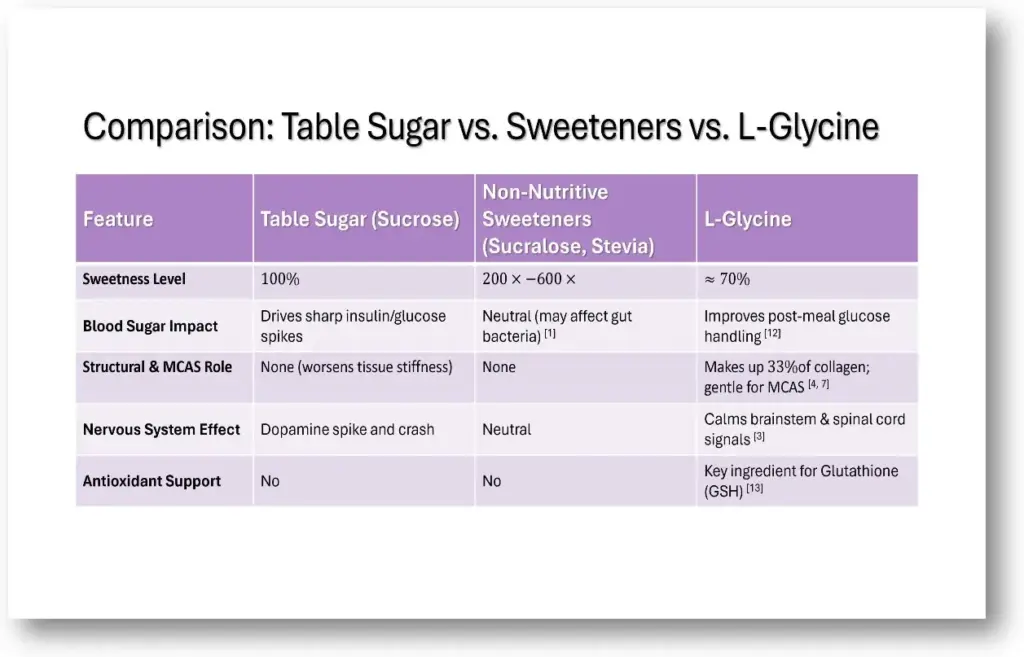
Standard sugars cause dangerous blood glucose spikes, but for many in our community, standard sugar-free alternatives are off the table because of Mast Cell Activation Syndrome (MCAS).

Many common artificial sweeteners (like aspartame, sucralose, and saccharin), and even certain sugar alcohols (like erythritol or xylitol), can trigger mast cell degranulation. They can spark systemic inflammation, brain fog, digestive distress, and skin flares [1].

Fortunately, a fascinating molecule pulls triple duty: L-glycine.

Metabolically speaking, glycine isn’t a sugar or an artificial sweetener—it is a functional amino acid (a protein building block). It tricks your tongue into tasting sweetness by binding to your mouth’s sweet flavor receptors and sending a “sweet” signal to your brain with zero actual sugar or synthetic chemicals [2].

People often dismiss glycine as just a sleep aid or simple sweetener. In reality, it is a key amino acid that supports tissue repair, immune stability, blood sugar control, and nervous system balance.

For people navigating hypermobile Ehlers-Danlos Syndrome (hEDS), Chiari Malformation, Craniocervical Instability (CCI), MCAS, or dysautonomia, glycine offers targeted benefits far beyond replacing sugar.

1. The Mast Cell Side: A Stabilizer-Friendly Option

  • Bypasses Artificial Triggers: Because pure L-glycine is a natural amino acid already native to the human body, it doesn’t trigger the chemical-induced mast cell flares common with synthetic sweeteners [1].
  • Calming to the Nervous System: Glycine acts as an inhibitory neurotransmitter in the central nervous system. By helping calm an overactive sympathetic nervous system (fight-or-flight), it can indirectly lower the systemic stress response that often drives mast cell reactivity [3, 4].
  • Soothing to the Digestive Tract: Many artificial options feed gut dysbiosis or irritate a sensitive GI tract. Glycine is rapidly absorbed via specific amino acid transporters in the upper small intestine, so it won’t ferment in the gut or cause bloating. Instead, it actively helps protect and repair the fragile intestinal mucosal barrier [5].

2. The Structural Side: Supporting the hEDS Collagen Matrix

  • The Premier Collagen Building Block: Collagen is structurally made up of a repeating chain of amino acids (Glycine - X - Y), and glycine makes up roughly one-third (33%) of that entire matrix [6]. In hEDS, genetic mutations make connective tissue inherently fragile, leading to chronic wear and tear that requires constant cellular turnover [7]. While supplemental glycine cannot alter these underlying genetic mutations, ensuring adequate amino acid availability matters because standard human metabolism naturally falls short of the massive daily demands of baseline collagen synthesis [8].
  • Protecting Tissues from Glycation: High blood sugar causes sugar molecules to bond to proteins in a destructive process called glycation, creating Advanced Glycation End-products (AGEs). This process stiffens collagen and makes it brittle—a double hit to tissue integrity for an hEDS patient. Glycine acts as a shield, helping to protect fragile connective tissues from this sugar-driven erosion [9].

3. Brainstem & Nervous System Support (Chiari & CCI)

Chiari Malformation and Craniocervical Instability can compress the brainstem and spinal cord, disrupting cerebrospinal fluid (CSF) flow and over-exciting the central nervous system.

  • Natural “Brakes” for Pain & Spasms: Glycine is the primary inhibitory (calming) neurotransmitter in the spinal cord and brainstem [3]. When it binds to its receptors (GlyR), it acts as a nerve damper, helping quiet motor hyperexcitability, muscle spasticity, and chronic pain signals [3, 10].
  • Autonomic & Vagal Balance: Many Chiari and hEDS patients struggle with dysautonomia (like POTS). Glycine exerts central anti-inflammatory effects and modulates brainstem tone, helping buffer against hyper-adrenergic “fight-or-flight” surges [3, 11].
  • Balanced Brain Function: In the brainstem and forebrain, glycine also works alongside glutamate as an NMDA co-agonist, supporting healthy memory and neuroplasticity without driving excitotoxicity [3].

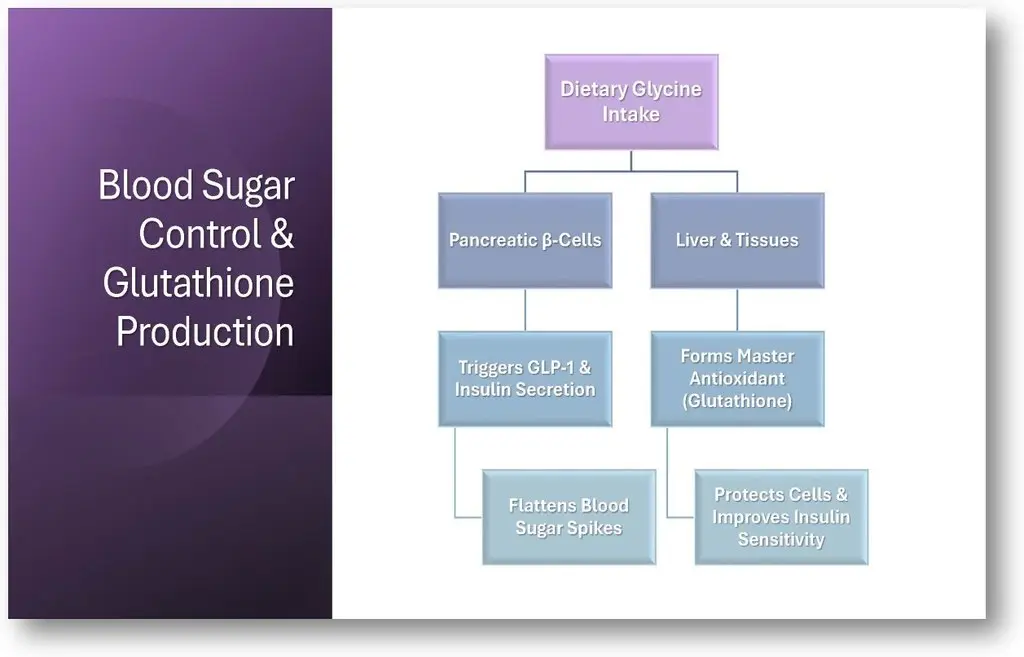
4. Blood Sugar Control & Glutathione Production

Rather than spiking blood sugar, glycine actively helps your body manage glucose and protect against cellular stress.

  • Flattens Glucose Spikes: When taken with food, glycine stimulates the gut hormone GLP-1 and triggers insulin release, helping prevent sharp blood sugar spikes after meals [12].
  • Builds Glutathione (GSH): Glycine is a required precursor for glutathione—the body’s master antioxidant [12]. Keeping glutathione levels high protects against liver inflammation and systemic oxidative stress [13].
  • Protects Tissue Elasticity: Glycine inhibits Advanced Glycation End-products (AGEs), “sticky sugars” that cross-link with collagen and stiffen joints and blood vessels over time [9].

5. The Glutathione Bottleneck: Why Glycine Often Pairs with NAC (GlyNAC)

While glycine is essential for glutathione synthesis, it doesn’t work alone. Glutathione is a tripeptide composed of three amino acids: glycine, glutamate, and cysteine [13].

Because cysteine is typically the hardest precursor for the liver to source, dietary cysteine (most commonly supplemented as N-acetylcysteine, or NAC) acts as the primary rate-limiting step [13].

  • The GlyNAC Synergy: Clinical trials demonstrate that combining glycine with NAC (GlyNAC) dramatically boosts intracellular glutathione levels, reduces systemic oxidative stress, and improves mitochondrial energy production better than either amino acid alone [14].
  • A Note of Caution for MCAS & Sensitive Stomachs: While GlyNAC is a powerful metabolic tool, NAC contains sulfur and can sometimes trigger histamine release or gastric distress in sensitive MCAS patients.
  • Best Practice: Ensure glycine tolerance first before introducing low-dose NAC, and always discuss new amino acid protocols with your healthcare provider.

💡 How to Use It in Your Routine

Pure L-glycine comes as a clean, white powder that dissolves easily in warm liquids. With a gentle, smooth sweetness, it pairs well as a functional sweetener in custom herbal blends—like morning coffee or my personal favorite, Spiced Dandelion Root Tea—to help protect metabolic health, soothe mast cells, and nourish connective tissue.

  • Standard Therapeutic Dose: Clinical studies generally look at 3g to 15g per day, divided into smaller doses with meals or before bed [11, 13].
  • Sleep Quality: Taking a 3g dose 30–60 minutes before bed helps lower core body temperature via peripheral vasodilation, promoting deeper slow-wave sleep [14].
  • Avoid Stomach Upset: High single doses (> 10 g at once) can pull water into the bowel, causing loose stools or cramping in people with slow GI motility.
    • Tip: Start with a low dose (1-2 g per meal) and slowly work your way up to see what your body tolerates best.

References

  1. Afrin, Lawrence B., et al. “Some Cases of Hypermobile Ehlers–Danlos Syndrome May Be Rooted in Mast Cell Activation Syndrome.” American Journal of Medical Genetics Part C: Seminars in Medical Genetics, vol. 175, no. 1, Mar. 2017, pp. 48–69, doi:10.1002/ajmg.c.31944. onlinelibrary.wiley.com/doi/abs/10.1002/ajmg.c.31944.
  2. Schmidt, Robert W., and Meghan L. Thompson. “Glycinergic Signaling in the Human Nervous System: An Overview of Therapeutic Drug Targets and Clinical Effects.” Mental Health Clinician, vol. 6, no. 6, Nov. 2016, pp. 266–76, doi:10.9740/mhc.2016.11.266. PubMed Central, pmc.ncbi.nlm.nih.gov/articles/PMC6007534/.
  3. Li, Xiangli, et al. “Dietary Glycine Prevents Peptidoglycan Polysaccharide-Induced Reactive Arthritis in the Rat: Role for Glycine-Gated Chloride Channel.” Infection and Immunity, vol. 69, no. 9, Sept. 2001, pp. 5883–91, doi:10.1128/IAI.69.9.5883-5891.2001. PubMed Central, pmc.ncbi.nlm.nih.gov/articles/PMC98707/.
  4. Howard, Alison, et al. “Glycine Transporter GLYT1 Is Essential for Glycine-Mediated Protection of Human Intestinal Epithelial Cells Against Oxidative Damage.” The Journal of Physiology, vol. 588, no. 6, Mar. 2010, pp. 995–1009, doi:10.1113/jphysiol.2009.186262. physoc.onlinelibrary.wiley.com/doi/full/10.1113/jphysiol.2009.186262.
  5. Shoulders, Matthew D., and Ronald T. Raines. “Collagen Structure and Stability.” Annual Review of Biochemistry, vol. 78, no. 1, June 2009, pp. 929–58, doi:10.1146/annurev.biochem.77.032207.120833. PubMed Central, pmc.ncbi.nlm.nih.gov/articles/PMC2846778/.
  6. Tinkle, Brad, et al. “Hypermobile Ehlers–Danlos Syndrome (a.k.a. Ehlers–Danlos Syndrome Type III and Joint Hypermobility Syndrome): Clinical Description and Natural History.” American Journal of Medical Genetics Part C: Seminars in Medical Genetics, vol. 175, no. 1, Mar. 2017, pp. 48–69, doi:10.1002/ajmg.c.31538. onlinelibrary.wiley.com/doi/10.1002/ajmg.c.31538.
  7. Meléndez-Hevia, Enrique, et al. “A Weak Link in Metabolism: The Metabolic Capacity for Glycine Biosynthesis Does Not Satisfy the Need for Collagen Synthesis.” Journal of Biosciences, vol. 34, no. 6, Dec. 2009, pp. 853–72, doi:10.1007/s12038-009-0100-9. Indian Academy of Sciences, www.ias.ac.in/article/fulltext/jbsc/034/06/0853-0872.
  8. Wang, Xuan, et al. “Glycine Suppresses AGE/RAGE Signaling Pathway and Subsequent Oxidative Stress by Restoring Glo1 Function in the Aorta of Diabetic Rats and in HUVECs.” The Journal of Nutritional Biochemistry, vol. 70, Aug. 2019, pp. 16–25, doi:10.1016/j.jnutbio.2019.03.018. PubMed, pubmed.ncbi.nlm.nih.gov/30944692/.
  9. Gundersen, Rune Y., Pål S. Opstad, and Frode Fonnum. “Glycine – An Important Neurotransmitter and Cytoprotective Agent.” Acta Anaesthesiologica Scandinavica, vol. 49, no. 8, Sept. 2005, pp. 1108–16, doi:10.1111/j.1399-6576.2005.00786.x. onlinelibrary.wiley.com/doi/abs/10.1111/j.1399-6576.2005.00786.x.
  10. Zafra, Francisco, et al. “Glycine Transporters and Its Coupling with NMDA Receptors.” Advances in Neurobiology, vol. 16, no. 1, Meeting 2017, pp. 55–83, doi:10.1007/978-3-319-55769-4_4. PubMed, pubmed.ncbi.nlm.nih.gov/28828606/.
  11. McCarty, Mark F., and James J. DiNicolantonio. “The Cardiometabolic Benefits of Glycine: Is Glycine an ‘Antidote’ to Dietary Fructose?” Open Heart, vol. 1, no. 1, May 2014, pp. 1–9, doi:10.1136/openhrt-2014-000103. PubMed Central, pmc.ncbi.nlm.nih.gov/articles/PMC4195924/.
  12. Sekhar, Rajagopal V., et al. “Glutathione Synthesis Is Diminished in Patients with Uncontrolled Diabetes and Restored by Dietary Supplementation with Cysteine and Glycine.” Diabetes Care, vol. 34, no. 1, Jan. 2011, pp. 162–67, doi:10.2337/dc10-1006. PubMed Central, pmc.ncbi.nlm.nih.gov/articles/PMC3005481/.
  13. Kumar, Premranjan, et al. “Supplementing Glycine and N-Acetylcysteine (GlyNAC) in Older Adults Improves Glutathione Deficiency, Oxidative Stress, Mitochondrial Dysfunction, Inflammation, Physical Function, and Aging Hallmarks: A Randomized Clinical Trial.” The Journals of Gerontology: Series A, vol. 78, no. 1, Jan. 2023, pp. 75–89, doi:10.1093/gerona/glac135. https://academic.oup.com/biomedgerontology/article/78/1/75/6668639.
  14. Yamadera, Wataru, et al. “Glycine Ingestion Improves Subjective Sleep Quality in Human Volunteers, Correlating with Polysomnographic Changes.” Sleep and Biological Rhythms, vol. 5, no. 2, Apr. 2007, pp. 126–31, doi:10.1111/j.1479-8425.2007.00262.x. https://onlinelibrary.wiley.com/doi/full/10.1111/j.1479-8425.2007.00262.

Most patients go to a neurosurgeon expecting an expert in their condition. However, while a doctor may be a brilliant surgeon, their knowledge of complex Ehlers-Danlos Syndromes (EDS) comorbidities can rank dangerously low.

Traditional Chiari decompression has an estimated failure rate approaching 50%. When a surgeon claims a “100% success rate,” be highly cautious. They are usually measuring mechanical completion (the bone was removed, the patch was sewn in) rather than how the patient actually feels.

Furthermore, data from our community of over 10,000 members reveals a deeply deceptive tactic used to protect these perfect statistics: these surgeons systematically cherry-pick their cases, dismissing complex patients before surgery—and entirely abandoning them if they develop a post-decompression problem afterward.

When a hypermobile patient experiences a post-op slump, worsening fluid pressure, or progressive instability, these surgeons routinely gaslight them, claim the operation was a structural success, and tell them to find a new neurosurgeon when post-decompression problems appear. By erasing injured patients from their clinics, they erase them from their failure data.

We deserve better than a tidy post-op scan followed by medical abandonment. Use the interview script below to find out if your surgeon understands a crowded skull versus a prolapsing brain.


  • Defining the Anatomy:
    How do you differentiate between a true congenital Chiari malformation and an acquired Chiari Malformation driven by connective tissue laxity? Since the standard diagnostic criteria for Chiari are based entirely on the size of the tissue prolapse (herniated tonsils) rather than the physical size of the skull cavity, an MRI report for a congenital crowded skull and an acquired prolapsing brain will look completely identical. How are you ruling out the latter before operating?
  • Volumetric Data:
    Are you basing my diagnosis solely on the millimeter drop of my cerebellar tonsils? Did my radiologist measure the physical volume of my posterior fossa to prove my skull cavity is actually too small?
  • The Prolapsing Risk:
    If my posterior fossa volume is normal but my ligaments are fragile, how will decompression prevent my hindbrain from prolapsing further into the newly enlarged opening?
  • The Chiari 1.5 Distinction:
    Looking at my sagittal scans, is any part of my medulla oblongata (brainstem) herniated or elongated below the foramen magnum? If yes, how does a basic decompression address this altered brainstem position?

  • The Core Measurements:
    What are my exact measurements for the Clivo-Axial Angle (CXA), Grabb-Oakes, and Harris measurements? [1]
  • Dynamic Imaging:
    Since instability is a motion failure, will you order an Upright Dynamic (Flexion/Extension) MRI or digital motion X-ray (DMX) to calculate how many millimeters my skull translates when moving? [2]
  • The Subaxial Foundation (C3–C7):
    Have you evaluated my mid-to-lower neck for Subaxial Instability (SAI) and premature Degenerative Disc Disease (DDD)? If my lower neck column is unstable or collapsing, how will my upper neck withstand the stress of a skull-base decompression? [4]
  • The Full-Spinal & Brain Scan Blindspot:
    If you are ordering a cervical scan but refusing a brain scan (or vice versa), how can we accurately map my neuro-anatomy? Since the central nervous system is one continuous column, how can we safely plan an irreversible surgery without a complete visualization of my brain down to my lumbar spine?
  • The Syrinx Origin:
    If I have a Syringomyelia (syrinx), how are we ruling out localized spinal cord compression from C3–C7 instability as the true driver of the cavity, rather than a skull-base blockage alone? If you refuse to scan my thoracic and lumbar spine, how can we be sure there isn’t a secondary syrinx or a tethering point fueling this fluid buildup? [4]

  • Addressing the Occult:
    Are you experienced in diagnosing Occult Tethered Cord Syndrome (OTCS)? If my conus medullaris terminates at a “normal” level on a standard supine MRI, how are we ruling out a tight, stretched cord that is anchoring my nervous system? [3]
  • Advanced High-Resolution Imaging:
    Will you order a CISS (Constructive Interference in Steady State) MRI sequence of my lumbar spine? Since standard thick-slice MRIs miss microstructural tension, will we use a CISS sequence to check for a thickened filum terminale or nerve roots pinned against the spinal canal walls? [3]
  • Prone Imaging Dynamics:
    Will you order a Prone Lumbar MRI (lying on your stomach) alongside the CISS sequence to see if my spinal cord is pathologically anchored and fails to float forward normally? [4]
  • Medullary Stretching & Dysautonomia:
    Are my profound autonomic symptoms (POTS, blood pressure crashes) coming from direct brainstem compression, or is a tethered cord stretching my medulla oblongata from the bottom up? [3, 4]
  • Surgical Order of Operations:
    If I have an occult tethered cord pulling my brain down, why should we decompress my skull before releasing the bottom tension? Won’t the rubber-band pull simply drag my brainstem deeper into the empty surgical site?

  • The S.E.E.P.S. Scan Review:
    Do you see any of the classic signs of spontaneous intracranial hypotension (SIH) on my brain MRI? [5]
    • S — Subdural fluid collections?
    • E — Enhancement of the pachymeninges (brain lining)?
    • E — Engorgement of dural venous structures?
    • P — Pituitary hyperemia (enlargement)?
    • S — Sagging of the brain/brainstem?
  • The Invisible Fistula:
    Are you aware that CSF-Venous Fistulas (CVFs) act like an open drain, siphoning my brain downward, yet leave zero fluid pools on standard spinal MRIs? [5]
  • Advanced Imaging Verification:
    If I have a clear orthostatic (positional) headache but a “normal” MRI, will you refer me to a specialized CSF leak center for a Digital Subtraction Myelogram (DSM) or Ultrafast CT Myelogram to find the hidden fistula or leak before operating on my head? [6]

  • High-Pressure Structural Signs:
    Does my brain MRI show an Empty Sella (or partially empty sella), flattened lateral ventricles, or distension of the optic nerve sheaths? [7]
  • Venous Stenosis Assessment:
    Since dural sinus collapse is highly prevalent in the EDS population, will you order a Magnetic Resonance Venogram (MRV) to evaluate my internal brain drainage? [7]
  • The Outside-In “Eagle” Compression:
    Because I have a hypermobile neck, will you order a 3D-CT Reconstruction of my skull base to rule out Eagle Syndrome? Are my elongated or calcified styloid processes mechanically crushing my internal jugular veins when I turn my head? [7, 8]
  • The Post-Op Slump Risk:
    If my brain is being pushed down by high pressure from a blocked vein or Eagle Syndrome, how will a decompression fix my drainage? Won’t the high pressure simply shove my brain stem directly into the newly created space? [8]
  • Cranial Valve Check:
    If my high pressure has caused a Cranial CSF Leak (fluid leaking from nose or ears), why should we patch the leak before clearing the venous blockage that caused the pressure to blow out in the first place?

If a neurosurgeon answers defensively, dismisses your measurements, or attempts to schedule an immediate decompression while ignoring met diagnostic criteria in Track 1, 2, 3, or 4: STOP.

An untreated comorbidity is the primary driver of a failed surgery. Walk away, protect your anatomy, and find a surgeon who treats the human being, not just the herniation.

You are informed, empowered, and absolutely Worth the Fight (WTF!)

Chiari headaches are felt at the occiput – at the base of the back of the skull and upper neck. They are generally tussive in nature, where they are exacerbated by valsalva maneuvers, which generally include: coughing, sneezing, heaving, laughing hard, or bearing down (like with a bowel movement or childbirth). These maneuvers reduce cardiac output (the amount of blood coming from the heart with each heartbeat), which in turn affects the attempted flow of cerebrospinal fluid, and it increases vagal stimuli. These headaches are often accompanied with feelings of vertigo, proprioception problems, gait problems, trouble swallowing, muscle spasms (commonly starts in the eyelids – blepharospasm), memory deficits, and cognitive difficulties (usually word recollection problems).

Occipital headaches occur at the back of the lower skull (occiput) and upper neck, on one or both sides of the upper spinal cord.

Pressure headaches are generally differentiated by position.

  • Low-pressure headaches: pressure is generally worse when upright and relieved by laying down.
  • High-pressure headaches: pressure is generally worse when laying down and relieved by being upright.
  • EXCEPTION TO THE RULE: Internal Jugular Venous Compression Syndrome (JVCS) increases intracranial pressure, but because the jugular vein is usually more open when laying down, it is usually relieved by laying down (which often causes confusion with low-pressure symptoms).

Those that suffer from low-pressure headaches tend to report feeling like there is an invisible pressure pushing down from the top of the head, often making it feel like your “head is going to implode.” Low-pressure headaches are characterized by being worse when upright and relieved by laying down. Low-pressure headaches are typically a sign of a cerebrospinal fluid leak (CSF Leak). The longer that the leak has existed, the less obvious the positional element – meaning the patient can be upright longer before they feel the pressure at the top of their head and they tend to need to lay down longer before getting any measure of relief. Caffeine often helps relieve low-pressure headaches.

Click image to view a more complete list of common low-pressure symptoms.


High-Pressure Headaches (IH/IIH)

Those that suffer from high pressure tend to feel pressure behind the eyes (often mistaken for sinus headaches) and report feeling like their “head is going to explode” from the pressure. High-pressure headaches are generally characterized by being worse when laying down – often awaking in the middle of the night or first thing in the morning with a headache, and the headache tends to dissipate to some degree after being upright for a period of time (and that period of time is different for everybody). Caffeine generally exacerbates high-pressure headaches.

Click image to view a more complete list of common high-pressure symptoms.


Connecting the Three Headaches

All of these are most common in patients with a connective tissue disorder such as Ehlers-Danlos Syndrome.

  • Untreated high pressure can push the cerebellar tonsils down into the foramen magnum where it blocks the flow of cerebrospinal fluid, leading to an Acquired Chiari Malformation (usually simply diagnosed and treated as a Chiari 1 Malformation) AND the blockage of cerebrospinal fluid further increases intracranial pressure.
  • Untreated high pressure can cause cranial leaks – often accompanied by cerebrospinal fluid leaking through the nose (CSF Rhinorrhea) or less commonly, the ears. (This can temporarily reduce intracranial pressure and its symptoms.)
  • Cranial leaks (often misdiagnosed with allergies) can sometimes seal on their own as the pressure reduces, leading to rebound high pressure (which is temporary) or continued high pressure if they originally had high pressure.
  • Untreated spinal leaks can create a suctioning or pulling down (sag) effect where the cerebellar tonsils get lodged into the foramen magnum, creating an Acquired Chiari Malformation (usually simply diagnosed and treated as a Chiari 1 Malformation). Once there, it blocks the flow of cerebrospinal fluid and increases the pressure (which can reduce spinal pressure and increase intracranial pressure), leading to the occipital headaches and other symptoms associated with any Chiari Malformation.

Major Problem Regarding Our Diagnoses & Treatment Options:

  1. Doctors and radiologists alike, tend to see the herniated tonsils and assume a small posterior fossa.
  2. Most do not check for high-pressure or low-pressure, even when directly asked and symptoms are present.
  3. When a posterior fossa decompression is finally offered, the high or low pressure is often left untreated which leads to a failed decompression.
  4. By the time sufferers get a name to go with their symptoms, we jump at the opportunity for relief.

The “Bobble-head Sensation” – When It Feels Like Your Neck Can No Longer Hold Up Your Head

While most of us experience this feeling either intermittently or continuously, it is generally related to structural instability issues:

  • Craniocervical Instability (CCI, also known as Syndrome of Occipitoatlantialaxial Hypermobility) involves vertical hypermobility (back and forth sliding) of the craniocervical junction (interface between the occipital bone and the 1st and 2nd vertebrae), where the neck is no longer properly supporting the cranium. This condition can be dangerous as it often involves brain stem compression that can lead to a vast array of symptoms of Dysautonomia (dysfunction of the Autonomic Nervous System – ANS).
  • Subaxial Instability (SAI; also known as Cervical Instability) involves hypermobility of the C2/C3 to the C7 intervertebral discs. This condition (like most conditions involving the cervical spine) is a major cause of muscle spasms (in the neck and throughout the body at any point below the disc issues. When these neck spasms occur, they can cause the “Bobble-head sensation” where it feels like your neck can no longer hold up your head. This disc degeneration can lead to paralysis as discs compress the spinal cord.

Important Questions to Ask Your Neurosurgeons: https://chiaribridges.org/important-questions-for-your-neurosurgery-appointment/.


Originally written 10/2019
Updated 12/2022

Updated 11/2024
Updated 3/2026

INTRACRANIAL HYPERTENSION (IH) MEANS HIGH PRESSURE INSIDE THE SKULL

Intracranial Pressure (ICP) is measured in millimeters of mercury (mmHg). Most scholars agree that on average:

  • Intracranial pressures (ICP) between 5-15 mmHg, are considered Normal pressure
  • Intracranial pressures (ICP) between 20-30 mmHg, are considered Mild to moderate intracranial hypertension which “requires treatment in most circumstances”,
  • Intracranial pressures (ICP) of > 40 mmHg indicates “Severe and possibly life-threatening intracranial hypertension.” [1]

When high intracranial pressure is left untreated, it creates a “pushing effect” towards the only natural escape at the base of the skull (the foramen magnum), and the cerebellar tonsils in the pathway are pushed through the foramen magnum. [2]


Understanding the Monro-Kellie Doctrine (the pressure-volume relationship)

The association between IH/IIH and Chiari Malformation appears to be a malicious intricate pathological circle. The cranium (skull) consists of brain matter, cerebrospinal fluid, and both venous and arterial blood. A hypothesis, referred to as the Monro-Kellie Hypothesis (now better known as the Monro-Kellie Doctrine), states, “The sum of volumes of the brain, CSF, and intracranial blood is constant. An increase in one should cause a decrease in one or both of the remaining two.” Therefore, if an abundance of cerebrospinal fluid (IIH or hydrocephalus), both cranial blood volume and brain matter should be forced to deplete. This depletion is usually directed in the path of least resistance – through the foramen magnum and into the spinal canal. When the brain matter closest to the bottom of the skull (cerebellar tonsils) is pushed through the foramen magnum and into the spinal canal (an Acquired Chiari Malformation), the tonsils act like a cork and blocks the flow of cerebrospinal fluid (regardless of the size of the tonsillar descent), which in turn, continues to raise intracranial pressure.[3]


Venous Hypertension

When an etiological cofactor exists (such as a space-occupying mass), it is considered Secondary Intracranial Hypertension (SIH); when no other cause was identified, it is known as Idiopathic Intracranial Hypertension (IIH) formerly known as Pseudotumor Cerebri. However, recent studies on the connection between Intracranial Hypertension and Venous Hypertension might put an end to the “idiopathic” theory.

Oxygen-rich blood travels from the heart to the rest of the body through the arterial system, then the oxygen-depleted blood returns to the heart through the venous system. We have a host of small veins in our head and they dump into a series of large veins, called sinuses.

Dural Venous Sinus Stenosis occurs when there is a narrowing of one or more of the venous sinuses (most commonly seen in the transverse sinuses or transverse/sigmoid sinus junction, but can also occur anywhere within these sinuses or in the jugular). This narrowing compromises cerebral venous outflow through the jugular vein (stenosis/compression of the jugular vein can also result in elevated intracranial pressure [4]). Transverse Sinus Stenosis (TSS) is most common what was initially assumed to be “Idiopathic Intracranial Hypertension (IIH), formerly known as Pseudotumor Cerebri (PTC). Depending on the study that you are reading, it is proving to be present in 90-100% of IIH patients [5]. While its connection might sound obscure, if you look at it from a Monro-Kellie perspective – the blood going into the head, cannot get out at the same speed (because of the narrowed sinus). When this inflow of blood remains constant and the outflow is hindered, the transverse sinus on that side (we have two transverse sinuses, one on each side) enlarges, forcing the CSF and brain matter to reduce to maintain the volume equilibrium. This reciprocation can happen when any of the sinuses or jugular narrow (stenosis). While scholars continue to debate whether TSS is a cause or consequence of IIH, surgeons continue to decompress us without checking our pressures or decompress (the most invasive treatment) in hopes that it will lower our pressures, and patients are left with untreated high pressure still causing a “pushing down effect” and an enlarged foramen magnum for our brains to be pushed down. [2] The sagging brain once again obstructs the flow of cerebrospinal fluid by plugging the foramen magnum, and that in turn raises the intracranial pressure even more. Or, the untreated high pressure blows through the duraplasty and causes a post-operative leak, known as a pseudomeningocele.


Brain MRIs often show indicators of Intracranial Hypertension (IH/IIH), therefore, we recommend that all Chiari patients have full brain MRIs and not just cervical MRIs.

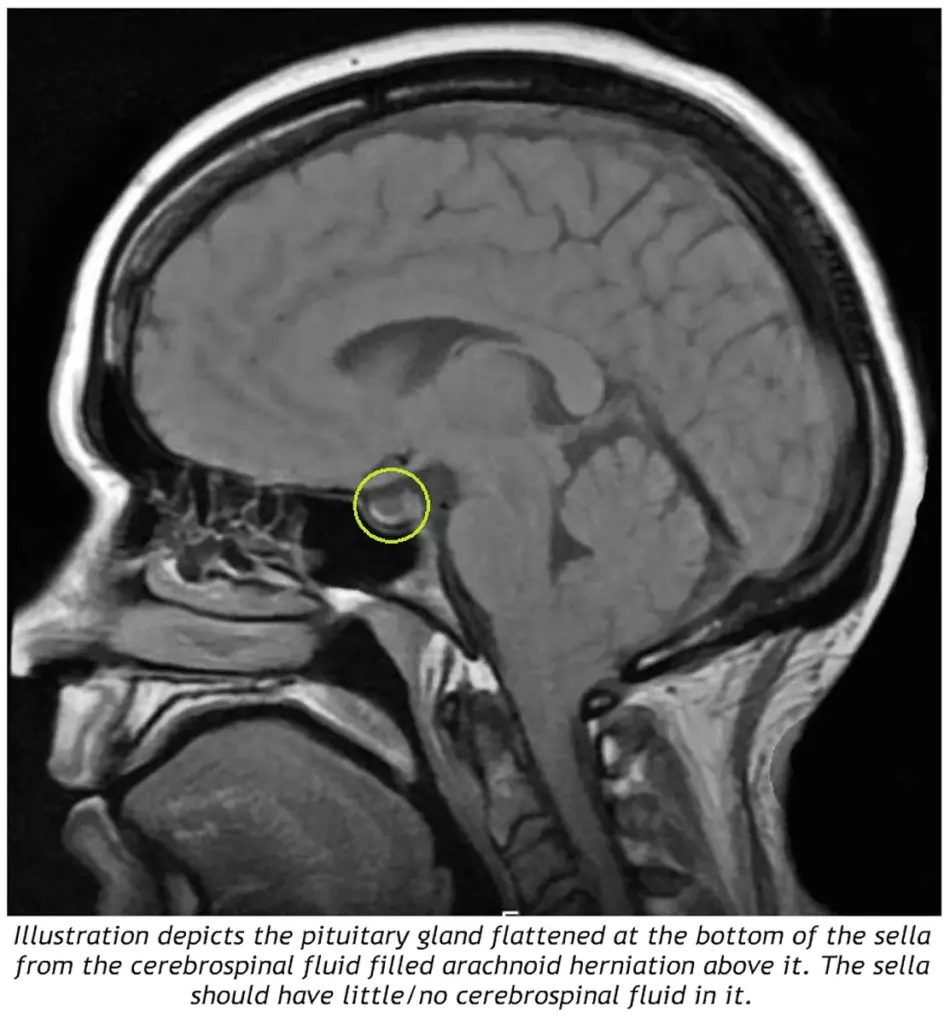
  • When the pressure builds inside of the dura mater the pressure pushes the dura and fluid inside of the crevice that holds the pituitary gland (the sella turcica or pituitary fossa). When the amount of fluid is equal to or greater than 50% and the pituitary gland size is 2mm, the condition is known as Empty Sella Syndrome. (Doctors now recognize that < 50% (where the pituitary gland size is 3-7mm) can also cause symptoms and they now refer to that as a partially empty sella.) [8]
  • Slit like or flattened lateral ventricles from the increased pressure, however, when the Foramen of Monro (the aqueduct that connects the lateral ventricle to the third ventricle) is stenosed, the fluid will back-up and the lateral ventricle will not appear flattened. [7]
  • Enlarged/swollen optical nerves (papilledema). [8]
  • Low lying or herniated tonsils (often diagnosed as a Chiari Malformation). [2]

Ideas BEFORE DECOMPRESSION is considered:

If you have symptoms of IH/IIH accompanied by any of the MRI indicators mentioned above, it is both reasonable and prudent to ask your neurosurgeon to investigate further BEFORE DECOMPRESSION.

  • See a neuro-ophthalmologist to check for signs of papilledema, including Optical Coherence Tomography and Ultrasonographic B-scanning. [8]
  • Magnetic Resonance Venography (MRV, preferably with the ATECO technique) to check for venous stenosis of any of the cranial sinuses and/or jugular vein. Stenosis is not exclusive to the transverse sinus and it can happen in multiple sinuses simultaneously.
  • If overweight, consider trying to lose weight. Studies show that a weight loss of 5-10% of one’s overall body weight, when accompanied by a low-salt diet, can offer some to IH/IIH symptoms.[9]
  • Consider trying Diamox (Acetazolamide) and/or Topamax (Topiramate) to see if that improves the pressure headaches.
  • Request a lumbar puncture (spinal tap) to test your opening pressures. We recommend that it’s guided with fluoroscopy with a small gauge needle (and not the standard 22 gauge) that they allow to drip (as opposed to syringe pull) and ensure that someone is available to perform an epidural blood patch if necessary. Time should be allotted afterward to lay flat for several hours immediately following the procedure and for several days once returning home. The potential for CSF leaks is high for the EDS/Chiari patient. A doctor that marginalizes the risks ahead of time, will generally marginalize your symptoms when you are actively leaking.
  • ICP Bolt Monitoring can record the differences experienced in pressure over time, and how different positions affect ICP.

Note: When the intracranial pressure gets high enough, it can cause a cranial leak. This is especially true for the Ehlers-Danlos patient where the dura mater is thin and fragile. When a cranial leak decreases the intracranial pressure, the papilledema, empty sella, stenosis, and high-pressure headaches can sometimes start to revert to normal or near-normal, and the leak will affect any attempts to check intracranial pressure (reducing the pressure from what it was before the leak occurred), however, the tonsillar herniation will usually remain if the pressure gets too low. [10]


TREATMENT OPTIONS:

  • If you have IH/IIH, ask your doctor to help you reduce the ICP before decompression! This can be done medicinally using Topamax or Diamox. If that doesn’t work, a shunt or stent should be considered.
  • A Ventriculoperitoneal Shunt(VP Shunt) or Ventriculoatrial Shunt (VA Shunt) can be surgically placed to drain cerebrospinal fluid straight from the ventricle. Shunts are known for failing and often need a multitude of revisions, but even with all the revisions, it can be less invasive than a decompression. Shunts under the foramen magnum should never be used as a means of controlling ICP.
  • An MRV is recommended for all IH/IIH patients. If it indicates venous stenosis, stenting should be considered, as leaving the sinus/jugular stenosed can post other health risks, and stenting can be successful for many with fewer complications that often require revisions.

For the IH/IIH patient, herniated tonsils should be assumed an Acquired Chiari Malformation (even if a small posterior fossa is evident), and by correcting the high pressure before decompression, the decompression will be less likely to fail.

Helpful Tips:
If you have IH/IIH, it is best to avoid caffeine, avoid progestin based birth control, and all EDS patients should try to avoid the use of fluoroquinolones such as ciprofloxacin (Cipro), levofloxacin (Levaquin/Quixin), gatifloxacin (Tequin), moxifloxacin (Avelox), ofloxacin (Ocuflox/Floxin/Floxacin), norfloxacin (Noroxin), due to the increased risk of aneurysm.


References: 

1 Rangel-Castillo, Leonardo, et al. “Management of Intracranial Hypertension.” Rangel-Castilla, Leonardo et al. “Management of intracranial hypertension.” Neurologic clinics vol. 26,2 (2008): 521-41, x. doi:10.1016/j.ncl. Feb. 2008, <https://www.ncbi.nlm.nih.gov/pmc/articles/PMC2452989/>.

2 Aiken, A.H., et al. “Incidence of Cerebellar Tonsillar Ectopia in Idiopathic Intracranial Hypertension: A Mimic of the Chiari I Malformation.” American Journal of Neuroradiology; Nov. 2012, <http://www.ajnr.org/content/33/10/1901>.

3 Mokri, B. “The Monro-Kellie Hypothesis: Applications in CSF Volume Depletion.” Neurology., U.S. National Library of Medicine, 26 June 2001, <https://www.ncbi.nlm.nih.gov/pubmed/11425944>.

4 Zhou, D., et al. “Intracranial hypertension induced by internal jugular vein stenosis can be resolved by stenting.” European Journal of Neurology, November 2017 <https://onlinelibrary.wiley.com/doi/abs/10.1111/ene.13512>.

5 Henderson, Fraser C., et al. “Neurological and Spinal Manifestations of the Ehlers–Danlos Syndromes.” American Journal of Medical Genetics Part C: Seminars in Medical Genetics, 21 Feb. 2017, <www.onlinelibrary.wiley.com/doi/10.1002/ajmg.c.31549/full>.

6 Pietrangelo, Ann. “Empty Sella Syndrome.” Healthline, Oct. 2017, <https://www.healthline.com/health/empty-sella-syndrome>.

7 Hingwala, Divyata R., et al. “Imaging signs in idiopathic intracranial hypertension: Are these signs seen in secondary intracranial hypertension too?.” Annals of Indian Academy of Neurology vol. 16,2: 229-33. doi:10.4103/0972-2327.112476, June 2013, <https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3724081/>.

8 Mollan, Susan P., et al. “A practical approach to, diagnosis, assessment and management of idiopathic intracranial hypertension.” Practical neurology vol. 14,6: 380-90. doi:10.1136/practneurol-2014-000821. May 2014, <https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4251443/>.

9 Thurtell, Matthew J., and Michael Wall. “Idiopathic Intracranial Hypertension (Pseudotumor Cerebri): Recognition, Treatment, and Ongoing Management.” Current Treatment Options in Neurology, U.S. National Library of Medicine, Feb. 2013, <https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3554852/>.

10 Pérez, Mario A., et al. “Primary spontaneous cerebrospinal fluid leaks and idiopathic intracranial hypertension.” Journal of neuro-ophthalmology : the official journal of the North American Neuro-Ophthalmology Society vol. 33,4: 330-7. doi:10.1097/WNO.0b013e318299c292, Dec. 2014, <https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4040082/>.

INTRACRANIAL HYPERTENSION (IH) MEANS HIGH PRESSURE INSIDE THE SKULL.

Intracranial Pressure (ICP) is measured in millimeters of mercury (mmHg). Most scholars agree that on average, “normal pressure” should be between 5-15 mmHg, mild to moderate intracranial hypertension between 20-30 mmHg (which “requires treatment in most circumstances”), and an ICP of > 40 mmHg indicates “severe and possibly life-threatening intracranial hypertension.” [1] When high intracranial pressure is left untreated, it creates a “pushing effect” towards the only natural escape at the base of the skull (the foramen magnum), and the cerebellar tonsils in the pathway are pushed through the foramen magnum. [2]

Understanding the Monro-Kellie Doctrine (pressure-volume relationship)
The association between IH/IIH and Chiari Malformation appears to be a malicious intricate pathological circle. The cranium (skull) consists of brain matter, cerebrospinal fluid, and both venous and arterial blood. A hypothesis, referred to as the Monro-Kellie Hypothesis (now better known as the Monro-Kellie Doctrine), states, “The sum of volumes of the brain, CSF, and intracranial blood is constant. An increase in one should cause a decrease in one or both of the remaining two.” Therefore, if an abundance of cerebrospinal fluid (IIH or hydrocephalus), both cranial blood volume and brain matter should be forced to deplete. This depletion is usually directed in the path of least resistance – through the foramen magnum and into the spinal canal. When the brain matter closest to the bottom of the skull (cerebellar tonsils) is pushed through the foramen magnum and into the spinal canal (an Acquired Chiari Malformation), the tonsils act like a cork and blocks the flow of cerebrospinal fluid (regardless of the size of the tonsillar descent), which in turn, continues to raise intracranial pressure.[3]

Venous Hypertension
When an etiological cofactor exists (such as a space-occupying mass), it is considered Secondary Intracranial Hypertension (SIH); when no other cause was identified, it is known as Idiopathic Intracranial Hypertension (IIH) formerly known as Pseudotumor Cerebri. However, recent studies on the connection between Intracranial Hypertension and Venous Hypertension might put an end to the “idiopathic” theory.

Oxygen-rich blood travels from the heart to the rest of the body through the arterial system, then the oxygen-depleted blood returns to the heart through the venous system. We have a host of small veins in our head and they dump into a series of large veins, called sinuses.

Dural Venous Sinus Stenosis occurs when there is a narrowing of one or more of the venous sinuses (most commonly seen in the transverse sinuses or transverse/sigmoid sinus junction), which in turn compromises cerebral venous outflow through the jugular vein (stenosis/compression of the jugular vein can also result in elevated intracranial pressure [4]). Transverse Sinus Stenosis (TSS) is most common in Idiopathic Intracranial Hypertension (IIH). Depending on the study that you are reading, it is proving to be present in 90-100% of IIH patients [5]. While its connection might sound obscure if you look at it from a Monro-Kellie perspective – The blood going into the head, cannot get out at the same speed (because of the narrowed sinus). When this inflow of blood remains constant and the outflow is hindered, the transverse sinus on that side (we have two transverse sinuses, one on each side) enlarges, forcing the CSF and brain matter to reduce to maintain the volume equilibrium. This reciprocation can happen when any of the sinuses or jugular narrow (stenosis). While scholars continue to debate whether TSS is a cause or consequence of IIH, surgeons continue to decompress us without checking our pressures or decompress (the most invasive treatment) in hopes that it will lower our pressures, and patients are left with untreated high pressure still causing a “pushing down effect” and an enlarged foramen magnum for our brains to be pushed down. [2] The sagging brain once again obstructs the flow of cerebrospinal fluid by plugging the foramen magnum, and that in turn raises the intracranial pressure even more. Or, the untreated high pressure blows through the duraplasty and causes a post-operative leak, known as a pseudomeningocele.

• When the pressure builds inside of the dura mater the pressure pushes the dura and fluid inside of the crevice that holds the pituitary gland (the sella turcica or pituitary fossa). When the amount of fluid is equal to or greater than 50% and the pituitary gland size is 2mm, the condition is known as Empty Sella Syndrome. (Doctors now recognize that < 50% (where the pituitary gland size is 3-7mm) can also cause symptoms and they now refer to that as a partially empty sella.) [8]

• Slit like or flattened lateral ventricles from the increased pressure, however, when the Foramen of Monro (the aqueduct that connects the lateral ventricle to the third ventricle) is stenosed, the fluid will back-up and the lateral ventricle will not appear flattened. [7]

• Enlarged/swollen optical nerves (papilledema). [8]

• Low lying or herniated tonsils (often diagnosed as a Chiari Malformation). [2]

What We Recommend BEFORE DECOMPRESSION is considered:
If you have symptoms of IH/IIH accompanied by any of the MRI indicators mentioned above, it is both reasonable and prudent to ask your neurosurgeon to investigate further BEFORE DECOMPRESSION.

  • See a neuro-ophthalmologist to check for signs of papilledema, including Optical Coherence Tomography and Ultrasonographic B-scanning. [8]
  • Magnetic Resonance Venography (MRV, preferably with the ATECO technique) to check for venous stenosis of any of the cranial sinuses and/or jugular vein. Stenosis is not exclusive to the transverse sinus and it can happen in multiple sinuses simultaneously.
  • If overweight, consider trying to lose weight. Studies show that a weight loss of 5-10% of one’s overall body weight, when accompanied by a low-salt diet, can offer some to IH/IIH symptoms.[9]
  • Consider trying Diamox (Acetazolamide) and/or Topamax (Topiramate) to see if that improves the pressure headaches.
  • Request a lumbar puncture (spinal tap) to test your opening pressures. We recommend that it’s guided with fluoroscopy with a small gauge needle (and not the standard 22 gauge) that they allow to drip (as opposed to syringe pull) and ensure that someone is available to perform an epidural blood patch if necessary. Time should be allotted afterward to lay flat for several hours immediately following the procedure and for several days once returning home. The potential for CSF leaks is high for the EDS/Chiari patient. A doctor that marginalizes the risks ahead of time, will generally marginalize your symptoms when you are actively leaking.
  • ICP Bolt Monitoring can record the differences experienced in pressure over time, and how different positions affect ICP.

Note: When the intracranial pressure gets high enough, it can cause a cranial leak. This is especially true for the Ehlers-Danlos patient where the dura mater is thin and fragile. When a cranial leak decreases the intracranial pressure, the papilledema, empty sella, stenosis, and high-pressure headaches can sometimes start to revert to normal or near-normal, and the leak will affect any attempts to check intracranial pressure (reducing the pressure from what it was before the leak occurred), however, the tonsillar herniation will usually remain if the pressure gets too low. [10]

TREATMENT OPTIONS:
If Venous Stenosis exists, stenting should be considered as leaving the sinus/jugular stenosed can post other health risks, and stenting is proving to have much better success with fewer complications requiring revisions. When medication fails to decrease ICP, and a stent is not an option, a Ventriculoperitoneal Shunt (VP Shunt) or Ventriculoatrial Shunt (VA Shunt) can be surgically placed to drain cerebrospinal fluid straight from the ventricle. Shunts are known for failing and often need a multitude of revisions, but even with all the revisions, it is less invasive than a decompression. Shunts under the foramen magnum should never be used as a means of controlling ICP.

For the IH/IIH patient, herniated tonsils should be assumed an Acquired Chiari Malformation (even if a small posterior fossa is evident), and by correcting the high pressure before decompression, the decompression will be less likely to fail.

Helpful Tips:
If you have IH/IIH, it is best to avoid caffeine, avoid progestin based birth control, and all EDS patients should try to avoid the use of fluoroquinolones such as ciprofloxacin (Cipro), levofloxacin (Levaquin/Quixin), gatifloxacin (Tequin), moxifloxacin (Avelox), ofloxacin (Ocuflox/Floxin/Floxacin), norfloxacin (Noroxin), due to the increased risk of aneurysm.


References: 

1 Rangel-Castillo, Leonardo, et al. “Management of Intracranial Hypertension.” Rangel-Castilla, Leonardo et al. “Management of intracranial hypertension.” Neurologic clinics vol. 26,2 (2008): 521-41, x. doi:10.1016/j.ncl. Feb. 2008, <https://www.ncbi.nlm.nih.gov/pmc/articles/PMC2452989/>.

2 Aiken, A.H., et al. “Incidence of Cerebellar Tonsillar Ectopia in Idiopathic Intracranial Hypertension: A Mimic of the Chiari I Malformation.” American Journal of Neuroradiology; Nov. 2012, <http://www.ajnr.org/content/33/10/1901>.

3 Mokri, B. “The Monro-Kellie Hypothesis: Applications in CSF Volume Depletion.” Neurology., U.S. National Library of Medicine, 26 June 2001, <https://www.ncbi.nlm.nih.gov/pubmed/11425944>.

4 Zhou, D., et al. “Intracranial hypertension induced by internal jugular vein stenosis can be resolved by stenting.” European Journal of Neurology, November 2017 <https://onlinelibrary.wiley.com/doi/abs/10.1111/ene.13512>.

5 Henderson, Fraser C., et al. “Neurological and Spinal Manifestations of the Ehlers–Danlos Syndromes.” American Journal of Medical Genetics Part C: Seminars in Medical Genetics, 21 Feb. 2017, <www.onlinelibrary.wiley.com/doi/10.1002/ajmg.c.31549/full>.

6 Pietrangelo, Ann. “Empty Sella Syndrome.” Healthline, Oct. 2017, <https://www.healthline.com/health/empty-sella-syndrome>.

7 Hingwala, Divyata R., et al. “Imaging signs in idiopathic intracranial hypertension: Are these signs seen in secondary intracranial hypertension too?.” Annals of Indian Academy of Neurology vol. 16,2: 229-33. doi:10.4103/0972-2327.112476, June 2013, <https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3724081/>.

8 Mollan, Susan P., et al. “A practical approach to, diagnosis, assessment and management of idiopathic intracranial hypertension.” Practical neurology vol. 14,6: 380-90. doi:10.1136/practneurol-2014-000821. May 2014, <https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4251443/>.

9 Thurtell, Matthew J., and Michael Wall. “Idiopathic Intracranial Hypertension (Pseudotumor Cerebri): Recognition, Treatment, and Ongoing Management.” Current Treatment Options in Neurology, U.S. National Library of Medicine, Feb. 2013, <https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3554852/>.

10 Pérez, Mario A., et al. “Primary spontaneous cerebrospinal fluid leaks and idiopathic intracranial hypertension.” Journal of neuro-ophthalmology : the official journal of the North American Neuro-Ophthalmology Society vol. 33,4: 330-7. doi:10.1097/WNO.0b013e318299c292, Dec. 2014, <https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4040082/>.

Read More

Most Chiarians go to see a surgeon with an expectation of them being knowledgeable in their field. However, while they might be a neurosurgeon, their knowledge of Chiari and its comorbid/pathological conditions might not rank high in their practice. Make the most of your initial appointment by interviewing them and what they really know about Chiari Malformations. Be cautious of inflated success rates. Chiari decompression in general offers a just over a 50% success rate (which means it has a nearly 50% failure rate). Surgeons that claim a 100% (or near 100% success rate) are usually not basing their success on how their patients feel afterward, it is based on if they were successful with the aspects of the surgery:
         Removal of the occipital bone ✓
          Opening the dura and adding the patch/graft ✓
          Laminectomy ✓
          Cauterization/resection of cerebellar tonsils ✓

WE DESERVE BETTER THAN THAT!


HERE IS A LIST OF CHIARI QUESTIONS WE RECOMMEND ASKING AT YOUR FIRST NEUROSURGERY APPOINTMENT:

General Questions:

  • How do you define a Chiari Malformation?
  • What do you believe causes a Chiari malformation?
    • Are all Chiari malformations from a small posterior fossa?
    • Do I have a small posterior fossa? If yes, how big is it? If size is unknown, was my posterior fossa measured? If not, why not? How did you come to the conclusion that I have a small posterior fossa?
    • How common do you believe Acquired Chiari malformations to be?
  • Do you always recommend decompression surgery for all of your patients with herniated cerebellar tonsils? Why/why not?
  • In an average month, how many Chiari decompressions do you perform? How many tethered cord releases? How many craniocervical fusions? What percentage of your practice is spent treating patients with these connective tissue related conditions?
  • Looking at my brain scan, is any part of my “brainstem” herniated (below the posterior fossa)? If so, does that make me a Chiari 1.5?

Intracranial Hypotension (low pressure) Questions:
*Article to help you understand CSF Leaks & Intracranial Hypotension prior to your appointment.
If you have SYMPTOMS OF LOW INTRACRANIAL PRESSURE and/or suspect a cerebrospinal fluid leak, we recommend asking the following questions:

  • S.E.E.P.S.
    • Looking at my brain scan, do you see any Subdural fluid collections?
    • Looking at my brain scan, do you see an Enhancement of pachymeninges?
    • Looking at my brain scan, do you see an Engorgement of my venous structures? Should we do an MRV to make sure?
    • Looking at my brain scan, does my Pituitary appear to be enlarged?
    • Looking at my brain scan, does my brain appear to be Sagging?
  • Looking at my corpus callosum:
    • Does there appear to be a depression?
    • Is there an inferior pointing of the splenium?

If he/she answers affirmatively to any of the above S.E.E.P.S. questions, ask: 

  • What should be done to find/repair a potential leak?
  • Are you aware that it is common for CSF Leaks to not show up on MRI?
  • Are you willing to do a CT Myelogram and/or a digital subtraction myelogram, if I develop symptoms of a leak and none can be found on MRI?
  • Are you aware that it can often take multiple epidural blood patches to try and seal a leak, and sometimes when a blood patch fails to work, a surgical dural repair might be necessary?

Intracranial Hypertension (high pressure) Questions:
*Article to help you understand Intracranial Hypertension prior to your appointment.
If you have SYMPTOMS OF HIGH INTRACRANIAL PRESSURE, we recommend asking the following questions:

  • Looking at my brain scan, do I have cerebrospinal fluid in my sella turcica (Empty Sella Syndrome)?
  • Looking at my brain scan, do you see any evidence of my optic nerves are swollen (papilledema)?
    • If so, should I be referred to a neuro-ophthalmologist?
  • Looking at my brain scan, do my lateral ventricles appear small or flattened?
    • If so, do I need to have my pressures checked?
      • If yes, are you aware of the risks of developing a CSF Leak from a lumbar puncture?
    • What are the symptoms of a CSF Leak, should one develop?
      • What is your plan of action if I should develop these leak symptoms?
      • Are you aware that it is common for CSF Leaks to not show up on MRI?
      • Are you willing to do a CT Myelogram if I develop symptoms of a leak, and none can be found on MRI?
    • Should a leak be found, are you aware that it can often take multiple epidural blood patches to try and seal a leak?

Tethered Cord Questions: 
*Article to help you understand Tethered Cord: Sorry, Coming Soon.
If you have SYMPTOMS OF TETHERED CORD, we recommend asking the following questions:

  • Looking at my brain/cervical scan, does my brainstem appear to be elongated?
  • Looking at my cervical scan, does my spinal cord appear to be stretched?
  • Looking at my lumbar scan, does my conus reach my mid/low L2?
  • Looking at my thoracic and lumbar scan, does my spinal cord appear to be pulling to the back, or one particular side?
    • If so, should we do a prone MRI to see if it has actually adhered to that side?
  • Looking at my lumbar scan, do I appear to have fatty tissue inside the epidermis?
    • If the answer to any of these questions is affirmative, do you suspect that I have a tethered spinal cord?
    • If so, should we plan for a Tethered Cord Release before or soon after decompression surgery, so the likelihood of a failed decompression is reduced?
    • If I have urological issues, can I get a referral for urodynamic testing to rule out any other potential causes of my urological issues?

Craniocervical Instability (CCI) & Atlantoaxial Instability (AAI):
*Article to help you understand CCI & AAI prior to your appointment.
If you have SYMPTOMS OF CRANIOCERVICAL INSTABILITY or SYMPTOMS OF ATLANTOAXIAL INSTABILITY, we recommend asking the following questions:

  • Looking at my brain/cervical scans, what are the measurements of my clivoaxial angle, Grabb-Oakes, and Harris Measurements?
  • Do these measurements meet the diagnostic criteria for Craniocervical Instability?
  • Looking at my flexion and extension imaging, how many millimeters of translation are there between flexion and extension?
  • Does Chamberlain’s Line cross my odontoid? If so, does it cross at a level that would indicate Basilar Invagination?
  • Looking at my rotational imaging, what is the percentage of uncovering of the right and left articular facets on rotation?
  • Do the percentages from my rotational imaging meet the diagnosis criteria for Atlantoaxial Instability?

IF A DIAGNOSIS CRITERIA IS MET IN ANY OF THE ABOVE, WE STRONGLY RECOMMEND THAT YOU WAIT ON DECOMPRESSION AND PURSUE THE TREATMENT OF SAID CONDITION(S) AND THAT OF EHLERS-DANLOS SYNDROME, AS EACH OF THESE CONDITIONS CAN BE PATHOLOGICAL TO AN ACQUIRED CHIARI AND EACH IS A STRONG INDICATOR THAT A CONNECTIVE TISSUE PROBLEM EXISTS. 

*The questions in this article will periodically change as we are able to expand our recommended questions.


*Original version released September 2018, revised 2023.


Oropharyngeal dysphagia = when your upper esophageal sphincter, pharynx, larynx, and/or tongue fail to coordinate properly when trying to swallow.

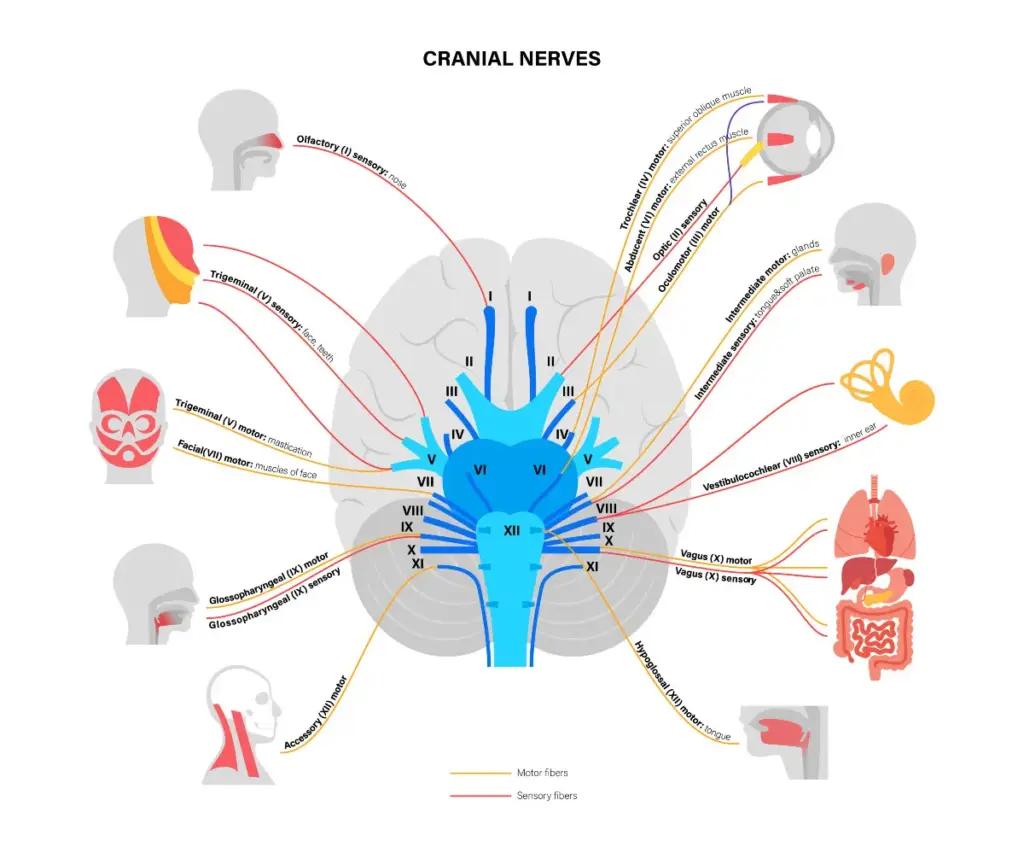
Can occur when one or more of the following nerves is damaged or compressed: facial nerve (CN VII), glossopharyngeal nerve (CN IX), vagus nerve (CN X), and hypoglossal nerve (CN XII).

Now that you know it’s a thing… ask your doctor for a swallow test to confirm it.

When you start to educate yourself on a condition like Chiari, your vocabulary will be challenged. Most of us study with a medical journal article opened in one tab and medical dictionary in the next. Amongst all the medical terminology you will tackle, there are probably a few terms as important to your understanding of Chiari than comorbidities and pathological/etiological cofactors. When two or more conditions tend to co-occur, they are said to be comorbid with one another. It makes no inferences of a causal relationship between the conditions, only that they co-occur. This co-occurrence deduces that a correlation exists, but when the nature of that correlation is not known, they are just said to be comorbidities. When a “causal relationship” is known or suspected, the conditions start being discussed in terms of pathology or etiology, which are similar, but not exactly the same thing.

An etiological cofactor exists when the “root cause” of a condition is known or believed to be known. That “root cause” is the etiological cofactor. When an etiological cofactor can cause a series of events or conditions that can become “direct causes” for other conditions, that series of events creates a pathology. Conditions along the path are called pathological cofactors. Understanding these cofactors is imperative in understanding Chiari and all of the comorbid conditions that accompany it.

ETIOLOGICAL COFACTOR:

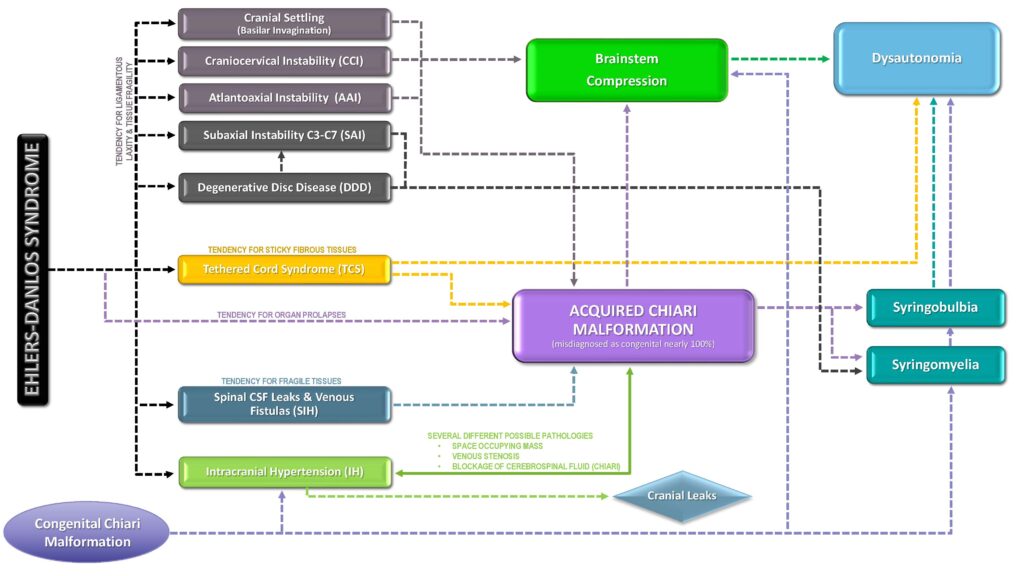
Chiari Malformation often seems like a beast that wreaks havoc on our bodies on every level. Indeed it is, but as you can see from the diagram above, it really is not the “root” of everything that is going wrong. There is a bigger beast at work in so many of us, and its name is Ehlers-Danlos. It is not by chance that so many of us with Chiari have so many other conditions in common (especially conditions like Degenerative Disc Disease, arthritis and other connective tissue problems). It is not by chance that so many of us have a history of miscarriage and similar familial histories. It is not by chance that Chiari is more prevalent in females than males. And it is definitely not by chance that Chiari is running in families and they cannot find a definitive genetic link. They cannot find it because they are not looking at the beast hiding in the background.

Ehlers-Danlos Syndromes are a group of inherited disorders involving a genetic mutation in one or more of our bodies’ collagen. Collagen is the most abundant protein, making up 1/3 of the proteins in the human body, affecting our bones, skin, muscles, and connective tissue[1]. Collagen is often described as a “cellular glue” that helps hold the body together. When that glue fails to hold, everything seems to go awry; before and after birth: skulls can under-develop in utero, organs tend to prolapse, and bones begin to shift as joint laxity increases (including the bones/vertebrae at the craniocervical junction). Ehlers-Danlos is a primary “root cause” of Chiari Malformations and a majority of the other problems we have. The list in blue is far from being a complete list of conditions caused by EDS. They are commonly accompanied with Chiari because they can cause or attribute to a Chiari malformation (pathological cofactors).[2]

PATHOLOGICAL COFACTORS:

Cranial Settling occurs when the skull has dropped and the odontoid (C2/axis) enters into the foramen magnum (Basilar Invagination). This drop can further compromise the craniocervical junction and as it pushes everything down, it increases the likelihood of an Acquired Chiari Malformation.

Craniocervical Instability (CCI) & Atlantoaxial Instability (AAI) usually occurs with cranial settling and Basilar Invagination (BI). The settling and/or softening of tissue can cause a shifting of the C2 (resulting in CCI or AAI) and the cerebellar tonsils (which are already inclined to prolapse) simply drop down with each shift affecting ones ability to tilt/rotate their head.[3]

Intracranial Hypertension (IH – High Intracranial Pressure) occurs when your intracranial pressure (ICP) becomes elevated. This elevation can happen for a variety of reasons.

  1. Space Occupying Masses (cysts, tumors or hydrocephalus) take up space inside the skull causing a “mass effect.”
  2. When no mass effect exists, many doctors look no further and give the diagnosis of Idiopathic Intracranial Hypertension.

Because the area of the skull is fixed in an adult cranium and partially fixed in that of a child, the elements inside the fixed space (CSF, blood volume and brain matter) tend to get pushed out wherever they can (the only place that they can escape without breaking through the dura is through the foramen magnum and the brain matter that’s closest to the foramen magnum is the cerebellar tonsils).[4]

Tethered Cord Syndrome occurs when the tissue inside the epidermis adheres to the spinal cord or filum terminale. While this tethering can happen anywhere along the spinal canal, it is most common in the lower lumbar and/or sacral spine. When this adhesion happens it creates a pulling down of the spinal cord and consequently, the brainstem located at the top of the spinal cord and the cerebellar tonsils just get pulled down with it.[5]

Intracranial Hypotension (Low Intracranial Pressure, often involving a CSF Leak) usually involves a cerebrospinal fluid leak or an over-draining shunt, we will highlight the former. Ehlers-Danlos patients tend to have weak dura matter. Tears/holes in the dura can happen anywhere in the dura surrounding the brain or spinal canal and they can happen completely spontaneously (without a known cause). When the leak occurs in the spinal canal, they can create a suctioning effect where cerebrospinal fluid (CSF) is being pulled down and out, causing the intracranial pressure (ICP) to drop. The cerebellar tonsils that are already prone to prolapse (due to EDS) end up getting suctioned downward with the CSF.[6] Cranial leaks often happen when high pressure is left untreated until the high pressure causes a leak in the dura mater. In cranial leaks, fluid usually leaks through the nose or ears (less common), and you can often taste the metallic taste of the cerebrospinal fluid in the back of your throat. While both spinal leaks and cranial leaks can cause low pressure and low-pressure symptoms, and while both can start, stop, and start again spontaneously, there is an increased risk whenever there is an opening where cerebrospinal fluid leaks outside of the human body (if cerebrospinal fluid can make it out of the body, microscopic bacteria can make it inside the same opening where it can enter in the meninges).[7]

Posterior Cranial Fossa Hypoplasia (PCFH) is the only etiological cofactor listed above that is definitely congenital. The role of collagen in bone development has been long-standing, especially its known contribution to certain conditions like Osteogenesis Imperfecta. However, more recent studies are discovering the role collagen plays in congenital posterior fossa anomalies. Posterior Cranial Fossa Hypoplasia is the most commonly “acclaimed” cause of Chiari malformations, but studies show, that even when all of the other causes above are factored out, only approximately 52% of those left (that fail to meet “the diagnosis criteria” for any of the above), have a small posterior fossa.[8]

COMORBIDITIES: 

While all of the conditions listed in the diagram are comorbidities, some are etiological/pathological cofactors of an Acquired Chiari (even though nearly 100% of us are told that our Chiari Malformation is congenital) and others have Chiari Malformation as their etiological/pathological cofactor:

Syringomyelia occurs when cerebrospinal fluid (CSF) is obstructed and a CSF filled cyst/cavity forms inside the spinal cord. This cyst is directly related to the obstruction of cerebrospinal fluid that can be caused by Chiari Malformation, Spinal Stenosis (a narrowing of the spinal canal, spinal cyst/tumor, a herniated disc), or irregular curvature of the spine (scoliosis). When that cyst/cavity extends into the medulla oblongata (the lowest part of the brain stem), it is called Syringobulbia, and it comes with a new set of symptoms consistent with the damage being done to the brain stem. So when Chiari Malformation exists with a syrinx, and there is no stenosis or disc problem in close proximity below it, the Chiari Malformation should be listed as the etiological cofactor for the syrinx. If more than just the Chiari Malformation is believed to be causing the syrinx, each would be more accurately described as a pathological cofactor.

Dysautonomia occurs when damage has been done to the brain stem or Vagus nerve. Whenever either of these is damaged, often from compression at/near the craniocervical junction, the autonomic nervous system can begin to dysfunction.

Confused? If you understand the causal relationships but find yourself wondering if a comorbid condition is an etiological or a pathological cofactor, think of it in terms of a domino effect. Only the first domino is the real etiological cofactor. All of the dominoes in between (on the path) are pathological cofactors. The important thing to remember in this array of medical terminology is that while everything is definitely not Chiari, it almost always shares a connection to it, and that is why so many of us have so many conditions and symptoms that doctors call unrelated! It is imperative in our fight that we know “what” we have and “why” it is happening. With such a broad spectrum of symptoms (like we all have), we must educate ourselves and not just believe the limited knowledge of our doctors.

*Revised November 2019

[wpedon id=”4396″ align=”center”]


References: 

1  McIntosh, James. “Collagen: What Is It and What Are Its Uses?” Medical News Today, MediLexicon International, 16 June 2017, <www.medicalnewstoday.com/articles/262881.php>.

2 Quake. “The Chiari Malformation Ehlers-Danlos Connection (Short Version).” Chiari Bridges, 7 Dec. 2017, <www.chiaribridges.org/chiari-malformation-ehlers-danlos-connection-short-version>.

3 Hawkeye. “Overview: Craniocervical Instability and Related Disorders.” Chiari Bridges, 6 Dec. 2017, <www.chiaribridges.org/craniocervical-instability-related-disorders>.

4 Quake. “Brain Under Pressure – Understanding Intracranial Hypertension.” Chiari Bridges, 10 Dec. 2017, <www.chiaribridges.org/brain-pressure-understanding-intracranial-hypertension>.

5 Storm. “The Tethered Cord – Chiari Malformation Connection!” Chiari Bridges, 15 Dec. 2017, <www.chiaribridges.org/tethered-cord-chiari-malformation-connection>.

6 Argent. “Overview: Cerebrospinal Fluid Leaks.” Chiari Bridges, 10 Dec. 2017, <www.chiaribridges.org/cerebrospinal-fluid-leaks>.

7 Pérez, Mario A et al. “Primary Spontaneous Cerebrospinal Fluid Leaks and Idiopathic Intracranial Hypertension” Journal of neuro-ophthalmology : the official journal of the North American Neuro-Ophthalmology Society vol. 33,4 (2013): 330-7. doi:10.1097/WNO.0b013e318299c292, <https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4040082/>

8 Quake. “Overview: Chiari Malformation.” Chiari Bridges, 6 Dec. 2017, <www.chiaribridges.org/chiari-malformation>.

✕
Chiaribridges

FREE
VIEW